
Our lens
Most pregnancy resources focus on the body. We see pregnancy differently: as a mental health journey that starts before conception and continues long after birth, for parents and for the developing brain of the child.
Three stages, three dimensions
We follow pregnancy before, within, and after, and at every stage we look through the biopsychosocial lens used in counseling and medicine. Health grows from three things working together:
Biological
Genes, hormones, nutrition, sleep, the brain, and exposures like alcohol or drugs.
Psychological
Thoughts, emotions, stress, coping, identity, and mental health history.
Social
Relationships, support, culture, money, work, health care, and discrimination.
How we use evidence, and what else we make room for
The biopsychosocial lens is our foundation. Everything we teach starts with what is happening in the body, the mind, and the world around you, and with what research shows, including where it is early or limited. But human experience is bigger than research findings. So some pages also include short, clearly labeled invitations from philosophy, culture, spirituality, and personal reflection. Here is how to tell them apart.
The default. Peer-reviewed studies and trusted health organizations. We say when the evidence is early, small, or from animals.
Questions to notice your own thoughts and feelings. There are no right answers.
Customs and practices that matter to families. We describe them. We don't rank them.
Faith, prayer, meditation, and other sources of meaning, a strength for many people.
Big questions about what is good and what matters, which research can inform but cannot answer.
Labeled, never blended
We won't present a belief or a reflection as a scientific finding, and we won't dismiss a tradition because a study didn't measure it.
Research has limits
Studies describe patterns across groups of people. They can't tell you what your life means, what you value, or what is right for you in particular.
No one right way
Families grieve, celebrate, parent, and find meaning in many ways. We don't rank them. Whatever you believe, you belong here.
Explore the map
Tap any square to see what matters and what you can do.
Across generations
Scientists call it the developmental origins of health and disease: the environment in the womb can shape a child's lifelong health, including the brain and the body's stress system. A 2020 review in Early Human Development highlighted three maternal influences on the developing brain.
Nutrition
Both too little food and an unbalanced diet matter. Adults exposed to famine early in the womb during the Dutch Hunger Winter did worse on attention tests nearly 60 years later. Managing blood sugar in pregnancy also protects the developing brain.
Infection
Some infections in pregnancy, such as rubella, measles, or severe flu, are linked to differences in brain development. Vaccines before and during pregnancy, and prompt treatment, are real prevention.
Stress
High, ongoing stress is linked to later emotional and behavior challenges. The flip side is just as real: good maternal mental health in pregnancy was linked to stronger thinking skills at age 2.
How patterns can pass down
The same environment
Families often stay in the same conditions, like poverty, unsafe neighborhoods, or food scarcity, across generations.
The body remembers
A daughter exposed to stress in the womb may carry changes in her own stress system into her pregnancies.
Parenting is learned
We often parent the way we were parented, which can pass on both strengths and struggles.
Epigenetics, honestly
Researchers are studying whether chemical marks on genes carry effects across generations. It's a promising idea, but the evidence in humans is still limited.
What can be prevented, lowered, or caught early
Some outcomes can be fully prevented. Many more can be made less likely, and almost everything goes better when it's noticed early.
Can be prevented
- Fetal alcohol spectrum disorders: no alcohol during pregnancy, since there is no known safe amount
- Harms from smoking, vaping, and drug use during pregnancy
- Many neural tube defects, with 400 mcg of folic acid daily before and during early pregnancy
- Some infections, through vaccines and food safety
Risk can be lowered
- Perinatal depression: counseling for people at higher risk
- Relapse of an existing condition: planning medications with a prescriber
- Toxic stress for children: warm, responsive caregiving and support for parents
- Relationship strain: agreements and shared work before the baby arrives
Can be caught early
- Depression and anxiety, through screening at every stage
- Life-threatening complications, through urgent warning signs up to a year after birth
- Developmental differences, through milestone checks
Things nobody tells you
Too many parents learn these facts only after a hard pregnancy, a hard first year, a child's diagnosis, or a teenager's silence. From "one drink won't hurt" to "a crying baby is just spoiled" to "it must be my fault," we share what research actually says, to educate, not to scare. Knowing early is how you protect yourself and your child.

When your baby cries: check the small things too
Crying is your baby's first language, and every baby cries. It tends to build until about 6 weeks, then slowly ease. Most of the time, a few quick checks and some comfort do the trick. Tick things off as you go; nothing is saved.
1. The basics
2. The small things
Comfort that works
Hold your baby close, skin to skin or in a carrier. Swaddle snugly (stop once your baby tries to roll), rock or walk gently, hum or shush, dim the lights, or offer a pacifier. In a randomized trial, carrying babies more reduced crying. If your baby falls asleep in a swing, bouncer, or carrier, move them to a flat, firm sleep space.
Share the soothing
Crying is exhausting, and either parent can do this. Trade off in shifts, hand the baby over before you hit your limit, and ask a trusted person to take a turn so you can rest. Babies often settle differently in different arms.
Call your pediatrician if
- Your baby is under 3 months and has a temperature of 100.4°F (38°C) or higher
- The cry is weak, unusually high-pitched, or just doesn't sound right
- Your baby refuses feeds, vomits repeatedly, or has fewer wet diapers
- Your baby is floppy, hard to wake, struggling to breathe, or has a swollen, hard belly
- You find a hair tourniquet, or a body part looks red, swollen, or purple
When they're 15 or 20: what parents wish they'd known
Parenting doesn't end when the diapers do. The teen and young-adult years bring their own surprises, and they're easier with a plan.
Keep the door open
Many teens talk most in the car, at bedtime, or while doing something side by side. Listen first, skip the lecture, and say "thank you for telling me." A teen who feels heard keeps talking.
Signs worth acting on
- Sadness, irritability, or hopelessness lasting weeks
- Pulling away from friends and activities they enjoyed
- Big changes in sleep, appetite, or grades
- More alcohol or drug use, or self-harm marks
- Talk of being a burden, giving belongings away, or not wanting to be here
If you're worried
Ask directly and calmly, listen without judging, and connect them with their doctor or a counselor. Call or text 988 any time, or text HOME to 741741. If there's immediate danger, call 911.
The paperwork at 18
Nobody warns you that your child's legal privacy starts at 18. A short conversation now can save a crisis later. Talk about these together, as your young adult's choice. Tick them off as you go; nothing is saved.
Alcohol: the clear facts
No safe amount
The CDC says there is no known safe amount of alcohol during pregnancy or while trying to get pregnant, and no safe time to drink.
No safe type
Wine and beer carry the same risk as liquor. Alcohol passes from the parent's blood to the baby.
100% preventable
Fetal alcohol spectrum disorders, which cause lifelong learning, behavior, and physical challenges, are completely preventable when there is no alcohol in pregnancy.
Never too late
If you drank before you knew you were pregnant, stop now and tell your provider. Stopping at any point helps your baby.
Why "I turned out fine" isn't proof
Alcohol can affect one baby more than another, and there's no way to know in advance which baby will be affected. Effects can also show up years later as trouble with attention, learning, memory, or behavior, which can be mistaken for other conditions.
Partners make it easier
When a partner or family skips alcohol too, or keeps it out of the house, it's easier for the pregnant person to stop. Support beats pressure.
If stopping is hard
That's a health condition, not a moral failing. Talk to your provider, or find confidential treatment at FindTreatment.gov. Getting help is one of the most loving things you can do for your baby.
Thinking about getting pregnant?
Some of the most important brain development happens before most people know they're pregnant. The months before conception are a chance to get your body, your mind, and your relationship ready.

Why the months before matter
Day 28
The neural tube, which becomes the brain and spinal cord, forms and closes within about the first month after conception, often before a pregnancy test turns positive.
400 mcg
The CDC recommends that everyone who could become pregnant take 400 micrograms of folic acid every day, starting at least one month before pregnancy, to help prevent neural tube defects.
Both partners
Health habits of the person contributing sperm matter too. Smoking, heavy drinking, and some medications can affect sperm quality.
Could I be pregnant?
Common early signs
- A missed period
- Unusual tiredness
- Tender or swollen breasts
- Nausea, with or without vomiting
- Needing to urinate more often
Feelings count too
Mood swings, tearfulness, or a rush of worry can arrive early. If you have a history of depression or anxiety, let your provider know as soon as you find out.
Next steps
Take a home pregnancy test, which is most accurate from the first day of a missed period, then book a prenatal visit to confirm and start care.
Health checks before you try
Vaccines
Make sure you're protected against measles, mumps, and rubella (MMR). Rubella in pregnancy can affect a baby's development, and the MMR vaccine can't be given during pregnancy, so the CDC advises waiting 4 weeks after the shot before trying.
Screenings
Get up to date on cervical screening, and consider testing for sexually transmitted infections for both partners. Many have no symptoms and are treatable.
Vitamins
Take folic acid daily, and ask your provider about vitamin D. In the UK, the NHS recommends a vitamin D supplement for everyone who is pregnant or trying.
Talk to your provider before trying if you or your partner…
- Live with a condition such as epilepsy, diabetes, sickle cell disease, HIV, or a past cancer treatment
- Take any prescription or over-the-counter medicine or herbal remedy. Don't stop prescribed medicine on your own; ask about the safest option first
- Have a known fertility issue, such as endometriosis or low sperm count
- Find sex difficult or impossible, for example because of a disability
- Want help to stop smoking, drinking, or using drugs
- Have been trying for a year, or six months if you're 35 or older
How pregnancy begins
Conception is a journey of several days. Tap each step.
The fertile window
Sperm can survive in the body for up to five days, but an egg can be fertilized for only about 12 to 24 hours after ovulation. That's why the days just before and on ovulation day matter most.
It often takes time
Even when timing is right, conception happens only about 1 in 4 times each cycle at best. Most people under 35 who have sex every 2 to 3 days get pregnant within a year, and chances fall gradually after that; with insemination (IUI), about 3 to 6 rounds is a common window before a doctor reassesses. When to ask for help
Many paths, same biology
Some families conceive with medical help: sperm placed in the uterus (IUI), or eggs fertilized in a lab and transferred as an embryo (IVF). Donor eggs, donor sperm, and surrogacy all build families too, including for LGBTQ+ couples, and trans and non-binary people can carry pregnancies as well.
Both partners' health counts
Sperm take about two to three months to develop, so a partner's alcohol, smoking, and health in the months before conception matter too.
Caring for your mental health first
A history of depression, anxiety, bipolar disorder, or trauma doesn't mean you shouldn't have a baby. It means you deserve a plan. People who have had depression before are at higher risk of depression during pregnancy or after birth, and planning ahead is one of the most effective ways to lower that risk.
Talk to your prescriber before you try
If you take medication for mental health, don't stop it on your own. Some medications are considered safe in pregnancy and stopping suddenly can cause relapse. A prescriber can weigh the options with you.
Learn your early warning signs
Write down what your own stress or low mood looks like: sleep changes, pulling away, irritability. Share it with someone you trust so they can notice too.
Build your nervous system skills now
Slow breathing, regular movement, time outdoors, and steady sleep are easier to practice before a baby arrives. They become your toolkit later.
Seven steps to plan for pregnancy
From the CDC. Getting ready can look different for different people, so take what fits.
Talk to your provider
Bring a list: health conditions, every medicine and supplement you take, vaccines you may need, and daily habits.
Take 400 mcg of folic acid daily
Start at least one month before pregnancy, ideally around three months, to help prevent defects of the brain and spine. A prenatal vitamin covers this.
Stop alcohol, smoking, and certain drugs
They're linked to premature birth and birth defects, and stopping protects your baby from the start. If stopping feels impossible, that's a reason to ask for help, not a failure.
Avoid toxic substances
Some chemicals, metals, fertilizers, bug spray, and cat or rodent feces at home or work can harm reproductive health, for all partners.
Care for your body's health
Both higher and lower body weight can affect pregnancy. Your provider can talk with you about what's healthy for your body, without judgment.
Learn your family history
It can point to risks for you or your baby. Your provider may suggest genetic counseling, especially after several miscarriages or trouble getting pregnant.
Care for your mental health
Everyone feels worried or sad sometimes. If those feelings don't go away or get in the way of daily life, get help. Support is also available if you're in a stressful or abusive situation.
Free help
1-800-QUIT-NOW for quitting smoking, and FindTreatment.gov for alcohol and drug treatment near you.
A readiness reflection
This isn't a test and there's no passing score. Tick what's already in place; what's left is your to-do list. Your answers stay only in this browser.
Pregnant
You're growing a brain and a body, and your own brain is changing too. Here's what supports both of you, without the pressure of doing everything perfectly.


How nutrients and the gut microbiome shape your baby's developing brain.
Why Food Matters During PregnancyMonth by month: what's forming in the brain, and what you might be feeling.
0–9 Months
How early experiences build the brain's architecture.
Baby BrainRespectful care, asking questions, and making decisions with your providers.
Your Care TeamThe three trimesters at a glance
A full-term pregnancy averages about 40 weeks. Choose a trimester to see what's happening for your baby, your body, and your mind.
Your baby, week by week
Sizes are averages. Healthy babies come in many different sizes.
Inside the womb: how it fits together
- Uterus (womb)The muscular organ where the baby grows. It stretches during pregnancy to hold the baby, the placenta, and the amniotic fluid.
- Amniotic sac and fluidA fluid-filled sac that cushions and protects the baby and lets the baby move.
- PlacentaA temporary organ attached to the wall of the uterus. It passes oxygen and nutrients from your blood to the baby, carries waste away, and makes hormones.
- Umbilical cordThe cord that connects the baby to the placenta. Its blood vessels carry oxygen and nutrients to the baby and waste back.
- CervixThe lower end of the uterus. It stays firm and closed during pregnancy, then softens and opens (dilates) for birth.
- Vagina (birth canal)The passage from the cervix to the outside of the body. It stretches during a vaginal birth.
- BladderSits in front of the uterus. As the uterus grows it presses on the bladder, which is why you may need to urinate more often.
- Baby (embryo, then fetus)Called an embryo until about week 10 of pregnancy and a fetus after that. Here the baby is head-down, the usual position near the end of pregnancy.
When is a baby "full term"?
Medical groups updated these definitions in 2013, because babies born even a week or two early can face more health risks than babies born at 39 weeks or later.
34–36 weeks: late preterm
Why 39 weeks matters
The last weeks give the baby's lungs, brain, and liver time to finish developing. Unless there's a medical reason to deliver sooner, the NIH advises waiting until at least 39 weeks.
If your baby comes early
Babies born before 37 weeks have a higher risk of problems like developmental delays, vision and hearing problems, and cerebral palsy, and they get specialized care to help. Medicine has come a long way: in an NIH research network study of babies born from 2003 to 2007 at its hospitals, 92% of those born at 28 weeks survived to go home, though many faced serious health challenges.
Care for NICU parents too
Having a baby in intensive care is a known risk factor for parents' depression and anxiety, and it can take a toll on any parent. Ask the NICU team about family support, and lean on the support lines.
If your baby is breech
About 3 to 4 in 100 babies are still bottom- or feet-first near the end of pregnancy. Hearing this can be stressful, especially if you'd hoped for a certain kind of birth. Here are the usual options; your provider will help you decide.
Wait and watch
Many babies turn on their own before about 36 weeks. Your provider will check position at later visits.
Turning the baby
In an external cephalic version (ECV), usually offered around 37 weeks, a doctor gently presses on your belly to roll the baby head-down, with ultrasound and heart-rate monitoring before, during, and after. It works roughly half to two-thirds of the time, more often if you've given birth before. Serious problems are rare, and you can ask to pause or stop at any time.
Planning the birth
If the baby stays breech, most babies are born by planned cesarean. Some hospitals with experienced providers offer a planned vaginal breech birth for carefully selected pregnancies. Either way, a cesarean is not a failure.
Home and alternative methods
Positions like the breech tilt, playing music low on the belly, moxibustion, chiropractic techniques, or homeopathy are popular, but there's little strong evidence that they work. Talk with your provider before trying any, especially anything involving herbs, pressure, or lying upside down.
How a doula can help during a version
A doula can explain what to expect beforehand (it can be uncomfortable and lasts about 5 to 20 minutes, and a medicine to relax the uterus may make your heart race), help you breathe slowly and stay relaxed, remind you that you can ask for a pause, and stay afterward to talk it through, whatever the result.
Your feelings count
Disappointment, worry, or grief over a changed birth plan are normal. Talking about them with your partner, doula, or provider, before and after, can help you feel more in control.
Stress and your nervous system
Everyday stress is part of life and doesn't harm your baby. Research on stress in pregnancy focuses on distress that is high and long-lasting, especially when there's little support.
A 2024 review in Molecular Psychiatry brought together brain-imaging studies from pregnancy through adulthood. Ongoing anxiety, stress, or depression during pregnancy was linked with differences in how parts of the baby's brain involved in emotion and memory develop. These are associations, not certainties, and they come with good news: therapy such as cognitive behavioral therapy, interpersonal therapy, and mindfulness reduces distress in pregnancy, and treating a parent's distress has been shown to benefit children's mental health too.
About 1 in 8
recent mothers report symptoms of postpartum depression, according to the CDC. Counting all mood and anxiety conditions during pregnancy and after birth, estimates are closer to 1 in 5. Even among well-resourced, highly educated women, about a quarter screened high for anxiety and stress in one study.
Most
people with depression during pregnancy or after birth don't get treatment, in part because it often goes unrecognized. Estimates range from more than half to about 8 in 10. That's why routine screening and honest conversations at every visit matter.
Support protects
Social support, in personal, family, and community relationships, is one of the most consistent protective factors for mental health in pregnancy.
Downshift daily
Try slow breathing with a longer exhale (for example, in for 4, out for 6) for a few minutes. Longer exhales are linked to calmer heart rhythms through the vagus nerve.
Protect sleep
Sleep often gets harder as pregnancy goes on. Naps, side sleeping with pillows, and a wind-down routine all count.
Move in ways that feel good
For most healthy pregnancies, guidelines encourage about 150 minutes of moderate activity a week. Check with your provider about what's right for you.
Ask to be screened
The American College of Obstetricians and Gynecologists recommends screening for depression and anxiety during pregnancy and after birth. You can ask for it at any visit.
Comfort and calm: what the evidence supports
Many families are drawn to natural approaches. Here's what research supports, and where to be careful.
Movement
For most healthy pregnancies, about 150 minutes a week of moderate activity is recommended, and early studies suggest it may support the baby's developing brain too. Walking, swimming, stationary cycling, modified prenatal yoga, and light strength training are good choices, and sitting less helps too. Moderate exercise doesn't harm the baby's heart rate or blood supply in healthy pregnancies. Skip hot yoga, contact sports, and activities with a risk of falling, and check with your provider first.
Nausea
Small, frequent meals help. Vitamin B6 is a common first step, and ginger may help some people. Ask your provider before starting any supplement, and call if you can't keep fluids down.
A doula
Continuous support during labor from a trained companion is one of the best-studied comfort measures. It's linked to more spontaneous births, less use of pain medication, shorter labors, and more positive birth experiences.
Calming practices
Mindfulness, breathing exercises, and prenatal yoga can ease stress and anxiety in pregnancy. Childbirth classes and relaxation techniques like hypnobirthing may help some people feel more confident in labor.
How hard is right? The talk test
Instead of watching your heart rate, use the talk test: during moderate activity you can talk comfortably but not sing. Drink water, and avoid getting overheated, especially in hot, humid weather. Regular movement can also ease back pain and constipation, lift mood, and improve sleep.
Stop and call your provider if you notice
Vaginal bleeding or fluid leaking, regular painful contractions, dizziness or feeling faint, chest pain, trouble breathing before you start, a headache, muscle weakness that affects your balance, or pain or swelling in your calf.
"Natural" doesn't always mean safe
Many herbs, such as valerian, lemon balm, and concentrated lavender supplements, haven't been studied enough in pregnancy to know they're safe. Raspberry leaf tea is popular, but evidence that it eases labor is weak. Ask your prenatal provider or pharmacist before trying any herb, tea in large amounts, or supplement.
Hands-on therapies
Acupuncture may help some people with nausea or back pain, and chiropractic care may ease low back pain. Choose practitioners trained in prenatal care, and let your obstetric provider know.
Things nobody tells you about your baby
See all tenBefore your baby arrives: two ideas about connection and about your own past that parents rarely hear.
Packing for the hospital or birth center
Aim to pack about a month before your due date. Check off as you go; your list stays in this browser. Hospitals usually provide a gown, basic toiletries, and disposable underwear for you, and diapers, wipes, and blankets for your baby. Labor can be messy, so leave your nicest clothes at home.
Your feed and your mind
Nearly everyone who is pregnant now turns to social media for information and support. A 2025 review of recent studies found it can genuinely help: groups moderated by midwives or other professionals improved knowledge, confidence, and help-seeking, and reduced isolation, especially for people with high-risk pregnancies. The same review found real risks: much pregnancy content online isn't backed by science, idealized images can lower self-esteem and raise worry, and heavy use has been linked with poorer sleep and mood.
A UK study that followed more than 1,100 pregnant people found social media use climbs from early pregnancy to about 20 weeks, then levels off. First-time parents used it more. Mid-pregnancy is a good moment to check in with your scrolling.
Choose moderated spaces
Groups run or checked by midwives, nurses, or health organizations tend to share more accurate information than unmoderated ones.
Notice how you feel after
If an account leaves you more anxious or less happy with your body, it's fine to mute or unfollow it.
Bring it to your visit
Saw something worrying? Write it down and ask your provider rather than acting on it alone.
Guard your health data
Pregnancy apps and social platforms often collect sensitive information. Check privacy settings and be thoughtful about what you share.
Expecting twins or more
A systematic review of 27 studies found that most research points to more depression, anxiety, and parenting stress for parents of multiples in the first months and years than for parents of one baby, and the strain tends to be greater with triplets than twins. Fathers and partners were affected too. The reasons make sense: one study found parents of newborn twins handled about 19 feedings in 24 hours, on top of more medical visits, money pressure, and broken sleep.
Plan help before birth
Line up people for nights, meals, and errands now. Accepting help was a theme in parents' own accounts of what got them through.
Both parents need care
Partners of parents of multiples often carry an especially heavy share of baby care, along with the same sleep loss. Screen both of you.
First-time parents of multiples
Learning to parent and caring for two or more babies at once is a lot. Extra stress is expected, not a sign you're failing.
Fairness guilt is normal
Parents of multiples often worry about giving each baby equal attention. Each baby's individuality will show over time.
Why food matters during pregnancy
Food supplies the building blocks of your baby's brain, and your gut talks to your brain through nerves, hormones, immune signals, and the microbiome.
How nutrition supports your baby's brain and nervous system
1
Building the brain's structure
Nutrients from food help form brain cells, the protective myelin coating around nerves, and the chemical messengers that shape mood, attention, and learning.
- Protein
- Omega-3 fats
- Iron
- Choline
- B vitamins, including folate
- Zinc
- Iodine
2
Supporting a healthy stress-response system
Balanced, nourishing meals help keep blood sugar steady and may lower inflammation. Together with sleep, movement, and support, this creates a calmer internal environment for both of you while your baby's own stress system is forming.
3
Shaping the gut microbiome
Your gut bacteria change during pregnancy and influence immune development, metabolism, and signals that may reach the developing brain. A varied, fiber-rich diet supports a more diverse microbiome. Much of this research is still early, especially in humans.
What this means for your baby
Nutrition in pregnancy supports brain growth and connections, emotional regulation, the setting of the stress response, and long-term physical and mental health. It doesn't mean perfection is required; consistent nourishment builds a supportive foundation.
Gentle reassurance for parents
Food is one piece of development, not the whole story. Cravings, nausea, stressful weeks, or imperfect days don't cause harm. Bodies and brains are resilient, and overall patterns matter far more than single meals.
What we suggest
- Eat regular, balanced meals when you can
- Include protein, fruits, vegetables, healthy fats, and whole foods
- Stay hydrated
- Take a prenatal vitamin as directed
- Avoid alcohol and other substances your provider advises against
- Talk with your provider or midwife about supplements and any dietary needs
The gut–brain connection, in plain words
Your gut and brain are in constant conversation through the vagus nerve, hormones, immune signals, and gut bacteria. Researchers call this the microbiota–gut–brain axis. In pregnancy, your gut–brain system reaches your baby indirectly, through the placenta: hormones, immune signals, and nutrients and other substances made with help from your gut bacteria. The vagus nerve links each person's own gut and brain; it doesn't connect parent to baby directly.

Variety helps most: vegetables, fruits, beans, whole grains, eggs, fish low in mercury, nuts, and fermented foods if you enjoy them. Your provider can tell you which fish and cheeses to avoid.
Foods to handle with care
A few foods carry a higher risk of infections or mercury that can harm a developing baby.
Raw or undercooked
Meat, poultry, eggs, and seafood, including sushi with raw fish. Cook until hot all the way through.
Unpasteurized
Raw milk and cheeses or juices that aren't pasteurized. Check the label.
High-mercury fish
Shark, swordfish, king mackerel, marlin, orange roughy, bigeye tuna, and tilefish from the Gulf of Mexico. Lower-mercury fish like salmon, sardines, and shrimp are good choices.
Deli meats and hot dogs
Heat until steaming before eating to lower the risk of listeria.
Your provider can tailor this to your health, culture, and food traditions.
What the science says, and what it doesn't yet
A review in the journal Gut Microbes gathered research on how the trillions of bacteria living in our gut may shape brain development before and after birth. Much of this work comes from studies in mice, so treat it as a promising window into how development might work rather than settled advice.
A two-way conversation
Gut bacteria can signal the brain through the vagus nerve, hormones, the immune system, and substances they make. The brain talks back too: in animal studies, stress changed the gut lining and which bacteria thrived.
Fiber feeds the conversation
Gut bacteria break down fiber from plant foods into short-chain fatty acids, which help keep the gut healthy and may affect the brain. They also make vitamins, including K2 and B12, which matters for the developing nervous system.
Before birth
The placenta protects and feeds the growing brain. In mice, it even turns the mother's tryptophan (an amino acid from protein foods) into serotonin for the developing forebrain. Animal studies also suggest the mother's gut bacteria during pregnancy can influence how offspring handle stress.
After birth
A baby's gut starts gathering bacteria at birth, during the same window when the brain is growing fastest. How a baby is born and fed both shape those early bacteria. In mice, early life looked like a sensitive window: bacteria added later didn't undo the early differences.
Four ways gut bacteria talk to the brain
A 2022 review in Clinical and Experimental Pediatrics pulls together what researchers know about how the gut and brain communicate. Most of the evidence comes from lab animals, so read this as how the system may work, not as a to-do list.
1
Messenger chemicals
Gut bacteria can make versions of the brain's own chemical messengers, including GABA (a calming signal), serotonin, and dopamine. These act on the body or change how it makes its own.
2
Immune signals
When the gut is out of balance or an infection is fighting, the immune system releases inflammatory messengers called cytokines. These can reach the developing brain and change how brain cells grow.
3
The vagus nerve
About 80% of the vagus nerve's fibers carry information up from the body to the brain, including news about the gut. In animal studies, a calming effect from a probiotic disappeared when the vagus nerve was cut.
4
Bacterial by-products
Most of the body's serotonin outside the brain (about 90% in humans) is made in the gut, and bacterial by-products influence how much. Butyrate, a short-chain fatty acid made from fiber, helped strengthen the blood–brain barrier in mice.
How gut bacteria help build a brain
The brain's own immune cells
Microglia, the brain's immune cells, help shape connections between nerve cells, build their insulation, and clear away what isn't needed. In mice raised without gut bacteria, or given antibiotics, microglia stayed immature. Putting bacteria back, or adding short-chain fatty acids, helped them recover.
Learning, memory, and connections
Mice without gut bacteria showed differences in the hippocampus (a learning and memory area), in the insulation around nerves in the prefrontal cortex, and in genes for building synapses. Some of these changes reversed when normal bacteria returned. Early life appears to be an especially important window.
What shapes your gut bacteria
Many things change which bacteria live in your gut. Researchers list these as the main ones, and they are also why gut studies are so hard to compare.
- Diet
- Medicines, including antibiotics
- Stress
- Age
- How a baby is born
- Your genes and other body factors
Infections in pregnancy
Why infections matter for the brain
A strong immune reaction to an infection during pregnancy can affect how a baby's brain develops. Research has linked flu in the first trimester with a higher chance of schizophrenia in the child later in life. The chance for any one family remains low, and most babies whose mothers had infections are not affected.
What you can do
- Wash your hands often
- Get the vaccines your provider recommends
- Handle food safely (see "Foods to handle with care" above)
- Call your provider early if you have a fever or feel unwell
Gut bacteria and autism: what we know, and what we don't
No single "autism bacterium"
Several reviews pooled 9 to 18 studies each. They found different patterns, and a bacterium that was lower in one review was sometimes higher in another. Studies used different methods, and diet and medicines can also change gut bacteria. Researchers can't yet name a bacterial pattern that explains autism.
Treatments are still experimental
Probiotic trials have mixed results: some saw gains in certain behaviors and others saw none. Small studies of fecal microbiota transfer, a medical procedure, reported improvements that lasted at two years, but they were small and had no placebo group. It is not an approved treatment for autism.
What this means for you
Autism isn't caused by parenting, by what you ate, or by how your baby was born or fed. Before you start probiotics, special diets, or supplements for autism, talk with your child's doctor.
Source: Kim, G.-H., & Shim, J.-O. (2022). Gut microbiota affects brain development and behavior. Clinical and Experimental Pediatrics, 66(7), 274–280.
Myth or fact?
Tap each card to check it.
Food, feeding, and mental health
What we eat in pregnancy helps build the brain, and how we feed children shapes their relationship with food, their bodies, and their feelings. Both are part of mental health.
From womb to table
Before
Folic acid at least a month before pregnancy, and a varied diet, give the first weeks of brain development what they need, often before you know you're pregnant.
Within
Nutrients like folate, iron, iodine, choline, and omega-3 fats are building blocks of the growing brain. Your gut bacteria are part of the conversation too.
After
Feeding becomes a relationship. Responding to hunger and fullness cues, sharing meals, and how we talk about food and bodies all shape a child's emotional health.
Eating during pregnancy
Diet quality and children's emotions
A large Norwegian study of more than 23,000 mothers and children found that a less healthy diet in pregnancy, and in a child's early years, was linked to more behavior and emotional problems by age 5, regardless of other family factors.
Daily needs in pregnancy
Pregnancy raises the need for brain nutrients. Recommended daily amounts: folate 600 mcg from food and supplements (including a 400 mcg folic acid supplement), choline 450 mg, iodine 220 mcg, iron 27 mg, calcium 1,000 mg (1,300 mg for teens), and vitamin D 600 IU. If you eat little or no animal food, ask about vitamin B12, which supports red blood cells and the nervous system. Many prenatal vitamins don't include enough choline, so check the label and ask your provider.
Iron and mood
Pregnancy doubles your iron needs to make extra blood for the baby. Low iron can bring headaches and deep tiredness, and low iron stores after birth have been linked with postpartum depression. Ask your provider to check your iron. Pairing iron-rich foods or supplements with vitamin C (like orange juice or strawberries) helps absorption, while calcium can block it, so take them at different times.
Iodine matters
A UK study found children of mothers with low iodine in early pregnancy were more likely to have lower verbal IQ and reading scores. Check that your prenatal vitamin contains iodine.
Fish, wisely
Fish supplies omega-3 fats for the brain. The FDA suggests 2 to 3 servings a week of low-mercury fish such as salmon, sardines, or shrimp.
When food is scarce
Studies of the Dutch "Hunger Winter" famine of 1944–45 found that severe hunger in early pregnancy was linked to higher rates of schizophrenia in adult children. Access to enough food is a mental health issue.
Brain food, made easy
The first 1,000 days, from conception to age 2, are when the brain grows fastest. Prenatal vitamins help, but many don't contain enough choline, so food matters too. Here's where to find three key brain nutrients, and simple ways to fit them in.
Folate
Beans and lentils, leafy greens, citrus fruits, eggs, and fortified breads and cereals.
Choline
Eggs (one of the richest sources), meat, chicken, fish, dairy, and beans.
Iodine
Dairy, eggs, seafood, and iodized salt. Check that your prenatal vitamin includes iodine too.
What brain scans tell us about food in pregnancy
A 2024 review in the journal Nutrients gathered studies that used ultrasound, MRI, and brain-wave tests to look at how a parent's diet in pregnancy relates to a baby's developing brain. Here is what it found, shared gently.
The good news
Across studies, eating in line with standard dietary guidelines in mid to late pregnancy was consistently linked to healthier brain development in babies. No special or expensive diet is needed.
Folate, all the way through
Lower folate early in pregnancy was linked to smaller brain volume in childhood. Children whose mothers kept taking folic acid through the whole pregnancy, not just the first trimester, showed more efficient language processing at age 11.
Omega-3s help
Higher omega-3 levels in mid-pregnancy were linked to more gray and white matter in children at ages 9 to 11.
Enough, not too much
For iron and iodine, both too little and too much were linked to smaller brain measures. More isn't always better, so take supplements as your provider recommends rather than doubling up.
Foods for sometimes
Some studies linked more ultra-processed foods, sodas, added sugar, and very salty foods with small differences in babies' head growth or brain tissue. These are averages across many pregnancies, so enjoying them sometimes is part of normal life.
Gentle swaps, not rules
Water or milk alongside an occasional soda. A piece of fruit with a sweet treat. Adding one more vegetable or an egg to a meal you already like. Small, steady steps count.
Folate and choline, a team
Both help close the neural tube and support the growing brain. Animal studies suggest they work together, with choline possibly helping buffer low folate. Human studies link them to children's thinking skills, though results aren't always consistent. Choline needs rise from 425 to 450 mg a day in pregnancy.
The recommended amount is the goal
Some studies have raised questions about very large supplement doses of folic acid or choline, and researchers don't yet know how much is too much for brain development. Taking your prenatal vitamin as directed, plus a varied diet, is the safe sweet spot.
What science still doesn't know
Many of these studies were small, measured only head size, or relied on people remembering what they ate. They show links, not proof. Researchers are still learning, and so are we.
Feeding your baby
Breast milk has real benefits
Breastfeeding is linked to health benefits for babies and parents, and some studies find modest gains in children's thinking skills.
A parent's mental health matters too
A UK study found mothers who planned to breastfeed but couldn't had a higher risk of postpartum depression. Pressure and guilt around feeding can hurt.
Alcohol while breastfeeding
The CDC says not drinking is the safest choice. If you do have a drink, waiting at least 2 hours before nursing lowers how much reaches your baby.
Fed and connected
Whether by breast, bottle, donor milk, or formula, holding, eye contact, and responding to your baby's cues are what build connection. Lactation consultants and mental health providers can both help.
Things nobody tells you about your baby
See all tenAfter birth: what crying and comforting mean, and what the research says.
Raising kids who feel good around food
Trust hunger and fullness
Children are born able to sense when they're hungry and full. Pressuring them to clean their plate, or strictly restricting foods, can teach them to tune out those signals.
Share family meals
A review of 14 studies found that regular family meals were linked to fewer depressive symptoms, less disordered eating, and better well-being in children and teens.
Talk about health, not weight
Teens whose parents talked about their weight or told them to diet were more likely to develop disordered eating. Teens whose parents talked about healthy eating without mentioning weight were less likely to.
Food and mood go together
A review of 12 studies in children and teens linked healthier diets with better mental health, and less healthy diets with poorer mental health.
Feeding words
Tap a card to see a gentler way to say it.
0–9 months
Slide through pregnancy month by month. Each month shows what's forming in your baby's brain and what you might be feeling. Months are approximate. Week numbers are counted the way your provider counts them, from the first day of your last period.
Baby's brain
Your mind and body
Timelines vary from pregnancy to pregnancy. Your provider is the best guide to your own.
Six keys to your baby's brain health
Tap each key to see what helps.
When the path is hard
Infertility, pregnancy loss, and painful reproductive health conditions are common, and so is the grief, anxiety, and depression that can come with them. None of it is your fault, and you don't have to carry it quietly.
Trying to conceive
1 in 6
adults worldwide (WHO, 2023) experience infertility at some point, defined as not getting pregnant after a year of trying.
When to ask
Guidelines suggest an evaluation after 12 months of trying if you're under 35, after 6 months if you're 35 or older, and right away if you're 40 or older or have a known condition.
20–50%
of women in studies of infertility evaluation and treatment report significant depressive symptoms, and anxiety is common too.
Infertility can feel like a crisis. People describe shock, anger, guilt, shame, a loss of control, and a sense that life is on hold. Treatment itself adds stress: hard decisions, injections and appointments, cost, and long waits. Access isn't equal either; treatment is expensive, often not covered by insurance, and success rates differ by race, which reflects gaps in care.
Relationships feel it too, and intimacy can become strained. Many couples also say getting through it together made them closer.
Therapy helps
For mild to moderate depression and anxiety, therapy is the first-line treatment. Mindfulness-based programs designed for infertility and relaxation techniques reduce anxiety.
Medication questions
If you take an antidepressant, talk with your prescriber before stopping. In one review, common antidepressants (SSRIs) did not lower IVF success rates, while untreated depression and anxiety were linked to lower odds.
Every path to parenthood
Donor eggs or sperm, surrogacy, and LGBTQ+ family building bring their own decisions and feelings. Counseling designed for these paths is available.
Pain, hormones, and mood
Some common gynecological conditions are closely tied to mental health. Pain and mood feed each other: depression and anxiety can make pain feel worse, and ongoing pain raises the risk of depression.
Endometriosis
Affects an estimated 7–15% of women and is found in many people being evaluated for infertility. Women with endometriosis have higher rates of depression and anxiety, especially with chronic pain.
Chronic pelvic pain
About as common as asthma, and one of the most common reasons for seeing a women's health specialist. It often comes with depression, anxiety, and strain on daily life and relationships.
Polycystic ovary syndrome
One of the most common hormone conditions in people of reproductive age. Its effects on cycles, fertility, and appearance can weigh heavily on mood and self-image.
Pregnancy loss
About 1 in 10
known pregnancies ends in miscarriage, most often in the first 12 weeks. Some studies find as many as 1 in 5, and more pregnancies end so early that the person never knew they were pregnant.
Not your fault
The most common causes are chromosomal or developmental problems that no one could have prevented. In up to half of losses, no cause is ever found.
Grief is normal
Grief after loss often softens gradually, but there is no set timeline, and it can return around due dates and anniversaries for years.
A pregnancy loss is the loss of a baby and of the future you imagined together. Parents may feel sadness, numbness, yearning, guilt, shame, anger, or a sense of failure. Because miscarriage is so often kept private, many people grieve alone.
For some, grief becomes intense and long-lasting, or turns into depression, anxiety, or post-traumatic stress, especially after a later loss or a sudden, traumatic one. Risk is higher with past mental health conditions and little support, and lower when partners grieve together and feel supported by their care team.
Partners grieve too
Partners often focus on caring for the person who was pregnant and feel they can't show their own grief. That can lead to throwing themselves into work or using substances to cope. Their grief deserves space too.
LGBTQ+ families
Pregnancies that took great planning and effort can make loss especially painful, and families who already feel overlooked by society may feel their grief is overlooked twice.
Support that fits
Talk therapy adapted for pregnancy loss, including interpersonal therapy and CBT, can reduce depression and anxiety. Many grieving parents look for support groups where they see people like themselves. It's okay to keep looking until one fits.
Pregnancy after loss
Most people who experience a loss become pregnant again. Anxiety in the next pregnancy is common and often rises as you approach the week of the earlier loss. Some parents hold back from feeling attached; others can't stop thinking about the pregnancy. Many wait to share the news. All of these are understandable.
Tell your provider about the loss
Extra reassurance visits or check-ins around the anniversary week can help.
Hope and grief can coexist
Loving this baby doesn't mean forgetting the one you lost.
Keep checking in after birth
Anxiety and depression can continue after a healthy baby arrives. That doesn't mean something is wrong with you.
How to support someone after a loss
Baby brain
Genes provide the blueprint, but experiences build the house. In the first years of life, a baby's brain forms connections faster than at any other time.

1 million+
new neural connections form every second in the first few years of life, according to Harvard's Center on the Developing Child.
About ⅓
of an adult's brain size is present at birth. The brain roughly doubles in the first year and reaches about three-quarters of its adult size by age 2.
Use it or lose it
Connections that are used often grow stronger. Unused ones are pruned away, which makes the brain more efficient.
New: love, connection, and your baby's brain
Explore the neuroscience of attachment with interactive brain and stress-system diagrams, a development timeline, and a guide to the things nobody tells you about your baby. All with peer-reviewed references, and a reminder that you do not have to do this alone.
How the brain builds itself
Well-established Brain development is not a single event. Several processes overlap, start early, and keep going long after birth. Here is the rough order, using the scientific terms you may hear from your care team.
First trimester: laying the foundation
Neurulation folds a flat sheet of cells into the neural tube, the starting point of the brain and spinal cord. Neurogenesis, the making of new neurons from neural stem cells, begins soon after.
Second trimester: moving and connecting
New neurons travel to their places in a process called neuronal migration. The outer layer of the brain, the cortex, builds up in layers as they arrive, the first synapses form (synaptogenesis, which speeds up later), and the senses start to emerge.
Third trimester: maturing
Connections between brain regions expand and the cortex matures. Myelination begins in some regions, as nerve fibers are wrapped in insulating myelin, and continues for years after birth. Hearing and other senses keep developing, and newborns recognize familiar sounds such as their mother's voice, which suggests some learning before birth.
After birth: experience shapes the wiring
Experience-dependent plasticity means the brain keeps forming and pruning synapses in response to experience, especially warm, responsive care. Attachment and co-regulation, when a caregiver helps a baby settle their feelings and body, are part of this.
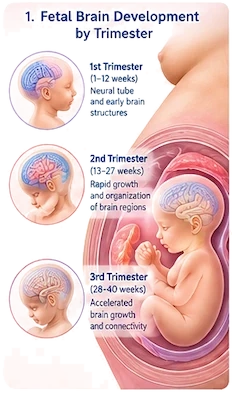
These processes overlap and don't begin or end exactly at trimester boundaries. No single event in pregnancy decides a child's future, and the brain stays changeable throughout life.
Four brain regions, in plain words
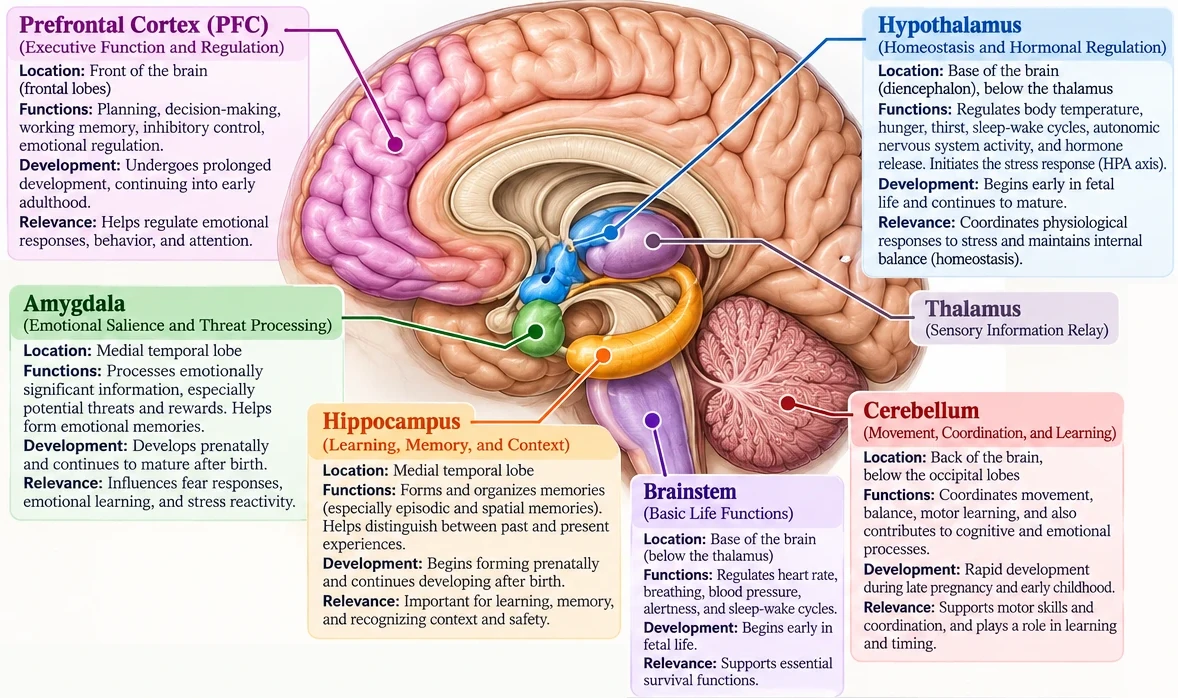
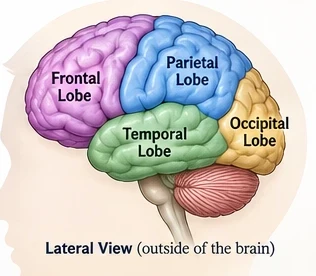
You may meet these names in articles or at appointments. Each region does several jobs, and they work together as a network, not alone. The amygdala, hippocampus, and hypothalamus are often grouped with other regions as the limbic system (interconnected regions involved in emotion, memory, motivation, and body regulation). All of them keep maturing after birth.
Amygdala
A pair of almond-shaped clusters of neurons, one in each temporal lobe (the sides of the brain at about ear level). It helps the brain notice what matters emotionally, such as possible threats, rewards, and learned associations, and it communicates with the hippocampus, hypothalamus, and prefrontal cortex. It is not simply a "fear center." Early hardship has been linked to differences in how it activates and connects, but outcomes vary widely from person to person.
Hippocampus
A paired structure in the temporal lobes involved in memory for events (episodic memory), finding your way around (spatial navigation), and learning in context. It has receptors for glucocorticoids, steroid hormones that affect metabolism, immunity, and the stress response. Cortisol is the main one in humans. Long-lasting stress may affect how the hippocampus works, but effects are not the same for everyone.
Prefrontal cortex
The front part of the frontal lobes, behind the forehead. It supports executive functions: planning, organizing, and directing behavior; working memory (holding information in mind for a short time); inhibitory control (pausing an automatic reaction); decision-making; and emotional regulation. It keeps maturing into adulthood, which is one reason children need help with big feelings.
Hypothalamus
A small structure below the thalamus that helps keep the body's internal conditions steady (homeostasis). It influences temperature, hunger, thirst, sleep-wake rhythms, automatic body functions, and hormone signaling. Its link with the pituitary gland is central to the body's stress response. See stress hormones, simply explained.
Serve and return
When a baby coos, looks, or points (the "serve") and a caregiver responds with words, eye contact, or a smile (the "return"), brain connections for language, emotion, and attention are strengthened. You don't need special toys or programs. Back-and-forth everyday moments are the program.
Three kinds of stress
Not all stress is harmful. What makes the difference is how intense and long it lasts, and whether a caring adult is there to buffer it.
After a stressful pregnancy: what helps
See also: How a parent's mental health shapes a baby's brain
If your pregnancy was stressful, here is something many parents never hear: what happens after birth matters a great deal. A 2023 review in Biological Psychiatry found that not every child exposed to stress in the womb develops problems, and that warm, supportive early environments are linked to healthier brain development and can soften, and sometimes offset, the effects of prenatal stress.
Sensitive care
Babies of mothers who had high anxiety or distress in pregnancy did not show lower cognitive scores when their caregivers were warm and responsive. In another study, a stress-hormone difference linked to a parent's mental illness in pregnancy wasn't seen in babies who got sensitive care.
Skin to skin
For premature babies, skin-to-skin holding (kangaroo care) and programs that build parents' responsiveness were linked to more mature brain connections, calmer stress responses, and better language and thinking skills.
Talk, read, play
Everyday talk, books, and play support the brain's language, attention, and self-control circuits. Children born smaller didn't fall behind in language when parents were highly responsive, and reading to babies in the NICU improved early social interaction.
Support for parents
When mothers had strong social support, depression or anxiety in pregnancy was not linked to differences in their babies' emotion-regulation brain circuits. Supporting the parent supports the baby.
Money matters too
Family resources are linked to infant brain development. In a randomized trial, giving low-income families monthly cash support in their baby's first year was linked to brain-activity patterns associated with later learning. Policies like paid leave and family support are brain health.
Honest about the science
Some studies, including some trials, haven't found these protective effects, and researchers are calling for larger long-term studies. But the overall direction is hopeful and consistent with animal research.
Secure attachment builds self-control
A secure attachment means a baby has learned that their caregiver will reliably come, comfort them, and be a safe base for exploring. A 2022 study followed 102 families from infancy to kindergarten, observing mothers, fathers, and children at 7 months, 15 months, and about 5½ years.
Both parents
Children with more secure attachment at 15 months, with their mother and with their father, did better on thinking-and-self-control tasks at age 5, like saying "night" when shown a picture of the sun.
Why it helps
When a child trusts that help will come, they don't have to spend energy watching for danger. That frees up attention, memory, and focus for learning.
How it grows
Through ordinary, repeated moments: coming when your baby cries, comforting them, keeping routines predictable, and cheering them on as they explore.
Big-feelings babies: for better or for worse
Some babies get angry and frustrated quickly and intensely. In the same study, for these more anger-prone babies, the quality of their early relationship with their mother mattered more than it did for calmer babies, in both directions.
When the relationship was less secure, anger-prone children later had a harder time following their mother's requests than calmer peers. When it was secure, they did better than calmer peers. Researchers call this differential susceptibility: some children are especially sensitive to their environment, for better or for worse.
The pattern appeared with mothers, who were the primary caregivers in most of these families, but not with fathers.
See the feeling, not a plot
In less secure relationships, parents were more likely to read a child's anger as deliberate. Seeing it as a feeling your child can't yet manage helps you stay calm.
Defuse, don't escalate
Secure parent–child pairs tended to use humor, distraction, and emotion coaching, like naming the feeling and helping the child calm down, when tempers rose.
Repair counts
No parent responds perfectly. Coming back after a hard moment with comfort teaches your child the relationship is safe.
Words to know
We keep the real scientific terms and explain them, so you can follow what you read and ask your care team informed questions. Tap a word to open it, or search the list.
Cortisol
The main glucocorticoid in humans. It helps supply energy, regulate blood sugar and the immune system, and adapt to demands. It rises and falls naturally through the day and in response to stress.
Dopamine
A neurotransmitter involved in movement, motivation, and learning from rewards.
GABA (gamma-aminobutyric acid)
The main inhibitory neurotransmitter in the mature brain, meaning it helps calm neural activity. Its effects work differently in early development.
Glial cells
Brain cells that are not neurons. They support the brain's metabolism, watch over immune health, and help regulate how neurons signal.
Glucocorticoids
Steroid hormones that influence metabolism, immunity, and the stress response. Cortisol is the main one in humans.
Glutamate
The main excitatory neurotransmitter in the mature brain, meaning it helps drive neural activity. It is important for learning and for synaptic plasticity, the ability of synapses to strengthen or weaken.
HPA axis
The hypothalamic-pituitary-adrenal axis, a neuroendocrine system (the nervous system and hormone-producing glands communicating together) involved in stress responses. The hypothalamus releases CRH (corticotropin-releasing hormone), the pituitary releases ACTH (adrenocorticotropic hormone), and the adrenal glands release cortisol, which signals back to help switch the system down.
Limbic system
Interconnected brain regions involved in emotion, memory, motivation, and body regulation.
Myelin
A fatty insulating coat around some nerve fibers that helps signals travel efficiently.
Neurogenesis
The making of new neurons from neural stem cells or progenitor cells.
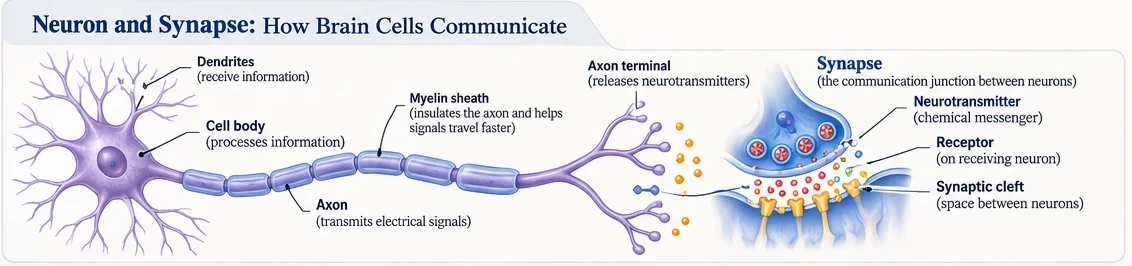
Neuron
A specialized cell that receives and sends information using electrical and chemical signals.
Neuronal migration
The movement of developing neurons to the places where they will work.
Neuroplasticity
The nervous system's ability to change its structure or function with development, learning, experience, or injury.
Neurotransmitter
A chemical messenger released by neurons that affects other cells.
Neurulation
The embryonic process that forms the neural tube, which becomes the brain and spinal cord.
Oligodendrocytes
Glial cells that make myelin around nerve fibers in the brain and spinal cord.
Placenta
A temporary organ that supports exchange between parent and baby and produces hormones, including its own CRH.
Serotonin (5-HT)
A neurotransmitter involved in mood-related signaling, sleep, digestion, and more. Anxiety or depression cannot be explained by serotonin or dopamine alone.
Synapse
The junction where a neuron communicates with another neuron or a target cell.
Synaptic pruning
The removal or reorganization of some synapses during development, which makes the brain more efficient.
Synaptogenesis
The formation of synapses, the connections between neurons.
No matching words.
A classic book, in context
Historical perspective
The Secret Life of the Unborn Child (Thomas R. Verny, with John Kelly, 1981) helped popularize prenatal psychology and the idea that babies experience and learn before birth. Some of its themes, such as prenatal hearing and learning, have support in later research. But claims that a baby understands emotions like an adult, remembers like an adult, or is shaped directly and permanently by a parent's passing feelings are not established science. We share the book as history, not as evidence.
Study limits: a small group of mostly low-risk, two-parent families from one region of the US, so findings may not apply to every family. The results show links, not proof of cause.
Things Nobody Tells You About Your Baby
Ten common beliefs about babies and toddlers, what the research actually says, and what is going on in the brain. Tap a card to read more.
Ten things worth knowing
Thing 1 · newborn and babyYour baby's cry is information, not a lesson to ignoreCommon belief: "Let your baby cry so they learn."Tap to read the scienceHide
What research indicates
Crying is a baby's main way of signalling needs. In colic, no single cause has been found. Babies cry about two hours a day on average in the first six weeks, easing to about an hour by 10 to 12 weeks, with big differences between babies. The small amount of recent research on sleep training does not show harm to attachment, but the studies are small and short, they cannot rule out every effect, and this is not advice to leave a baby crying. Gentler, responsive approaches also exist, and choosing not to sleep-train is a legitimate choice.
What is happening in the brain
A young baby's prefrontal cortex and calming systems are still maturing, so a baby cannot settle by themselves the way an older child can. Caregivers help their baby's body and feelings settle, a process called co-regulation. Regulation changes with age: in one study, babies from 5 to 18 months relied more on shared regulation as they grew.
Evidence Wolke et al., 2017 DOI; Zeevenhooven et al., 2018 DOI; Gradisar et al., 2016 DOI; Bilgin & Wolke, 2020 DOI; Reuter et al., 2020 DOI; Kolk & Rakic, 2022 DOI; Atkinson et al., 2021 DOI
Thing 2 · newborn and babyYour baby is not trying to manipulate youCommon belief: "They're just crying to get picked up."Tap to read the scienceHide
What research indicates
We did not find research showing that young babies cry to manipulate. Research describes crying as a signal. Sensitive, responsive care is associated with slightly better child outcomes, and we found no evidence that comforting babies "spoils" them.
What is happening in the brain
Planning and understanding other minds develop gradually over the first years, alongside brain regions that are still maturing. A newborn's cry is better understood as a signal of a felt need, such as discomfort, hunger, or wanting closeness.
Evidence Cooke et al., 2022 DOI; Britto et al., 2017 DOI; Vreden et al., 2025 DOI; Kolk & Rakic, 2022 DOI
Thing 3 · toddlerYour toddler says "no" because they are growingCommon belief: "They're being defiant."Tap to read the scienceHide
What research indicates
Between about ages one and three, toddlers' words, preferences, and sense of self develop quickly, and saying "no" is part of this. Children say the word "no" early, but they understand it as a logical idea ("it is not in the box") only after about age two. Tantrums are common: in one survey of 861 children aged 1 to 5, tantrums were less frequent in older children but lasted longer (parent report, comparing different children by age). Parenting that takes the child's view, offers choices where possible, and explains rules is linked with better wellbeing, mostly in studies of older children. It is different from permissiveness.
What is happening in the brain
Executive function (planning, holding information in mind, stopping an impulse) develops gradually from infancy through the preschool years and beyond. A toddler wants things strongly while the brain parts that apply the brakes are still maturing.
Evidence Feiman et al., 2017 DOI; Van den Akker et al., 2022 DOI; Bradshaw et al., 2025 DOI; Hoyniak et al., 2023 DOI; Montroy et al., 2016 DOI
Thing 4 · newborn and babyYour baby depends on connectionCommon belief: "They'll be fine on their own."Tap to read the scienceHide
What research indicates
Human babies are born very dependent. In the first year they cannot move, feed, or regulate themselves without help from caregivers, and researchers see this long dependence as part of how babies learn from and bond with the people around them. Attachment is the lasting bond that grows between a baby and familiar caregivers; its purposes are protection and a felt sense of safety.
What is happening in the brain
Brain networks develop fastest in the first two years, shaped by genes and experience, including the sights, sounds, and touch of caregiving; parents are one important part of that environment, not all of it.
Evidence Izaki et al., 2024 DOI; Burkart et al., 2025 DOI; Kliesch, 2025 DOI; Gilmore et al., 2018 DOI; Britto et al., 2017 DOI
Thing 5 · baby and toddlerComforting does not make them weakCommon belief: "If you always pick them up, they'll be clingy."Tap to read the scienceHide
What research indicates
We found no study showing that comforting or promptly responding to a baby or toddler makes a child more dependent. Long-term studies point the other way: mothers' sensitive parenting was associated with children's language, executive function, and self-reliance in a US cohort of 1,364 children, and more securely attached children were less likely to be overly reliant on their teachers. These are observational studies, not trials.
What is happening in the brain
Attachment theory's "secure base" idea is that children who can count on comfort can explore more freely. The evidence is still limited, so it is a theory with some supporting findings, not a proven rule.
Evidence Foley et al., 2025 DOI; Neuhaus et al., 2021 DOI; Verschueren & Spilt, 2021 DOI; Bernier et al., 2024 DOI; Nivison et al., 2026 DOI
Thing 6 · baby and toddlerYour baby cannot calm down like an adultCommon belief: "Just tell them to calm down."Tap to read the scienceHide
What research indicates
Babies depend on caregivers to help them regulate emotion, and regulation changes with age. In one study following infants from 5.5 to 18 months, babies used less self-soothing and more regulation shared with their caregiver as they grew older. Infants also differ a lot in how they regulate.
What is happening in the brain
The prefrontal cortex, which helps manage impulses and emotions, keeps maturing until about the third decade of life. Young children rely on adults to help them calm down because these systems are still under construction. That is normal development, not a failure of the child or the parent.
Evidence Kolk & Rakic, 2022 DOI; Atkinson et al., 2021 DOI; Ohmura et al., 2022 DOI; Möller et al., 2019 DOI; Johnston et al., 2017 DOI; Pease et al., 2016 DOI
Thing 7 · for youYou are allowed to need a breakCommon belief: "A good mother never gets frustrated."Tap to read the scienceHide
What research indicates
Crying can be exhausting, and frustration is common. Needing a break is not a sign you will harm your baby. Stepping away and asking for help is widely recommended; research on whether it prevents injury is limited. If you feel overwhelmed and your baby is fed, changed, and safe, it is reasonable to place the baby on their back in a safe sleep space (firm, flat, no soft bedding), step away for a few minutes to calm yourself, and ask another adult to take over or call a health professional.
What is happening in the brain
Stress and sleep loss affect adults' brains and bodies too. Parents who are struggling, with depression, anxiety, very broken sleep, or little support, may find caregiving harder on average. The link with depression is small, and one large study found it largely explained by other circumstances. Many such parents care well.
Evidence Moon et al., 2022 DOI; Scott et al., 2022 DOI; Chang et al., 2024 DOI; Bernard et al., 2018 DOI; MacMillan et al., 2021 DOI; Padrutt et al., 2026 DOI
Thing 8 · for youYou do not have to be a perfect motherCommon belief: "One mistake and the bond is broken."Tap to read the scienceHide
What research indicates
Parent and baby are not in perfect step. In one study of 116 mother-infant pairs, the pair was in a matched positive state about 58 to 70 percent of the time in play, and mismatches typically lasted about five seconds before they matched again. Out of sync is normal; repair is part of ordinary life. In a large review, sensitive care explained only a modest share of differences in attachment, and no parent is sensitive all the time.
What is happening in the brain
Brains stay changeable, and the research we found concerns repeated experience over time rather than single moments. We found no research showing that ordinary parenting stress or an imperfect day changes a child's brain.
Evidence Hu et al., 2025 DOI; Madigan et al., 2024 DOI; Nivison et al., 2026 DOI; Nelson & Gabard-Durnam, 2020 DOI; Reh et al., 2020 DOI
Thing 9 · for youYour childhood does not have to become your child'sCommon belief: "I will repeat what happened to me."Tap to read the scienceHide
What research indicates
Parents' early attachment experiences are linked with their children's attachment only moderately (about r = .29 to .31), and the link has weakened in newer studies. Most differences between children are not explained by a parent's history. Programs that help parents notice and respond to their baby's signals can increase children's security.
What is happening in the brain
The brain stays able to change throughout life, though change is usually greatest early. After severe early adversity, stable high-quality care was linked with better outcomes in one trial. That does not mean everyone can "heal completely".
Evidence Verhage et al., 2016 DOI; Verhage et al., 2018 DOI; Mountain et al., 2017 DOI; King et al., 2023 DOI; Reh et al., 2020 DOI
Thing 10 · baby and familyYour baby can feel safe with more than one personCommon belief: "Only the mother can really comfort a baby."Tap to read the scienceHide
What research indicates
Babies usually form attachments to more than one caregiver. Fathers' sensitivity relates to security about as strongly as mothers', and children's security with fathers is, on average, only very slightly lower than with mothers. In one hunter-gatherer community, caregivers other than the mother provided 40 to 50 percent of a child's care. Evidence on other caregivers such as grandparents and adoptive parents is more limited.
What is happening in the brain
Researchers argue that sharing care among several adults has long been part of how human babies are raised.
Evidence Madigan et al., 2024 DOI; Pinquart, 2022 DOI; Chaudhary et al., 2024 DOI; Burkart et al., 2025 DOI

What is my baby trying to tell me?
Four everyday situations. Tap an option to read what research suggests. These are possibilities to think about, not diagnoses, and no single answer is right for every child.
A. Your six-week-old is crying
It is evening, your baby has been fed and changed, and they are crying hard.
B. Your toddler says "NO!"
You ask your two-year-old to put on their shoes. They say "no" and sit down on the floor.
C. You feel overwhelmed
It has been a long night. Your baby is fed, changed, and still crying, and you feel your temper rising.
D. Your baby is upset when you leave
You step out of the room and your ten-month-old cries and reaches for the door.
What is still uncertain
- Most of these findings are associations from observational studies; they cannot prove that a parenting choice causes an outcome.
- Sleep-training studies are small and short, so we cannot say every method is safe for every baby.
- We found no recent studies tracking the timing of separation distress (ages come from milestone checklists), and no randomized trials of "spoiling" or of whether comforting changes later dependence.
- Many studies come from a limited range of countries, so we know less about families elsewhere. Families everywhere comfort and raise babies in many good ways.
- This content has not yet been reviewed by a pediatrician or developmental specialist.
The message under every card
Babies need connection, protection, and responsive care. Crying is communication. Saying "no" is normal growth. Calm develops slowly, over years. And you do not have to do this alone. Secure attachment is not created by a mother sacrificing her own wellbeing. Your rest, health, and support are part of caring for your baby, and they belong in the picture just as much as the neuroscience.
Support for mothers after birth: Postpartum Support International
Postpartum Support International (PSI) offers free help for pregnancy and postpartum mental health, for mothers and for other parents. You do not need to be in crisis to reach out. Feeling overwhelmed, anxious, sad, or not like yourself after a baby is common and treatable, and you will always hear back from a person, not an AI program.
- Call the PSI HelpLine: 1-800-944-4773 (press 1 for Spanish, 2 for English)
- Text in English: text "Help" to 800-944-4773
- Text in Spanish: 971-203-7773
- App: download "Connect by PSI" in your app store
The HelpLine is free and confidential. You can leave a message any time, and calls and texts are returned every day, from 8 am to 11 pm Eastern time. It gives information, support, and local resources. It is not a crisis line and does not handle emergencies. About the HelpLine
References
All sources are peer-reviewed journal articles or professional policy statements published 2016 to 2026. Select a number to jump to its reference, and a DOI to open the original article. APA 7th edition.
- Wolke, D., Bilgin, A., & Samara, M. (2017). Systematic review and meta-analysis: Fussing and crying durations and prevalence of colic in infants. The Journal of Pediatrics, 185, 55-61.e4. https://doi.org/10.1016/j.jpeds.2017.02.020 https://doi.org/10.1016/j.jpeds.2017.02.020 meta-analysis
- Zeevenhooven, J., Browne, P. D., L'Hoir, M. P., de Weerth, C., & Benninga, M. A. (2018). Infant colic: mechanisms and management. Nature Reviews Gastroenterology & Hepatology, 15(8), 479-496. https://doi.org/10.1038/s41575-018-0008-7 https://doi.org/10.1038/s41575-018-0008-7 narrative review
- Gradisar, M., Jackson, K., Spurrier, N. J., Gibson, J., Whitham, J., Williams, A. S., Dolby, R., & Kennaway, D. J. (2016). Behavioral interventions for infant sleep problems: A randomized controlled trial. Pediatrics, 137(6), e20151486. https://doi.org/10.1542/peds.2015-1486 https://doi.org/10.1542/peds.2015-1486 RCT
- Bilgin, A., & Wolke, D. (2020). Parental use of 'cry it out' in infants: No adverse effects on attachment and behavioural development at 18 months. Journal of Child Psychology and Psychiatry, 61(11), 1184-1193. https://doi.org/10.1111/jcpp.13223 https://doi.org/10.1111/jcpp.13223 longitudinal cohort
- Reuter, A., Silfverdal, S.-A., Lindblom, K., & Hjern, A. (2020). A systematic review of prevention and treatment of infant behavioural sleep problems. Acta Paediatrica, 109(9), 1717-1732. https://doi.org/10.1111/apa.15182 https://doi.org/10.1111/apa.15182 systematic review
- Kolk, S. M., & Rakic, P. (2022). Development of prefrontal cortex. Neuropsychopharmacology, 47(1), 41-57. https://doi.org/10.1038/s41386-021-01137-9 https://doi.org/10.1038/s41386-021-01137-9 narrative review (human and animal)
- Atkinson, N. H., Jean, A. D. L., & Stack, D. M. (2021). Emotion regulation from infancy to toddlerhood: Individual and group trajectories of full-term and very-low-birthweight preterm infants. Infancy, 26(4), 570-595. https://doi.org/10.1111/infa.12405 https://doi.org/10.1111/infa.12405 longitudinal observational cohort
- Cooke, J. E., Deneault, A.-A., Devereux, C., Eirich, R., Fearon, R. M. P., & Madigan, S. (2022). Parental sensitivity and child behavioral problems: A meta-analytic review. Child Development, 93(5), 1231-1248. https://doi.org/10.1111/cdev.13764 https://doi.org/10.1111/cdev.13764 meta-analysis
- Britto, P. R., Lye, S. J., Proulx, K., Yousafzai, A. K., Matthews, S. G., Vaivada, T., Perez-Escamilla, R., Rao, N., Ip, P., Fernald, L. C. H., MacMillan, H., Hanson, M., Wachs, T. D., Yao, H., Yoshikawa, H., Cerezo, A., Leckman, J. F., & Bhutta, Z. A. (2017). Nurturing care: promoting early childhood development. The Lancet, 389(10064), 91–102. https://doi.org/10.1016/s0140-6736(16)31390-3 https://doi.org/10.1016/s0140-6736(16)31390-3 narrative review (Lancet Series paper)
- Vreden, C., Atim, S., Buryn-Weitzel, J. C., Di Gregorio, G., Donnellan, E., Hoffman, M., Holden, E., Jurua, M., Knapper, C. V., Marshall, S., Paricia, J., Tusiime, F., Wilke, C., Slocombe, K. E., & Clay, Z. (2025). Maternal responsiveness to infant distress: A cross-cultural investigation in Uganda and the United Kingdom. Developmental Psychology. https://doi.org/10.1037/dev0002038 https://doi.org/10.1037/dev0002038 longitudinal cohort (naturalistic observation)
- Feiman, R., Mody, S., Sanborn, S., & Carey, S. (2017). What Do You Mean, No? Toddlers’ Comprehension of Logical “No” and “Not”. Language Learning and Development, 13(4), 430-450. https://doi.org/10.1080/15475441.2017.1317253 https://doi.org/10.1080/15475441.2017.1317253 experimental comprehension study (3 experiments)
- Van den Akker, A. L., Hoffenaar, P., & Overbeek, G. (2022). Temper Tantrums in Toddlers and Preschoolers: Longitudinal Associations with Adjustment Problems. Journal of Developmental & Behavioral Pediatrics, 43(7), 409-417. https://doi.org/10.1097/dbp.0000000000001071 https://doi.org/10.1097/dbp.0000000000001071 cross-sectional survey plus 1-year follow-up (subsample)
- Bradshaw, E. L., Duineveld, J. J., Conigrave, J. H., Steward, B. A., Ferber, K. A., Joussemet, M., Parker, P. D., & Ryan, R. M. (2025). Disentangling autonomy-supportive and psychologically controlling parenting: A meta-analysis of self-determination theory’s dual process model across cultures. American Psychologist, 80(6), 879-895. https://doi.org/10.1037/amp0001389 https://doi.org/10.1037/amp0001389 meta-analysis (meta-analytic structural equation modelling)
- Hoyniak, C. P., Donohue, M. R., Quiñones-Camacho, L. E., Vogel, A. C., Perino, M. T., Hennefield, L., Tillman, R., Barch, D. M., & Luby, J. L. (2023). Developmental pathways from preschool temper tantrums to later psychopathology. Development and Psychopathology, 35(4), 1643-1655. https://doi.org/10.1017/s0954579422000359 https://doi.org/10.1017/s0954579422000359 prospective longitudinal cohort (enriched for early psychopathology)
- Montroy, J. J., Bowles, R. P., Skibbe, L. E., McClelland, M. M., & Morrison, F. J. (2016). The development of self-regulation across early childhood. Developmental Psychology, 52(11), 1744-1762. https://doi.org/10.1037/dev0000159 https://doi.org/10.1037/dev0000159 longitudinal cohort (3 samples)
- Izaki, A., Verbeke, W. J. M. I., Vrticka, P., & Ein-Dor, T. (2024). A narrative on the neurobiological roots of attachment-system functioning. Communications Psychology, 2(1), 96. https://doi.org/10.1038/s44271-024-00147-9 https://doi.org/10.1038/s44271-024-00147-9 narrative review (theoretical)
- Burkart, J. M., Cerrito, P., Natalucci, G., & van Schaik, C. P. (2025). Cooperative Breeding as a Likely Early Catalyst of Human Evolution. Evolutionary Anthropology: Issues, News, and Reviews, 34(3), e70016. https://doi.org/10.1002/evan.70016 https://doi.org/10.1002/evan.70016 review (evolutionary anthropology)
- Kliesch, C. (2025). Postnatal dependency as the foundation of social learning in humans. Proceedings of the Royal Society B: Biological Sciences, 292(2045), 20242818. https://doi.org/10.1098/rspb.2024.2818 https://doi.org/10.1098/rspb.2024.2818 theoretical review
- Gilmore, J. H., Knickmeyer, R. C., & Gao, W. (2018). Imaging structural and functional brain development in early childhood. Nature Reviews Neuroscience, 19(3), 123-137. https://doi.org/10.1038/nrn.2018.1 https://doi.org/10.1038/nrn.2018.1 narrative review (imaging)
- Foley, J. E., Olino, T. M., & Weinraub, M. (2025). On the Broader Significance of Maternal Sensitivity: Mothers’ Early and Later Sensitive Parenting Matter to Children's Language, Executive Function, Academics, and Self‐Reliance. Developmental Science, 28(1), e13594. https://doi.org/10.1111/desc.13594 https://doi.org/10.1111/desc.13594 longitudinal cohort (random-intercept cross-lagged panel model)
- Neuhaus, R., McCormick, M., & O’Connor, E. (2021). The mediating role of child-teacher dependency in the association between early mother-child attachment and behavior problems in middle childhood. Attachment & Human Development, 23(5), 523-539. https://doi.org/10.1080/14616734.2020.1751989 https://doi.org/10.1080/14616734.2020.1751989 longitudinal cohort (secondary analysis)
- Verschueren, K., & Spilt, J. L. (2021). Understanding the origins of child-teacher dependency: mother-child attachment security and temperamental inhibition as antecedents. Attachment & Human Development, 23(5), 504-522. https://doi.org/10.1080/14616734.2020.1751988 https://doi.org/10.1080/14616734.2020.1751988 longitudinal observational study
- Bernier, A., Côté, S. M., Leclerc, G., Matte-Gagné, C., & Marquis-Brideau, C. (2024). Revisiting the childcare–attachment question: under what conditions is childcare participation associated with mother–child attachment security?. Attachment & Human Development, 26(2), 95–115. https://doi.org/10.1080/14616734.2024.2344521 https://doi.org/10.1080/14616734.2024.2344521 cross-sectional/longitudinal cohort (observational)
- Nivison, M. D., Fearon, P., Jenkins, J. M., & Madigan, S. (2026). Annual Research Review: The role of caregiver sensitivity in children's developmental outcomes – an umbrella review. Journal of Child Psychology and Psychiatry, 67(4), 486–507. https://doi.org/10.1111/jcpp.70087 https://doi.org/10.1111/jcpp.70087 umbrella review (17 meta-analyses)
- Ohmura, N., Okuma, L., Truzzi, A., Shinozuka, K., Saito, A., Yokota, S., Bizzego, A., Miyazawa, E., Shimizu, M., Esposito, G., & Kuroda, K. O. (2022). A method to soothe and promote sleep in crying infants utilizing the transport response. Current Biology, 32(20), 4521-4529.e4. https://doi.org/10.1016/j.cub.2022.08.041 https://doi.org/10.1016/j.cub.2022.08.041 experimental (within-subject physiological study)
- Möller, E. L., de Vente, W., & Rodenburg, R. (2019). Infant crying and the calming response: Parental versus mechanical soothing using swaddling, sound, and movement. PLOS ONE, 14(4), e0214548. https://doi.org/10.1371/journal.pone.0214548 https://doi.org/10.1371/journal.pone.0214548 experimental (counterbalanced)
- Johnston, C., Campbell-Yeo, M., Disher, T., Benoit, B., Fernandes, A., Streiner, D., Inglis, D., & Zee, R. (2017). Skin-to-skin care for procedural pain in neonates. Cochrane Database of Systematic Reviews, 2017(2), Article CD008435. https://doi.org/10.1002/14651858.cd008435.pub3 https://doi.org/10.1002/14651858.cd008435.pub3 systematic review (Cochrane) and meta-analysis
- Pease, A. S., Fleming, P. J., Hauck, F. R., Moon, R. Y., Horne, R. S. C., L'Hoir, M. P., Ponsonby, A.-L., & Blair, P. S. (2016). Swaddling and the risk of sudden infant death syndrome: A meta-analysis. Pediatrics, 137(6), e20153275. https://doi.org/10.1542/peds.2015-3275 https://doi.org/10.1542/peds.2015-3275 meta-analysis
- Moon, R. Y., Carlin, R. F., Hand, I., & the Task Force on Sudden Infant Death Syndrome and the Committee on Fetus and Newborn. (2022). Sleep-related infant deaths: Updated 2022 recommendations for reducing infant deaths in the sleep environment. Pediatrics, 150(1), e2022057990. https://doi.org/10.1542/peds.2022-057990 https://doi.org/10.1542/peds.2022-057990 policy statement · policy statement
- Scott, L. J., Wilson, R., Davies, P., Lyttle, M. D., Mytton, J., Dawson, S., Ijaz, S., Redaniel, M. T., Williams, J. G., & Savović, J. (2022). Educational interventions to prevent paediatric abusive head trauma in babies younger than one year old: A systematic review and meta-analyses. Child Abuse & Neglect, 134, 105935. https://doi.org/10.1016/j.chiabu.2022.105935 https://doi.org/10.1016/j.chiabu.2022.105935 systematic review
- Chang, H.-Y., Chang, Y.-C., Chang, Y.-T., Chen, Y.-W., Wu, P.-Y., & Feng, J.-Y. (2024). The effectiveness of parenting programs in preventing abusive head trauma: A systematic review and meta-analysis. Trauma, Violence, & Abuse, 25(1), 354-368. https://doi.org/10.1177/15248380231151690 https://doi.org/10.1177/15248380231151690 meta-analysis
- Bernard, K., Nissim, G., Vaccaro, S., Harris, J. L., & Lindhiem, O. (2018). Association between maternal depression and maternal sensitivity from birth to 12 months: a meta-analysis. Attachment & Human Development, 20(6), 578–599. https://doi.org/10.1080/14616734.2018.1430839 https://doi.org/10.1080/14616734.2018.1430839 meta-analysis
- MacMillan, K. K., Lewis, A. J., Watson, S. J., Bourke, D., & Galbally, M. (2021). Maternal social support, depression and emotional availability in early mother-infant interaction: Findings from a pregnancy cohort. Journal of Affective Disorders, 292, 757–765. https://doi.org/10.1016/j.jad.2021.05.048 https://doi.org/10.1016/j.jad.2021.05.048 prospective pregnancy cohort
- Padrutt, E. R., Stallworthy, I., DeJoseph, M., Wilson, S., & Berry, D. (2026). Maternal postnatal depression and sensitive parenting: Considering developmental timing with a causally informative approach. Developmental Psychology. https://doi.org/10.1037/dev0002273 https://doi.org/10.1037/dev0002273 prospective longitudinal cohort (causal-inference modelling)
- Hu, Y., Li, X., & McElwain, N. L. (2025). Mother–infant interactive processes and infant behavioral and vagal stress recovery: Associations at 3, 6, and 9 months of age. Developmental Psychology, 61(8), 1452–1463. https://doi.org/10.1037/dev0001878 https://doi.org/10.1037/dev0001878 observational longitudinal (still-face paradigm)
- Madigan, S., Deneault, A.-A., Duschinsky, R., Bakermans-Kranenburg, M. J., Schuengel, C., van IJzendoorn, M. H., Ly, A., Fearon, R. M. P., Eirich, R., & Verhage, M. L. (2024). Maternal and paternal sensitivity: Key determinants of child attachment security examined through meta-analysis. Psychological Bulletin, 150(7), 839–872. https://doi.org/10.1037/bul0000433 https://doi.org/10.1037/bul0000433 meta-analysis
- Nelson, C. A., & Gabard-Durnam, L. J. (2020). Early Adversity and Critical Periods: Neurodevelopmental Consequences of Violating the Expectable Environment. Trends in Neurosciences, 43(3), 133-143. https://doi.org/10.1016/j.tins.2020.01.002 https://doi.org/10.1016/j.tins.2020.01.002 narrative review
- Reh, R. K., Dias, B. G., Nelson, C. A., Kaufer, D., Werker, J. F., Kolb, B., Levine, J. D., & Hensch, T. K. (2020). Critical period regulation across multiple timescales. Proceedings of the National Academy of Sciences, 117(38), 23242-23251. https://doi.org/10.1073/pnas.1820836117 https://doi.org/10.1073/pnas.1820836117 narrative review · animal research
- Verhage, M. L., Schuengel, C., Madigan, S., Fearon, R. M. P., Oosterman, M., Cassibba, R., Bakermans-Kranenburg, M. J., & van IJzendoorn, M. H. (2016). Narrowing the transmission gap: A synthesis of three decades of research on intergenerational transmission of attachment. Psychological Bulletin, 142(4), 337–366. https://doi.org/10.1037/bul0000038 https://doi.org/10.1037/bul0000038 meta-analysis
- Verhage, M. L., Fearon, R. M. P., Schuengel, C., van IJzendoorn, M. H., Bakermans-Kranenburg, M. J., Madigan, S., Roisman, G. I., Oosterman, M., Behrens, K. Y., Wong, M. S., Mangelsdorf, S., Priddis, L. E., Brisch, K.-H., The Collaboration on Attachment Transmission Synthesis, Arnott, B., Aviezer, O., Bailey, H., Behringer, J., Bernier, A., . . . Ward, M. J. (2018). Examining Ecological Constraints on the Intergenerational Transmission of Attachment Via Individual Participant Data Meta-analysis. Child Development, 89(6), 2023–2037. https://doi.org/10.1111/cdev.13085 https://doi.org/10.1111/cdev.13085 individual participant data meta-analysis
- Mountain, G., Cahill, J., & Thorpe, H. (2017). Sensitivity and attachment interventions in early childhood: A systematic review and meta-analysis. Infant Behavior and Development, 46, 14–32. https://doi.org/10.1016/j.infbeh.2016.10.006 https://doi.org/10.1016/j.infbeh.2016.10.006 systematic review and meta-analysis of RCTs
- King, L. S., Guyon-Harris, K. L., Valadez, E. A., Radulescu, A., Fox, N. A., Nelson, C. A., Zeanah, C. H., & Humphreys, K. L. (2023). A Comprehensive Multilevel Analysis of the Bucharest Early Intervention Project: Causal Effects on Recovery From Early Severe Deprivation. American Journal of Psychiatry, 180(8), 573-583. https://doi.org/10.1176/appi.ajp.20220672 https://doi.org/10.1176/appi.ajp.20220672 RCT (long-term follow-up)
- Pinquart, M. (2022). Attachment security to mothers and fathers: A meta‐analysis on mean‐level differences and correlations of behavioural measures. Infant and Child Development, 31(6), e2364. https://doi.org/10.1002/icd.2364 https://doi.org/10.1002/icd.2364 meta-analysis
- Chaudhary, N., Salali, G. D., & Swanepoel, A. (2024). Sensitive responsiveness and multiple caregiving networks among Mbendjele BaYaka hunter-gatherers: Potential implications for psychological development and well-being. Developmental Psychology, 60(3), 422–440. https://doi.org/10.1037/dev0001601 https://doi.org/10.1037/dev0001601 observational field study
- Reuter, T., Feiman, R., & Snedeker, J. (2018). Getting to No: Pragmatic and Semantic Factors in Two- and Three-Year-Olds' Understanding of Negation. Child Development, 89(4), e364-e381. https://doi.org/10.1111/cdev.12858 https://doi.org/10.1111/cdev.12858 experimental comprehension study (2 experiments)
- Pinquart, M. (2017). Associations of parenting dimensions and styles with externalizing problems of children and adolescents: An updated meta-analysis. Developmental Psychology, 53(5), 873-932. https://doi.org/10.1037/dev0000295 https://doi.org/10.1037/dev0000295 meta-analysis
- Zubler, J. M., Wiggins, L. D., Macias, M. M., Whitaker, T. M., Shaw, J. S., Squires, J. K., Pajek, J. A., Wolf, R. B., Slaughter, K. S., Broughton, A. S., Gerndt, K. L., Mlodoch, B. J., & Lipkin, P. H. (2022). Evidence-informed milestones for developmental surveillance tools. Pediatrics, 149(3), Article e2021052138. https://doi.org/10.1542/peds.2021-052138 https://doi.org/10.1542/peds.2021-052138 policy statement (AAP-convened expert working group; literature-informed consensus; not a systematic review or RCT) · policy statement
- Van Hulle, C. A., Moore, M. N., Lemery-Chalfant, K., Goldsmith, H. H., & Brooker, R. J. (2017). Infant stranger fear trajectories predict anxious behaviors and diurnal cortisol rhythm during childhood. Development and Psychopathology, 29(3), 1119-1130. https://doi.org/10.1017/s0954579417000311 https://doi.org/10.1017/s0954579417000311 longitudinal cohort
- Battaglia, M., Garon-Carrier, G., Côté, S. M., Dionne, G., Touchette, E., Vitaro, F., Tremblay, R. E., & Boivin, M. (2017). Early childhood trajectories of separation anxiety: Bearing on mental health, academic achievement, and physical health from mid-childhood to preadolescence. Depression and Anxiety, 34(10), 918-927. https://doi.org/10.1002/da.22674 https://doi.org/10.1002/da.22674 longitudinal cohort (Quebec Longitudinal Study of Child Development)
Secure Attachment: Your Baby's Biological Need for Connection
What attachment is, why babies depend on the adults who care for them, and what research can and cannot tell you. It is not a test of your parenting.
What attachment is
Well-established Attachment is the selective, lasting emotional bond that grows between an infant and the familiar adults who care for them. In attachment theory it has two main purposes: protection and support when a baby needs it, and the felt sense of safety that comes with that. It is understood as part of human biology, which is why babies seek closeness and comfort when they are upset. A secure attachment means a baby has come to expect that a caregiver will usually help. Attachment research is a big field with active debates, and its main findings are about how caregiving relates to security. It is not a verdict on any individual parent.
Why babies depend so much on caregivers
Emerging Human babies are born very dependent. Compared with other great apes, they are born with brains that need a long period of maturation, and in the first year they cannot move about, feed, or reliably calm themselves without help. Researchers see this long dependence as part of how babies learn from, and bond with, the people around them. Many societies share the work of caring among several adults, and babies need responsive care and protection while families need support to give it. The brain is not "unfinished" or "defective" at birth; for example, the prefrontal cortex is slow to mature overall but changes quickly in the first year.
How a secure attachment develops
Sensitive, responsive care Well-established
Across 174 studies, caregivers who noticed, interpreted, and responded fairly promptly and appropriately to their baby's signals ("sensitivity") tended to have more securely attached children. The link was moderate (r = .25; .26 for mothers and .21 for fathers), meaning roughly 6 percent of the differences between children, so many other things matter too: the child, the family's circumstances, and chance. A parent's ability to wonder about what their baby might be feeling was also linked with security (r = .30). No parent is sensitive all the time, and the research does not ask for that.
Not destiny Well-established
Parents' own early attachment experiences are linked with their children's attachment only moderately (about r = .29 to .31), and that link has weakened in newer studies. Most differences between children are not explained by a parent's history. Programs that help parents notice and respond to their baby's signals can increase the number of children who are securely attached. One video-feedback program (VIPP-SD), studied in 25 trials with at-risk families, improved attachment security with a small to moderate effect (r = .23). Attachment patterns are not destiny, and later relationships and support can matter.

Rupture and repair: perfect is not the goal
Emerging In everyday play, parent and baby are not in perfect step. In one study of 116 mother-infant pairs, the pair was in a matched positive state about 58 to 70 percent of the time, and when they fell out of step the mismatch typically lasted about five seconds before they matched again. At 6 and 9 months, pairs who matched more had babies who recovered better from a brief stressful moment. Other researchers also describe parent-infant coordination as partial and two-way. The takeaway: being out of sync is normal, and repair (a smile, a word, a cuddle after a missed signal) is part of ordinary life. This comes from one US sample and cannot show that repair "builds" attachment.
A secure base for exploring
Emerging Attachment theory says that when babies and toddlers can count on a caregiver for comfort, they can more easily venture out and explore. Warmth and encouraging independence are not opposites. In one study of 236 Canadian mother-child pairs, the least secure behavior appeared in children who did not attend childcare and whose mothers were less sensitive or less supportive of autonomy. That suggests care at home matters, but the study did not measure exploration. Direct research on attachment and exploration since 2016 is limited, so this is best seen as a core idea of the theory with supporting but not decisive evidence.
More than one person can be a safe person
Well-established Babies usually form attachments to more than one caregiver. Fathers' sensitivity is related to their child's security about as strongly as mothers' (r = .21 for fathers, .26 for mothers). In a meta-analysis of 95 studies, children's security with fathers was, on average, only very slightly lower than with mothers (a very small difference), and the two were related. In one hunter-gatherer community, caregivers other than the mother provided 40 to 50 percent of a child's care. In a Canadian study, childcare attendance was not by itself linked with less secure attachment; what mattered was the care children received at home. Evidence for other kinds of caregivers, such as adoptive parents and grandparents, is limited, so we say only that other consistent caregivers can be attachment figures.
What secure attachment is associated with
These are group averages. They are not predictions for your child, and insecure attachment is not a disorder.
| Area | What studies found | Strength of evidence |
|---|---|---|
| Emotion regulation | More securely attached children, on average, regulated emotion somewhat better and showed more positive and less negative emotion. | Well-established modest effects |
| Behavior and emotional problems | In children aged 3 to 18, secure attachment was modestly linked with fewer internalizing problems such as anxiety or low mood (d = .58) and fewer externalizing problems such as aggression (d = .49). Effects were smaller in older children and varied across studies. | Well-established modest effects |
| Social competence | Earlier attachment security is linked with getting along with peers, but we found no recent study giving a reliable effect size. | Emerging |
| Learning and language | Caregiver sensitivity (not attachment itself) was moderately linked with children's thinking (r = .23) and language (r = .26). | Emerging |
Ten everyday ways to support security
These are practical ideas drawn from the research above. None requires being perfect, and none is the only right way. Different cultures comfort babies differently; in one small study of mothers in Uganda and the UK, babies recovered well in both settings.
- Notice your baby's signals and respond, not instantly every time, but often and kindly.
- Talk, sing, and take turns with sounds and smiles (back-and-forth talk is linked with children's vocabulary).
- Wonder aloud what your baby might be feeling.
- Comfort distress. We found no research showing that comforting a baby "spoils" them.
- Repair after a missed moment: a smile, a cuddle, a quiet "I'm here".
- Let your toddler explore, and be the place they can come back to.
- Share care with a partner, family, or trusted caregivers.
- Protect your own sleep, health, and mood, and ask for help early.
- Name feelings and accept them, while still setting the limits you need (supportive responses to feelings are linked with better adjustment).
- Be kind to yourself when a day goes badly (general encouragement, not a research finding).
An idea we looked at: being true to your feelings
Some of the thinking behind this page was inspired by the writings of physician Gabor Maté, who argues that children need to be allowed to feel and express their real emotions and that suppressing feelings can have long-term costs. His books and talks are not used as evidence here. We checked the idea against independent research.
- Partly supported (small associations) Parents who respond supportively to children's emotions, rather than dismissing or punishing them, tend to have children with somewhat better emotional and behavior outcomes, though the associations are small. In adults and students, habitually suppressing emotions is linked with poorer social wellbeing in correlational studies.
- Limited We found no strong evidence that suppressing feelings as a child causes later physical illness; the studies below measured adversity or diagnosed stress disorders, not suppressing feelings. Childhood adversity is linked with higher average risks for many problems, but a person's score has poor accuracy for predicting what happens to one individual, and links between everyday stress and cancer are not consistent. Stress-related psychiatric disorders have been linked with later autoimmune disease at the population level. These are associations that need cautious interpretation, not proof of a single cause.
Before you become a mother: understanding your own attachment experiences
This is for reflection only. It is not a test, it does not give you an "attachment style", and it cannot diagnose anything. Take what is useful and leave the rest.
Things worth knowing
Your own early experiences do not decide how your child will attach. The link between parents' and children's attachment is only moderate and has weakened in newer studies. You can offer your baby what you did not receive. Many parents do, with support, reflection, and good relationships now, although research on how is limited.
Pregnancy and bonding
Many parents feel connected to their baby during pregnancy, and stronger connection in pregnancy tends to go with stronger bonding afterwards, but only to a small or moderate degree. Activities such as touch, music, relaxation, and meditation are linked with higher scores on prenatal attachment measures, though we do not know that they change later bonding. The associations are small to moderate and many parents bond well after a quieter pregnancy, so feeling little connection now does not mean you will not bond.
Questions to think about, perhaps with a friend, partner, or therapist
- What did comfort look like when I was little, and what would I like to keep or change?
- Who are the people I can lean on after the baby comes?
- What do I want my baby to know about being loved?
- What would help me feel less alone in the early weeks?
If thinking about your childhood brings up pain, a perinatal mental-health professional can help. Postpartum Support International (above) can point you to one.
What is still uncertain
- Much of the attachment research so far was carried out in a small number of countries, and we are still learning how it applies to families and communities around the world. Effect sizes are modest.
- The evidence on repair, on exploration, on adoptive parents and grandparents, and on prenatal preparation is limited.
- Treating a parent's depression does not always change parenting, and the studies disagree about how much.
- This is psychoeducation and has not yet been reviewed by an attachment researcher or clinician.
Secure attachment does not require sacrifice
A baby does not need a parent who gives up sleep, health, friendships, and help to be "good enough". Research on attachment is about responsive, reasonably consistent care. Care is likely easier to give when a parent is rested, supported, and not alone, though that is general sense more than a tested finding. Looking after the person who looks after the baby is part of looking after the baby.
When a parent is struggling, for example with depression, caregiving can be a little harder on average (the link is small, r = -.16 in a review of 48 studies). These are group patterns that may reflect circumstances such as exhaustion and isolation, not how much a parent loves their child, and many parents in these situations care warmly and well. In one large US study the link largely disappeared after accounting for other life circumstances. In one study, support from a partner or family was linked with better parent-baby interaction among mothers with depressive symptoms. Programs that support parents are linked with better parent-child interaction and child outcomes, although they do not all work equally well, and no program "fixes" parenting. Asking for help, sleeping when you can, and getting treatment are good for you, and support is linked with better caregiving, though treatment studies disagree about how much it changes parenting.
Support for mothers after birth: Postpartum Support International
Postpartum Support International (PSI) offers free help for pregnancy and postpartum mental health, for mothers and for other parents. You do not need to be in crisis to reach out. Feeling overwhelmed, anxious, sad, or not like yourself after a baby is common and treatable, and you will always hear back from a person, not an AI program.
- Call the PSI HelpLine: 1-800-944-4773 (press 1 for Spanish, 2 for English)
- Text in English: text "Help" to 800-944-4773
- Text in Spanish: 971-203-7773
- App: download "Connect by PSI" in your app store
The HelpLine is free and confidential. You can leave a message any time, and calls and texts are returned every day, from 8 am to 11 pm Eastern time. It gives information, support, and local resources. It is not a crisis line and does not handle emergencies. About the HelpLine
References
All sources are peer-reviewed journal articles published 2016 to 2026. Select a number above to jump to its reference, and a DOI to open the original article. APA 7th edition.
- Izaki, A., Verbeke, W. J. M. I., Vrticka, P., & Ein-Dor, T. (2024). A narrative on the neurobiological roots of attachment-system functioning. Communications Psychology, 2(1), 96. https://doi.org/10.1038/s44271-024-00147-9 https://doi.org/10.1038/s44271-024-00147-9 narrative review (theoretical)
- Fearon, R. P., & Roisman, G. I. (2017). Attachment theory: progress and future directions. Current Opinion in Psychology, 15, 131–136. https://doi.org/10.1016/j.copsyc.2017.03.002 https://doi.org/10.1016/j.copsyc.2017.03.002 narrative review
- Burkart, J. M., Cerrito, P., Natalucci, G., & van Schaik, C. P. (2025). Cooperative Breeding as a Likely Early Catalyst of Human Evolution. Evolutionary Anthropology: Issues, News, and Reviews, 34(3), e70016. https://doi.org/10.1002/evan.70016 https://doi.org/10.1002/evan.70016 review (evolutionary anthropology)
- Kliesch, C. (2025). Postnatal dependency as the foundation of social learning in humans. Proceedings of the Royal Society B: Biological Sciences, 292(2045), 20242818. https://doi.org/10.1098/rspb.2024.2818 https://doi.org/10.1098/rspb.2024.2818 theoretical review
- Britto, P. R., Lye, S. J., Proulx, K., Yousafzai, A. K., Matthews, S. G., Vaivada, T., Perez-Escamilla, R., Rao, N., Ip, P., Fernald, L. C. H., MacMillan, H., Hanson, M., Wachs, T. D., Yao, H., Yoshikawa, H., Cerezo, A., Leckman, J. F., & Bhutta, Z. A. (2017). Nurturing care: promoting early childhood development. The Lancet, 389(10064), 91–102. https://doi.org/10.1016/s0140-6736(16)31390-3 https://doi.org/10.1016/s0140-6736(16)31390-3 narrative review (Lancet Series paper)
- Hodel, A. S. (2018). Rapid infant prefrontal cortex development and sensitivity to early environmental experience. Developmental Review, 48, 113–144. https://doi.org/10.1016/j.dr.2018.02.003 https://doi.org/10.1016/j.dr.2018.02.003 narrative review (neuroimaging)
- Madigan, S., Deneault, A.-A., Duschinsky, R., Bakermans-Kranenburg, M. J., Schuengel, C., van IJzendoorn, M. H., Ly, A., Fearon, R. M. P., Eirich, R., & Verhage, M. L. (2024). Maternal and paternal sensitivity: Key determinants of child attachment security examined through meta-analysis. Psychological Bulletin, 150(7), 839–872. https://doi.org/10.1037/bul0000433 https://doi.org/10.1037/bul0000433 meta-analysis
- Zeegers, M. A. J., Colonnesi, C., Stams, G.-J. J. M., & Meins, E. (2017). Mind matters: A meta-analysis on parental mentalization and sensitivity as predictors of infant–parent attachment. Psychological Bulletin, 143(12), 1245–1272. https://doi.org/10.1037/bul0000114 https://doi.org/10.1037/bul0000114 meta-analysis (multilevel, with meta-analytic structural equation model)
- Verhage, M. L., Schuengel, C., Madigan, S., Fearon, R. M. P., Oosterman, M., Cassibba, R., Bakermans-Kranenburg, M. J., & van IJzendoorn, M. H. (2016). Narrowing the transmission gap: A synthesis of three decades of research on intergenerational transmission of attachment. Psychological Bulletin, 142(4), 337–366. https://doi.org/10.1037/bul0000038 https://doi.org/10.1037/bul0000038 meta-analysis
- Verhage, M. L., Fearon, R. M. P., Schuengel, C., van IJzendoorn, M. H., Bakermans-Kranenburg, M. J., Madigan, S., Roisman, G. I., Oosterman, M., Behrens, K. Y., Wong, M. S., Mangelsdorf, S., Priddis, L. E., Brisch, K.-H., The Collaboration on Attachment Transmission Synthesis, Arnott, B., Aviezer, O., Bailey, H., Behringer, J., Bernier, A., . . . Ward, M. J. (2018). Examining Ecological Constraints on the Intergenerational Transmission of Attachment Via Individual Participant Data Meta-analysis. Child Development, 89(6), 2023–2037. https://doi.org/10.1111/cdev.13085 https://doi.org/10.1111/cdev.13085 individual participant data meta-analysis
- van IJzendoorn, M. H., Schuengel, C., Wang, Q., & Bakermans-Kranenburg, M. J. (2023). Improving parenting, child attachment, and externalizing behaviors: Meta-analysis of the first 25 randomized controlled trials on the effects of Video-feedback Intervention to promote Positive Parenting and Sensitive Discipline. Development and Psychopathology, 35(1), 241–256. https://doi.org/10.1017/s0954579421001462 https://doi.org/10.1017/s0954579421001462 meta-analysis of randomized controlled trials
- Mountain, G., Cahill, J., & Thorpe, H. (2017). Sensitivity and attachment interventions in early childhood: A systematic review and meta-analysis. Infant Behavior and Development, 46, 14–32. https://doi.org/10.1016/j.infbeh.2016.10.006 https://doi.org/10.1016/j.infbeh.2016.10.006 systematic review and meta-analysis of RCTs
- Hu, Y., Li, X., & McElwain, N. L. (2025). Mother–infant interactive processes and infant behavioral and vagal stress recovery: Associations at 3, 6, and 9 months of age. Developmental Psychology, 61(8), 1452–1463. https://doi.org/10.1037/dev0001878 https://doi.org/10.1037/dev0001878 observational longitudinal (still-face paradigm)
- Beebe, B., Messinger, D., Bahrick, L. E., Margolis, A., Buck, K. A., & Chen, H. (2016). A systems view of mother–infant face-to-face communication. Developmental Psychology, 52(4), 556–571. https://doi.org/10.1037/a0040085 https://doi.org/10.1037/a0040085 observational (time-series coding)
- Bernier, A., Côté, S. M., Leclerc, G., Matte-Gagné, C., & Marquis-Brideau, C. (2024). Revisiting the childcare–attachment question: under what conditions is childcare participation associated with mother–child attachment security?. Attachment & Human Development, 26(2), 95–115. https://doi.org/10.1080/14616734.2024.2344521 https://doi.org/10.1080/14616734.2024.2344521 cross-sectional/longitudinal cohort (observational)
- Nivison, M. D., Fearon, P., Jenkins, J. M., & Madigan, S. (2026). Annual Research Review: The role of caregiver sensitivity in children's developmental outcomes – an umbrella review. Journal of Child Psychology and Psychiatry, 67(4), 486–507. https://doi.org/10.1111/jcpp.70087 https://doi.org/10.1111/jcpp.70087 umbrella review (17 meta-analyses)
- Pinquart, M. (2022). Attachment security to mothers and fathers: A meta‐analysis on mean‐level differences and correlations of behavioural measures. Infant and Child Development, 31(6), e2364. https://doi.org/10.1002/icd.2364 https://doi.org/10.1002/icd.2364 meta-analysis
- Chaudhary, N., Salali, G. D., & Swanepoel, A. (2024). Sensitive responsiveness and multiple caregiving networks among Mbendjele BaYaka hunter-gatherers: Potential implications for psychological development and well-being. Developmental Psychology, 60(3), 422–440. https://doi.org/10.1037/dev0001601 https://doi.org/10.1037/dev0001601 observational field study
- Cooke, J. E., Kochendorfer, L. B., Stuart-Parrigon, K. L., Koehn, A. J., & Kerns, K. A. (2019). Parent–child attachment and children’s experience and regulation of emotion: A meta-analytic review. Emotion, 19(6), 1103–1126. https://doi.org/10.1037/emo0000504 https://doi.org/10.1037/emo0000504 meta-analysis
- Madigan, S., Brumariu, L. E., Villani, V., Atkinson, L., & Lyons-Ruth, K. (2016). Representational and questionnaire measures of attachment: A meta-analysis of relations to child internalizing and externalizing problems. Psychological Bulletin, 142(4), 367–399. https://doi.org/10.1037/bul0000029 https://doi.org/10.1037/bul0000029 meta-analysis
- Groh, A. M., Narayan, A. J., Bakermans-Kranenburg, M. J., Roisman, G. I., Vaughn, B. E., Fearon, R. M. P., & van IJzendoorn, M. H. (2017). Attachment and Temperament in the Early Life Course: A Meta-Analytic Review. Child Development, 88(3), 770–795. https://doi.org/10.1111/cdev.12677 https://doi.org/10.1111/cdev.12677 meta-analysis
- Vreden, C., Atim, S., Buryn-Weitzel, J. C., Di Gregorio, G., Donnellan, E., Hoffman, M., Holden, E., Jurua, M., Knapper, C. V., Marshall, S., Paricia, J., Tusiime, F., Wilke, C., Slocombe, K. E., & Clay, Z. (2025). Maternal responsiveness to infant distress: A cross-cultural investigation in Uganda and the United Kingdom. Developmental Psychology. https://doi.org/10.1037/dev0002038 https://doi.org/10.1037/dev0002038 longitudinal cohort (naturalistic observation)
- Donnelly, S., & Kidd, E. (2021). The longitudinal relationship between conversational turn-taking and vocabulary growth in early language development. Child Development, 92(2), 609-625. https://doi.org/10.1111/cdev.13511 https://doi.org/10.1111/cdev.13511 longitudinal cohort (daylong audio recordings)
- Cooke, J. E., Deneault, A.-A., Devereux, C., Eirich, R., Fearon, R. M. P., & Madigan, S. (2022). Parental sensitivity and child behavioral problems: A meta-analytic review. Child Development, 93(5), 1231-1248. https://doi.org/10.1111/cdev.13764 https://doi.org/10.1111/cdev.13764 meta-analysis
- Bernard, K., Nissim, G., Vaccaro, S., Harris, J. L., & Lindhiem, O. (2018). Association between maternal depression and maternal sensitivity from birth to 12 months: a meta-analysis. Attachment & Human Development, 20(6), 578–599. https://doi.org/10.1080/14616734.2018.1430839 https://doi.org/10.1080/14616734.2018.1430839 meta-analysis
- MacMillan, K. K., Lewis, A. J., Watson, S. J., Bourke, D., & Galbally, M. (2021). Maternal social support, depression and emotional availability in early mother-infant interaction: Findings from a pregnancy cohort. Journal of Affective Disorders, 292, 757–765. https://doi.org/10.1016/j.jad.2021.05.048 https://doi.org/10.1016/j.jad.2021.05.048 prospective pregnancy cohort
- Johnson, A. M., Hawes, D. J., Eisenberg, N., Kohlhoff, J., & Dudeney, J. (2017). Emotion socialization and child conduct problems: A comprehensive review and meta-analysis. Clinical Psychology Review, 54, 65-80. https://doi.org/10.1016/j.cpr.2017.04.001 https://doi.org/10.1016/j.cpr.2017.04.001 meta-analysis
- Zinsser, K. M., Gordon, R. A., & Jiang, X. (2021). Parents’ socialization of preschool-aged children's emotion skills: A meta-analysis using an emotion-focused parenting practices framework. Early Childhood Research Quarterly, 55, 377-390. https://doi.org/10.1016/j.ecresq.2021.02.001 https://doi.org/10.1016/j.ecresq.2021.02.001 meta-analysis
- Chervonsky, E., & Hunt, C. (2017). Suppression and expression of emotion in social and interpersonal outcomes: A meta-analysis. Emotion, 17(4), 669-683. https://doi.org/10.1037/emo0000270 https://doi.org/10.1037/emo0000270 meta-analysis
- Hughes, K., Bellis, M. A., Hardcastle, K. A., Sethi, D., Butchart, A., Mikton, C., Jones, L., & Dunne, M. P. (2017). The effect of multiple adverse childhood experiences on health: a systematic review and meta-analysis. The Lancet Public Health, 2(8), e356-e366. https://doi.org/10.1016/s2468-2667(17)30118-4 https://doi.org/10.1016/s2468-2667(17)30118-4 systematic review and meta-analysis
- Baldwin, J. R., Caspi, A., Meehan, A. J., Ambler, A., Arseneault, L., Fisher, H. L., Harrington, H., Matthews, T., Odgers, C. L., Poulton, R., Ramrakha, S., Moffitt, T. E., & Danese, A. (2021). Population vs Individual Prediction of Poor Health From Results of Adverse Childhood Experiences Screening. JAMA Pediatrics, 175(4), 385. https://doi.org/10.1001/jamapediatrics.2020.5602 https://doi.org/10.1001/jamapediatrics.2020.5602 prospective birth cohorts (2)
- Galicia Pacheco, S. I., Petrova, D., Garrido, D., Catena, A., Madrid Pérez-Esparza, B., Torralba, C., Ruiz-Vozmediano, J., García-Pérez, J., Sánchez, M. J., & Garcia-Retamero, R. (2026). The relationship between psychological stress and cancer incidence: a systematic review and meta-analysis. Health Psychology Review, 20(2), 330-356. https://doi.org/10.1080/17437199.2025.2590491 https://doi.org/10.1080/17437199.2025.2590491 systematic review and meta-analysis of prospective studies
- Song, H., Fang, F., Tomasson, G., Arnberg, F. K., Mataix-Cols, D., Fernández de la Cruz, L., Almqvist, C., Fall, K., & Valdimarsdóttir, U. A. (2018). Association of Stress-Related Disorders With Subsequent Autoimmune Disease. JAMA, 319(23), 2388. https://doi.org/10.1001/jama.2018.7028 https://doi.org/10.1001/jama.2018.7028 population- and sibling-matched retrospective register cohort
- Trombetta, T., Giordano, M., Santoniccolo, F., Vismara, L., Della Vedova, A. M., & Rollè, L. (2021). Pre-natal Attachment and Parent-To-Infant Attachment: A Systematic Review. Frontiers in Psychology, 12, 620942. https://doi.org/10.3389/fpsyg.2021.620942 https://doi.org/10.3389/fpsyg.2021.620942 systematic review
- Coté, J. J., Dilsaver, D. B., Dimmock, J., Doehrman, P., Teague, S., Coté, R. D., Coté, B. P., Kilzer, R., Sabbaghi, M. O., Borelli, J. L., & Massey, S. H. (2025). Prenatal attachment interventions: a comprehensive systematic review and meta-analysis. Archives of Women's Mental Health, 28(6), 1447–1471. https://doi.org/10.1007/s00737-025-01630-w https://doi.org/10.1007/s00737-025-01630-w systematic review and meta-analysis
- Branjerdporn, G., Meredith, P., Strong, J., & Garcia, J. (2017). Associations Between Maternal-Foetal Attachment and Infant Developmental Outcomes: A Systematic Review. Maternal and Child Health Journal, 21(3), 540–553. https://doi.org/10.1007/s10995-016-2138-2 https://doi.org/10.1007/s10995-016-2138-2 systematic review
- Freeman, S. E., Reznik, J., Jain, M., Sokol, E. E., Manning, D., Rohde, H., Loverich, T. M., & Lawler, J. M. (2025). Perinatal Mental Health Interventions with a Parent–Child Relational Component: A Systematic Review of the Effects on Mothers and Dyads. Clinical Child and Family Psychology Review, 28(3), 650–683. https://doi.org/10.1007/s10567-025-00535-5 https://doi.org/10.1007/s10567-025-00535-5 systematic review
- Al Sager, A., Goodman, S. H., Jeong, J., Bain, P. A., & Ahun, M. N. (2024). Effects of multi-component parenting and parental mental health interventions on early childhood development and parent outcomes: a systematic review and meta-analysis. The Lancet Child & Adolescent Health, 8(9), 656–669. https://doi.org/10.1016/s2352-4642(24)00134-2 https://doi.org/10.1016/s2352-4642(24)00134-2 systematic review and meta-analysis of RCTs
- Padrutt, E. R., Stallworthy, I., DeJoseph, M., Wilson, S., & Berry, D. (2026). Maternal postnatal depression and sensitive parenting: Considering developmental timing with a causally informative approach. Developmental Psychology. https://doi.org/10.1037/dev0002273 https://doi.org/10.1037/dev0002273 prospective longitudinal cohort (causal-inference modelling)
- Alves, C. R. L., Seibel, B. L., Gaspardo, C. M., Altafim, E. R. P., & Linhares, M. B. M. (2024). Home-visiting Parenting Programs to Improve Mother-Infant Interactions at Early Ages: A Systematic Review. Psychosocial Intervention, 33(2), 117–132. https://doi.org/10.5093/pi2024a7 https://doi.org/10.5093/pi2024a7 systematic review
Your Baby's Brain: How Love, Connection, and Responsive Caregiving Support Development
Understanding the neuroscience of attachment, emotional security, and your baby's developing nervous system.
The short version
Babies need connection
Babies cannot reliably feed, stay warm, or calm themselves without adults. Warm, responsive care is part of how they stay safe and how their brains and bodies develop.
Crying is communication
A cry is a signal. Babies cry a lot in the first weeks, and many crying spells have no single cause that anyone can find.
Calm grows slowly
The parts of the brain that help with calming and self-control keep maturing for years. A baby who cannot settle alone is not failing; the brain is developing as expected.
Explore the brain: five key parts
Choose a part, or tap it on the drawing, to read what it does, what is known about it in babies and children, and how everyday caregiving connects to it. The drawing is a simplified, see-through side view. It is a schematic, not an anatomy atlas, and the real brain parts work together as networks rather than alone.
Amygdala Emerging
amygdala (a small almond-shaped cluster of nerve cells deep in the side of the brain)
- What it does
- It helps the brain judge how important or emotionally meaningful something is, including possible threats, and it takes part in learning from emotional experience and in stress responses. It is not simply a "fear center"; it works as one part of wider networks.
- In babies and children
- It is already active in infancy. A brain-imaging study of 80 children aged 3 months to 5 years (different children were scanned at each age) found that many of the amygdala's connections to sensory and deeper brain regions already looked like those of older children, while the shift in its connections with the front of the brain had not yet appeared by age 5. Researchers describe the amygdala and prefrontal cortex as developing together over a long period, which gives caregivers a long time to help.
- Caregiving connection
- Researchers think caregiving can shape how these circuits develop, but this is mainly a theory supported by animal work and by studies of severe adversity. We do not know of evidence that ordinary parenting stress or imperfect days change a child's amygdala.
Prefrontal cortex Well-established
prefrontal cortex (the front part of the brain, behind the forehead)
- What it does
- It supports planning, holding information in mind, and managing impulses and emotions.
- In babies and children
- Its nerve cells form before birth, but its connections keep being refined, with extra connections first made and then trimmed, until roughly the third decade of life. Imaging also shows quick change in the first year of life, so it is "slow to finish" rather than "not working".
- Caregiving connection
- This is one reason young children rely on adults to help them calm down: their own regulation systems are still being built. That is normal development, not a failure of the child or of the parent.
Hippocampus Emerging
hippocampus (a seahorse-shaped structure in the temporal lobe, central to memory)
- What it does
- It is central to forming memories and remembering their context, such as where and when something happened.
- In babies and children
- It develops over a long period. Some memory abilities appear in the first year, and richer memory for context appears to emerge around 18 to 24 months and keep refining into adolescence.
- Caregiving connection
- In one US study of 127 children (a group enriched for preschool depression) scanned from preschool to early adolescence, children whose mothers were observed to be more supportive in the preschool years showed faster growth of this region, and that growth was linked to better emotion regulation later. A smaller Canadian study of 33 mother-infant pairs found the opposite direction: more maternal positivity in infancy went with smaller hippocampal volumes at age 10. So the evidence is mixed. Brain-region size is not a measure of memory or of parenting success, and this research is about associations, not proof that love "grows" the brain.
Hypothalamus Well-established
hypothalamus (a small region at the base of the brain that helps keep the body's internal conditions steady)
- What it does
- It takes in signals from the body, the surroundings, and other brain areas, and helps coordinate basic functions, including hormone release and automatic body responses. It helps coordinate; it does not "control emotions" by itself.
- In the stress response
- Neurons in one part of the hypothalamus release a signal called CRH, which starts the body's main hormonal stress system (see the HPA axis below).
- Caregiving connection
- Babies are still learning to keep temperature, feeding rhythm, and arousal steady, so they rely on caregivers for much of it. This is general physiology rather than a single study's finding.
Pituitary gland Well-established
pituitary gland (a pea-sized gland hanging below the hypothalamus, often called the body's "master gland")
- What it does
- It releases hormones into the blood. In the stress system it responds to CRH by releasing ACTH, which signals the adrenal glands.
- Caregiving connection
- It is part of the hormonal chain that the next section explains.
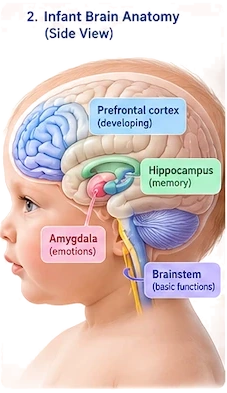
The stress hormone chain (HPA axis)
Well-established The HPA axis (hypothalamic-pituitary-adrenal axis, the body's main hormonal stress system) is a normal, adaptive system that everyone has. It is not a sign that something is wrong.
- Hypothalamus. When the brain detects a real or expected demand, it releases CRH (corticotropin-releasing hormone, a chemical messenger).
- Pituitary gland. CRH tells it to release ACTH (adrenocorticotropic hormone) into the blood.
- ACTH travels in the blood to the adrenal glands.
- Adrenal glands (small glands on top of the kidneys) release cortisol, which helps the body mobilize energy for the demand.
- Negative feedback. Cortisol also signals back to the brain to turn the system down once the demand has passed.
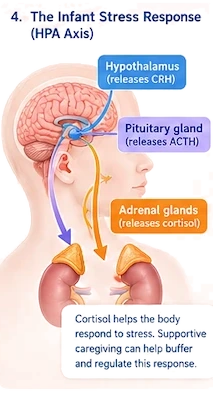
What this means for babies Emerging
Babies' stress systems are working in the first year. In a review of 47 studies of infants aged 3 to 18 months, laboratory stressors such as brief separation were linked with only a small average rise in cortisol, and only the separation studies showed a consistent rise. Measurement methods varied widely. Scientists do not yet have a clear picture of how this changes across infancy.
Does caregiving change it? Emerging
Researchers think warm, responsive care can help calm a child's body as well as their feelings. Some studies link caregiving to babies' cortisol or heart measures. But a meta-analysis of parenting programs found no overall effect on child cortisol, and another found no clear overall link between early life stress and cortisol. The human evidence is small and inconsistent, and the trial that found a link studied families involved with child protective services, partly through correlation. So we say "may help buffer", not "lowers cortisol".
The body's autopilot (autonomic nervous system) and the vagus nerve
Well-established The autonomic nervous system (the body's automatic controls for heart rate, breathing, digestion, and more) has a sympathetic part, which generally prepares the body for action, and a parasympathetic part, which supports rest and recovery. They work together to keep the body in balance. That is a useful simplification, not an on-off switch. The newborn's autonomic system is still maturing, and a baby's heart-rate patterns reflect this.
- Brainstem (the base of the brain, where automatic functions are coordinated).
- Vagus nerve (the tenth cranial nerve, purple line): the main nerve of the parasympathetic system. It carries signals in both directions between the brainstem and organs, including the heart, lungs, and gut.
- Sympathetic nerves (orange dashed line, running alongside the spine) generally raise arousal.
- Lungs.
- Heart. Both branches affect heart rate.
- Gut (digestive tract).
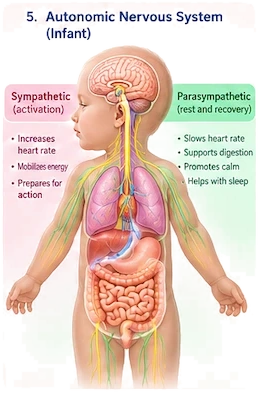
Heart rhythms between parent and baby Emerging
In 12 studies of mothers and children (mostly beyond infancy), heart-related rhythms moved together to a modest degree during interaction. Larger reviews find this "synchrony" varies by age and context and is not simply good or bad. One study of at-risk infants found that babies' heart rhythm changed around moments of shared positive play with their mothers. Evidence is correlational and effects are modest.
Calming together
When you hold, rock, or talk softly to a baby, it often helps a still-immature system settle. This is called co-regulation (a caregiver helping a child's body and feelings settle). Babies cannot do this alone yet. In one study, babies from 5 to 18 months relied more on regulation shared with a caregiver as they grew, and children take on more of it themselves over the preschool years and beyond.
Neuroplasticity: the brain changes with experience
Well-established Neuroplasticity (the brain's ability to change its connections in response to experience). Early in life the brain makes many more synapses (connections between nerve cells) than it will keep. Connections that are used and strengthened tend to be kept, while others are trimmed, a process called pruning. Much of the detail on pruning and sensitive periods comes from animal studies, and the human evidence on early adversity is mostly about severe deprivation.
Sensitive periods
Plasticity is especially high in early windows called sensitive periods. This is why early experience matters. But in humans these windows are graded and flexible, not doors that slam shut at a certain age, and outcomes after early difficulty are described as probabilities, not certainties.
The brain grows fastest early, and keeps changing
The brain develops fastest in the first two years, and development goes on at a slower pace afterwards. Genes and experiences all contribute, and parents do not "build" a baby's brain alone. The capacity to change continues through life, though it is usually greatest early.
Your baby's development over time
Children develop at different speeds. The ages below come from the US CDC and American Academy of Pediatrics milestone checklists, which list skills that at least three out of four children are expected to show by that age. They are tools for noticing and talking with your child's doctor, not tests every child passes on schedule. Choose an age to read more.
Pregnancy: the senses start to listen
- Sensory. Late in pregnancy a baby can hear. In a small imaging study of 9 pregnant women at 33 to 38 weeks, most fetuses showed auditory-brain activity when the mother sang. A review of 8 studies found 7 showed newborns had learned sounds presented before birth, but the studies were mostly low quality and used experimental sounds. This does not show that playing music to the belly helps. The studies do not give a reliable week for when hearing begins.
- Attachment. Many parents begin to feel connected to their baby during pregnancy. Not feeling a strong connection yet is common. Studies find only a small to moderate link between feelings in pregnancy and later bonding, so it does not decide how bonding will go.
Newborn: getting to know you
- Sensory and social. Newborns respond to sounds and smells they met before birth or in the first days. By about 7 months, babies' brain responses track their mother's voice more strongly than an unfamiliar speaker's.
- Brain. Brain volume is roughly a third of the adult size around birth, and growth is rapid.
- Emotional regulation. Newborns can only calm themselves a little and rely on caregivers to help. Crying is their main signal, and the amount of fussing and crying varies a great deal between babies.
About 2 to 4 months: social smiles
- Social communication. By about 2 months most babies smile when you talk or smile at them and look at your face. By about 4 months many smile on their own to get your attention and make sounds back.
- Emotional regulation. Crying on average eases after the first six weeks, to a little over an hour a day by 10 to 12 weeks, though babies differ.
About 6 months: taking turns
- Language and social. By about 6 months many babies take turns making sounds with you. Back-and-forth conversation and children's vocabulary seem to grow together.
- Emotional regulation. Between about 5 and 18 months, babies in one study used more regulation shared with their caregiver and less pure self-soothing as they grew. Relying on you is a normal part of how regulation develops.
About 9 to 12 months: you are the one they want
- Attachment. By about 9 months most babies are shy, clingy, or fearful around strangers and react when a caregiver leaves. Children differ a lot in how strong this is.
- Social communication. Joint attention (sharing focus on an object with another person) emerges around this age.
- Language. By 12 months many call a parent "mama" or "dada" and wave.
About 18 months: exploring with a safe base
- Attachment and autonomy. By about 18 months most children move away to explore but check that a caregiver is close.
- Language. A few words by 15 to 18 months. Children vary widely.
- Executive function (mental skills for holding information in mind and stopping an impulse). Simple executive-function skills can be tested by around 18 months, and they keep developing through the preschool years.
2 years: "mine!" and "no!"
- Autonomy. Toddlers say "no" early as a word, but understand it as a logical idea only after about age two. Using "no" and having strong preferences fits ordinary toddler growth, though these studies tested understanding of the word rather than autonomy itself.
- Emotional regulation. Tantrums are common. In a parent-report survey of 861 children aged 1 to 5, older children had fewer but longer tantrums than younger ones.
- Language. Two-word combinations by about 24 months.
3 years: calming down with help
- Attachment. By about 3 years most children calm within about 10 minutes after a caregiver leaves.
- Executive function and self-control. Impulse control increased steadily between ages 2.5 and 6.5 in one study, with growth slowing as children got older. In that parent-report study, more sensitive parenting went with higher starting self-control. Parents also respond to their child's behavior, so this is an association. Most children gain behavioral self-regulation rapidly in early childhood.
5 years: conversations and friends
- Language. Conversations with several back-and-forth turns are expected between 3 and 5 years.
- Executive function and social life. Executive function at 3 to 5 years is linked with how well peers accept a child (an association). The prefrontal cortex is still maturing, so regulation continues to grow well into adolescence.
Ages are approximate and described by milestone checklists, not by exact onset studies. If you are worried about your child's development, ask your pediatrician; early support helps.
What is still uncertain
Limits of this evidence.
- Much of the neuroscience of caregiving comes from animal studies and from studies of severe adversity. Evidence about ordinary family life is thinner.
- Most findings are associations. Children also shape their parents' behavior, and shared genes and circumstances can look like parenting effects.
- Many studies come from a limited range of countries, and families everywhere care for babies in many good ways.
- The drawings here are simplified schematics. A professional medical illustrator and a pediatric neuroscientist should review them before wider use.
You are part of the environment, not the whole of it
Nothing on this page means a parent has to be perfect, or that a mother alone builds her baby's brain. Genes, health, family circumstances, and many things nobody chooses all shape development. Caregivers are an important part of that environment, and so is the support around them.
Looking after the person who looks after the baby is part of looking after the baby. When a parent is struggling, for example with depression, very broken sleep, or little help, caregiving can be a little harder on average (the link with depression is small). Many parents in those situations care warmly and well. One large study found the link between depression and sensitive parenting was largely explained by other circumstances in families' lives, which is one reason support matters. In one Australian study, support from a partner or family was linked with better parent-baby interaction in mothers who had depressive symptoms. Asking for help, resting, and getting treatment are not selfish. They are part of good care. More on this in Secure Attachment
Support for mothers after birth: Postpartum Support International
Postpartum Support International (PSI) offers free help for pregnancy and postpartum mental health, for mothers and for other parents. You do not need to be in crisis to reach out. Feeling overwhelmed, anxious, sad, or not like yourself after a baby is common and treatable, and you will always hear back from a person, not an AI program.
- Call the PSI HelpLine: 1-800-944-4773 (press 1 for Spanish, 2 for English)
- Text in English: text "Help" to 800-944-4773
- Text in Spanish: 971-203-7773
- App: download "Connect by PSI" in your app store
The HelpLine is free and confidential. You can leave a message any time, and calls and texts are returned every day, from 8 am to 11 pm Eastern time. It gives information, support, and local resources. It is not a crisis line and does not handle emergencies. About the HelpLine
References
All sources are peer-reviewed journal articles or professional policy statements published 2016 to 2026. Select a number above to jump to its reference, and a DOI to open the original article. APA 7th edition.
- Burkart, J. M., Cerrito, P., Natalucci, G., & van Schaik, C. P. (2025). Cooperative Breeding as a Likely Early Catalyst of Human Evolution. Evolutionary Anthropology: Issues, News, and Reviews, 34(3), e70016. https://doi.org/10.1002/evan.70016 https://doi.org/10.1002/evan.70016 review (evolutionary anthropology)
- Hodel, A. S. (2018). Rapid infant prefrontal cortex development and sensitivity to early environmental experience. Developmental Review, 48, 113–144. https://doi.org/10.1016/j.dr.2018.02.003 https://doi.org/10.1016/j.dr.2018.02.003 narrative review (neuroimaging)
- Wolke, D., Bilgin, A., & Samara, M. (2017). Systematic review and meta-analysis: Fussing and crying durations and prevalence of colic in infants. The Journal of Pediatrics, 185, 55-61.e4. https://doi.org/10.1016/j.jpeds.2017.02.020 https://doi.org/10.1016/j.jpeds.2017.02.020 meta-analysis
- Zeevenhooven, J., Browne, P. D., L'Hoir, M. P., de Weerth, C., & Benninga, M. A. (2018). Infant colic: mechanisms and management. Nature Reviews Gastroenterology & Hepatology, 15(8), 479-496. https://doi.org/10.1038/s41575-018-0008-7 https://doi.org/10.1038/s41575-018-0008-7 narrative review
- Kolk, S. M., & Rakic, P. (2022). Development of prefrontal cortex. Neuropsychopharmacology, 47(1), 41-57. https://doi.org/10.1038/s41386-021-01137-9 https://doi.org/10.1038/s41386-021-01137-9 narrative review (human and animal)
- Šimić, G., Tkalčić, M., Vukić, V., Mulc, D., Španić, E., Šagud, M., Olucha-Bordonau, F. E., Vukšić, M., & R. Hof, P. (2021). Understanding Emotions: Origins and Roles of the Amygdala. Biomolecules, 11(6), 823. https://doi.org/10.3390/biom11060823 https://doi.org/10.3390/biom11060823 narrative review · animal research
- Gabard-Durnam, L., O’Muircheartaigh, J., Dirks, H., Dean, D., Tottenham, N., & Deoni, S. (2018). Human amygdala functional network development: A cross-sectional study from 3 months to 5 years of age. Developmental Cognitive Neuroscience, 34, 63-74. https://doi.org/10.1016/j.dcn.2018.06.004 https://doi.org/10.1016/j.dcn.2018.06.004 cross-sectional neuroimaging (resting-state fMRI)
- Tottenham, N., & Gabard-Durnam, L. J. (2017). The developing amygdala: a student of the world and a teacher of the cortex. Current Opinion in Psychology, 17, 55-60. https://doi.org/10.1016/j.copsyc.2017.06.012 https://doi.org/10.1016/j.copsyc.2017.06.012 narrative review (theoretical) · animal research
- Tottenham, N. (2020). Early Adversity and the Neotenous Human Brain. Biological Psychiatry, 87(4), 350-358. https://doi.org/10.1016/j.biopsych.2019.06.018 https://doi.org/10.1016/j.biopsych.2019.06.018 narrative review
- Larsen, B., & Luna, B. (2018). Adolescence as a neurobiological critical period for the development of higher-order cognition. Neuroscience & Biobehavioral Reviews, 94, 179-195. https://doi.org/10.1016/j.neubiorev.2018.09.005 https://doi.org/10.1016/j.neubiorev.2018.09.005 narrative review
- Gómez, R. L., & Edgin, J. O. (2016). The extended trajectory of hippocampal development: Implications for early memory development and disorder. Developmental Cognitive Neuroscience, 18, 57-69. https://doi.org/10.1016/j.dcn.2015.08.009 https://doi.org/10.1016/j.dcn.2015.08.009 narrative review · animal research
- Luby, J. L., Belden, A., Harms, M. P., Tillman, R., & Barch, D. M. (2016). Preschool is a sensitive period for the influence of maternal support on the trajectory of hippocampal development. Proceedings of the National Academy of Sciences, 113(20), 5742-5747. https://doi.org/10.1073/pnas.1601443113 https://doi.org/10.1073/pnas.1601443113 longitudinal cohort (neuroimaging)
- Bernier, A., Dégeilh, F., Leblanc, É., Daneault, V., Bailey, H. N., & Beauchamp, M. H. (2019). Mother–Infant Interaction and Child Brain Morphology: A Multidimensional Approach to Maternal Sensitivity. Infancy, 24(2), 120-138. https://doi.org/10.1111/infa.12270 https://doi.org/10.1111/infa.12270 longitudinal cohort (neuroimaging)
- Fong, H., Zheng, J., & Kurrasch, D. (2023). The structural and functional complexity of the integrative hypothalamus. Science, 382(6669), 388-394. https://doi.org/10.1126/science.adh8488 https://doi.org/10.1126/science.adh8488 narrative review
- Herman, J. P., McKlveen, J. M., Ghosal, S., Kopp, B., Wulsin, A., Makinson, R., Scheimann, J., & Myers, B. (2016). Regulation of the Hypothalamic‐Pituitary‐Adrenocortical Stress Response. Comprehensive Physiology, 6(2), 603-621. https://doi.org/10.1002/cphy.c150015 https://doi.org/10.1002/cphy.c150015 narrative review · animal research
- Sapolsky, R. M. (2021). Glucocorticoids, the evolution of the stress-response, and the primate predicament. Neurobiology of Stress, 14, 100320. https://doi.org/10.1016/j.ynstr.2021.100320 https://doi.org/10.1016/j.ynstr.2021.100320 narrative review
- Puhakka, I. J. A., & Peltola, M. J. (2020). Salivary cortisol reactivity to psychological stressors in infancy: A meta-analysis. Psychoneuroendocrinology, 115, 104603. https://doi.org/10.1016/j.psyneuen.2020.104603 https://doi.org/10.1016/j.psyneuen.2020.104603 meta-analysis (systematic review)
- Rattaz, V., Puglisi, N., Tissot, H., & Favez, N. (2022). Associations between parent–infant interactions, cortisol and vagal regulation in infants, and socioemotional outcomes: A systematic review. Infant Behavior and Development, 67, 101687. https://doi.org/10.1016/j.infbeh.2022.101687 https://doi.org/10.1016/j.infbeh.2022.101687 systematic review
- Garnett, M., Bernard, K., Hoye, J., Zajac, L., & Dozier, M. (2020). Parental sensitivity mediates the sustained effect of Attachment and Biobehavioral Catch-up on cortisol in middle childhood: A randomized clinical trial. Psychoneuroendocrinology, 121, 104809. https://doi.org/10.1016/j.psyneuen.2020.104809 https://doi.org/10.1016/j.psyneuen.2020.104809 RCT with long-term follow-up
- Martins, R. C., Blumenberg, C., Tovo-Rodrigues, L., Gonzalez, A., & Murray, J. (2020). Effects of parenting interventions on child and caregiver cortisol levels: systematic review and meta-analysis. BMC Psychiatry, 20(1), 370. https://doi.org/10.1186/s12888-020-02777-9 https://doi.org/10.1186/s12888-020-02777-9 systematic review and meta-analysis of RCTs
- Fogelman, N., & Canli, T. (2018). Early life stress and cortisol: A meta-analysis. Hormones and Behavior, 98, 63-76. https://doi.org/10.1016/j.yhbeh.2017.12.014 https://doi.org/10.1016/j.yhbeh.2017.12.014 meta-analysis
- Wehrwein, E. A., Orer, H. S., & Barman, S. M. (2016). Overview of the Anatomy, Physiology, and Pharmacology of the Autonomic Nervous System. Comprehensive Physiology, 6(3), 1239-1278. https://doi.org/10.1002/cphy.c150037 https://doi.org/10.1002/cphy.c150037 narrative review
- Patural, H., Pichot, V., Roche, F., & Giraud, A. (2023). Why, when and how to assess autonomic nervous system maturation in neonatal care units: A practical overview. Neurophysiologie Clinique, 53(2), 102855. https://doi.org/10.1016/j.neucli.2023.102855 https://doi.org/10.1016/j.neucli.2023.102855 narrative review
- Breit, S., Kupferberg, A., Rogler, G., & Hasler, G. (2018). Vagus Nerve as Modulator of the Brain–Gut Axis in Psychiatric and Inflammatory Disorders. Frontiers in Psychiatry, 9, 44. https://doi.org/10.3389/fpsyt.2018.00044 https://doi.org/10.3389/fpsyt.2018.00044 narrative review
- Miller, J. G., Armstrong‐Carter, E., Balter, L., & Lorah, J. (2023). A meta‐analysis of mother–child synchrony in respiratory sinus arrhythmia and contextual risk. Developmental Psychobiology, 65(1), e22355. https://doi.org/10.1002/dev.22355 https://doi.org/10.1002/dev.22355 meta-analysis
- DePasquale, C. E. (2020). A systematic review of caregiver–child physiological synchrony across systems: Associations with behavior and child functioning. Development and Psychopathology, 32(5), 1754-1777. https://doi.org/10.1017/s0954579420001236 https://doi.org/10.1017/s0954579420001236 systematic review
- Lavezzo, L., Bhadra, K., Ceravolo, L., Hüppi, P., Scilingo, E. P., Grandjean, D., Péron, J., Nardelli, M., & Filippa, M. (2026). On human synchrony: A systematic review of the origins of physiological and neural synchrony in parent–infant dyads (0–12 months). Neuroscience & Biobehavioral Reviews, 185, 106622. https://doi.org/10.1016/j.neubiorev.2026.106622 https://doi.org/10.1016/j.neubiorev.2026.106622 systematic review
- Abney, D. H., Sheinkopf, S. J., Mitsven, S. G., Seifer, R., Lester, B. M., Tronick, E. Z., & Messinger, D. S. (2026). Mutual positive engagement with mother is uniquely associated with increases in human infant heart rate variability. Philosophical Transactions of the Royal Society B: Biological Sciences, 381(1959), 20260004. https://doi.org/10.1098/rstb.2026.0004 https://doi.org/10.1098/rstb.2026.0004 longitudinal cohort (exploratory observational)
- Atkinson, N. H., Jean, A. D. L., & Stack, D. M. (2021). Emotion regulation from infancy to toddlerhood: Individual and group trajectories of full-term and very-low-birthweight preterm infants. Infancy, 26(4), 570-595. https://doi.org/10.1111/infa.12405 https://doi.org/10.1111/infa.12405 longitudinal observational cohort
- Hendry, A., & Holmboe, K. (2026). Parent-reported infant emotion regulation and executive functions predict preschool executive function skills. Developmental Psychology. Advance online publication. https://doi.org/10.1037/dev0002229 https://doi.org/10.1037/dev0002229 longitudinal cohort (parent report)
- Grossman, P. (2023). Fundamental challenges and likely refutations of the five basic premises of the polyvagal theory. Biological Psychology, 180, 108589. https://doi.org/10.1016/j.biopsycho.2023.108589 https://doi.org/10.1016/j.biopsycho.2023.108589 narrative review (critical)
- Taylor, E. W., Wang, T., & Leite, C. A. C. (2022). An overview of the phylogeny of cardiorespiratory control in vertebrates with some reflections on the ‘Polyvagal Theory’. Biological Psychology, 172, 108382. https://doi.org/10.1016/j.biopsycho.2022.108382 https://doi.org/10.1016/j.biopsycho.2022.108382 narrative review (comparative physiology)
- Porges, S. W. (2022). Polyvagal Theory: A Science of Safety. Frontiers in Integrative Neuroscience, 16, 871227. https://doi.org/10.3389/fnint.2022.871227 https://doi.org/10.3389/fnint.2022.871227 narrative review (theory paper by the theory's author)
- Neuhuber, W. L., & Berthoud, H. R. (2022). Functional anatomy of the vagus system: How does the polyvagal theory comply? Biological Psychology, 174, 108425. https://doi.org/10.1016/j.biopsycho.2022.108425 https://doi.org/10.1016/j.biopsycho.2022.108425 narrative review (anatomy; critical appraisal)
- Faust, T. E., Gunner, G., & Schafer, D. P. (2021). Mechanisms governing activity-dependent synaptic pruning in the developing mammalian CNS. Nature Reviews Neuroscience, 22(11), 657-673. https://doi.org/10.1038/s41583-021-00507-y https://doi.org/10.1038/s41583-021-00507-y narrative review (mostly animal mechanisms)
- Reh, R. K., Dias, B. G., Nelson, C. A., Kaufer, D., Werker, J. F., Kolb, B., Levine, J. D., & Hensch, T. K. (2020). Critical period regulation across multiple timescales. Proceedings of the National Academy of Sciences, 117(38), 23242-23251. https://doi.org/10.1073/pnas.1820836117 https://doi.org/10.1073/pnas.1820836117 narrative review · animal research
- Nelson, C. A., & Gabard-Durnam, L. J. (2020). Early Adversity and Critical Periods: Neurodevelopmental Consequences of Violating the Expectable Environment. Trends in Neurosciences, 43(3), 133-143. https://doi.org/10.1016/j.tins.2020.01.002 https://doi.org/10.1016/j.tins.2020.01.002 narrative review
- Gilmore, J. H., Knickmeyer, R. C., & Gao, W. (2018). Imaging structural and functional brain development in early childhood. Nature Reviews Neuroscience, 19(3), 123-137. https://doi.org/10.1038/nrn.2018.1 https://doi.org/10.1038/nrn.2018.1 narrative review (imaging)
- Sampaio-Baptista, C., & Johansen-Berg, H. (2017). White Matter Plasticity in the Adult Brain. Neuron, 96(6), 1239-1251. https://doi.org/10.1016/j.neuron.2017.11.026 https://doi.org/10.1016/j.neuron.2017.11.026 narrative review (human neuroimaging and animal)
- King, L. S., Guyon-Harris, K. L., Valadez, E. A., Radulescu, A., Fox, N. A., Nelson, C. A., Zeanah, C. H., & Humphreys, K. L. (2023). A Comprehensive Multilevel Analysis of the Bucharest Early Intervention Project: Causal Effects on Recovery From Early Severe Deprivation. American Journal of Psychiatry, 180(8), 573-583. https://doi.org/10.1176/appi.ajp.20220672 https://doi.org/10.1176/appi.ajp.20220672 RCT (long-term follow-up)
- Vanderwert, R. E., Zeanah, C. H., Fox, N. A., & Nelson, C. A. (2016). Normalization of EEG activity among previously institutionalized children placed into foster care: A 12-year follow-up of the Bucharest Early Intervention Project. Developmental Cognitive Neuroscience, 17, 68-75. https://doi.org/10.1016/j.dcn.2015.12.004 https://doi.org/10.1016/j.dcn.2015.12.004 RCT follow-up (EEG)
- Zubler, J. M., Wiggins, L. D., Macias, M. M., Whitaker, T. M., Shaw, J. S., Squires, J. K., Pajek, J. A., Wolf, R. B., Slaughter, K. S., Broughton, A. S., Gerndt, K. L., Mlodoch, B. J., & Lipkin, P. H. (2022). Evidence-informed milestones for developmental surveillance tools. Pediatrics, 149(3), Article e2021052138. https://doi.org/10.1542/peds.2021-052138 https://doi.org/10.1542/peds.2021-052138 policy statement (AAP-convened expert working group; literature-informed consensus; not a systematic review or RCT) · policy statement
- Goldberg, E., McKenzie, C. A., de Vrijer, B., Eagleson, R., & de Ribaupierre, S. (2020). Fetal response to a maternal internal auditory stimulus. Journal of Magnetic Resonance Imaging, 52(1), 139-145. https://doi.org/10.1002/jmri.27033 https://doi.org/10.1002/jmri.27033 cohort (fetal task fMRI)
- Movalled, K., Sani, A., Nikniaz, L., & Ghojazadeh, M. (2023). The impact of sound stimulations during pregnancy on fetal learning: A systematic review. BMC Pediatrics, 23(1), Article 183. https://doi.org/10.1186/s12887-023-03990-7 https://doi.org/10.1186/s12887-023-03990-7 systematic review
- Trombetta, T., Giordano, M., Santoniccolo, F., Vismara, L., Della Vedova, A. M., & Rollè, L. (2021). Pre-natal Attachment and Parent-To-Infant Attachment: A Systematic Review. Frontiers in Psychology, 12, 620942. https://doi.org/10.3389/fpsyg.2021.620942 https://doi.org/10.3389/fpsyg.2021.620942 systematic review
- Jessen, S., Orf, M., & Obleser, J. (2025). Neural tracking of the maternal voice in the infant brain. The Journal of Neuroscience, 45(50), Article e0646252025. https://doi.org/10.1523/JNEUROSCI.0646-25.2025 https://doi.org/10.1523/jneurosci.0646-25.2025 EEG experiment
- Schaal, B., Saxton, T. K., Loos, H., Soussignan, R., & Durand, K. (2020). Olfaction scaffolds the developing human from neonate to adolescent and beyond. Philosophical Transactions of the Royal Society B: Biological Sciences, 375(1800), Article 20190261. https://doi.org/10.1098/rstb.2019.0261 https://doi.org/10.1098/rstb.2019.0261 narrative review
- Donnelly, S., & Kidd, E. (2021). The longitudinal relationship between conversational turn-taking and vocabulary growth in early language development. Child Development, 92(2), 609-625. https://doi.org/10.1111/cdev.13511 https://doi.org/10.1111/cdev.13511 longitudinal cohort (daylong audio recordings)
- Van Hulle, C. A., Moore, M. N., Lemery-Chalfant, K., Goldsmith, H. H., & Brooker, R. J. (2017). Infant stranger fear trajectories predict anxious behaviors and diurnal cortisol rhythm during childhood. Development and Psychopathology, 29(3), 1119-1130. https://doi.org/10.1017/s0954579417000311 https://doi.org/10.1017/s0954579417000311 longitudinal cohort
- Mateus, V., Santos, A. C., Ganho-Ávila, A., Sobral, M., Osório, A., & Cruz, S. (2026). Neural correlates of joint attention in infants aged 8-24 months: A systematic review. Developmental Cognitive Neuroscience, 78, Article 101678. https://doi.org/10.1016/j.dcn.2026.101678 https://doi.org/10.1016/j.dcn.2026.101678 systematic review
- Gottwald, J. M., Achermann, S., Marciszko, C., Lindskog, M., & Gredebäck, G. (2016). An embodied account of early executive-function development. Psychological Science, 27(12), 1600-1610. https://doi.org/10.1177/0956797616667447 https://doi.org/10.1177/0956797616667447 cross-sectional experimental study
- Feiman, R., Mody, S., Sanborn, S., & Carey, S. (2017). What Do You Mean, No? Toddlers’ Comprehension of Logical “No” and “Not”. Language Learning and Development, 13(4), 430-450. https://doi.org/10.1080/15475441.2017.1317253 https://doi.org/10.1080/15475441.2017.1317253 experimental comprehension study (3 experiments)
- Reuter, T., Feiman, R., & Snedeker, J. (2018). Getting to No: Pragmatic and Semantic Factors in Two- and Three-Year-Olds' Understanding of Negation. Child Development, 89(4), e364-e381. https://doi.org/10.1111/cdev.12858 https://doi.org/10.1111/cdev.12858 experimental comprehension study (2 experiments)
- Van den Akker, A. L., Hoffenaar, P., & Overbeek, G. (2022). Temper Tantrums in Toddlers and Preschoolers: Longitudinal Associations with Adjustment Problems. Journal of Developmental & Behavioral Pediatrics, 43(7), 409-417. https://doi.org/10.1097/dbp.0000000000001071 https://doi.org/10.1097/dbp.0000000000001071 cross-sectional survey plus 1-year follow-up (subsample)
- Geeraerts, S. B., Endendijk, J. J., Deković, M., Huijding, J., Deater-Deckard, K., & Mesman, J. (2021). Inhibitory Control Across the Preschool Years: Developmental Changes and Associations with Parenting. Child Development, 92(1), 335-350. https://doi.org/10.1111/cdev.13426 https://doi.org/10.1111/cdev.13426 longitudinal cohort (4 annual waves)
- Montroy, J. J., Bowles, R. P., Skibbe, L. E., McClelland, M. M., & Morrison, F. J. (2016). The development of self-regulation across early childhood. Developmental Psychology, 52(11), 1744-1762. https://doi.org/10.1037/dev0000159 https://doi.org/10.1037/dev0000159 longitudinal cohort (3 samples)
- Stucke, N. J., & Doebel, S. (2024). Early childhood executive function predicts concurrent and later social and behavioral outcomes: A review and meta-analysis. Psychological Bulletin, 150(10), 1178-1206. https://doi.org/10.1037/bul0000445 https://doi.org/10.1037/bul0000445 meta-analysis
- Bernard, K., Nissim, G., Vaccaro, S., Harris, J. L., & Lindhiem, O. (2018). Association between maternal depression and maternal sensitivity from birth to 12 months: a meta-analysis. Attachment & Human Development, 20(6), 578–599. https://doi.org/10.1080/14616734.2018.1430839 https://doi.org/10.1080/14616734.2018.1430839 meta-analysis
- Padrutt, E. R., Stallworthy, I., DeJoseph, M., Wilson, S., & Berry, D. (2026). Maternal postnatal depression and sensitive parenting: Considering developmental timing with a causally informative approach. Developmental Psychology. https://doi.org/10.1037/dev0002273 https://doi.org/10.1037/dev0002273 prospective longitudinal cohort (causal-inference modelling)
- MacMillan, K. K., Lewis, A. J., Watson, S. J., Bourke, D., & Galbally, M. (2021). Maternal social support, depression and emotional availability in early mother-infant interaction: Findings from a pregnancy cohort. Journal of Affective Disorders, 292, 757–765. https://doi.org/10.1016/j.jad.2021.05.048 https://doi.org/10.1016/j.jad.2021.05.048 prospective pregnancy cohort
You and your partner's brain
Becoming a parent changes the brain, and not only for the person who's pregnant. Every kind of family, two moms, two dads, a mom and a dad, a single parent with a support person, goes through this rewiring together.

The pregnant brain
A 2017 study in Nature Neuroscience found that pregnancy reshapes gray matter in areas involved in understanding others, changes that lasted at least two years and were linked to the parent's attachment to their baby. Researchers see this as specialization, not loss.
The caregiving brain
Brains change through caregiving, too. A 2014 study in PNAS found that fathers who were primary caregivers, including gay fathers raising children together, showed parenting brain networks that resembled those of mothers. Hands-on time builds the parent brain.
Partners get depressed too
About 1 in 10 fathers experience depression during pregnancy or the first year, according to a review in JAMA. When one parent struggles, the other's risk goes up, so check in on each other.
Inside the pregnant brain, week by week
In 2024, researchers published the first detailed map of a human brain through pregnancy. They took 26 MRI scans of one healthy 38-year-old first-time mother, who conceived through IVF and was herself one of the scientists, from three weeks before conception to two years after birth.
- Gray matter, the brain's outer layer of nerve cells, gradually thinned as pregnancy progressed in about 80% of the 400 brain regions measured, then partly rebounded after birth. Networks for attention and sensing the body were among the most affected.
- White matter, the wiring that connects brain regions, grew stronger through the first two trimesters, then returned to its starting level after birth.
- The changes happened almost week by week and tracked pregnancy hormones such as estrogen and progesterone, which rise 100- to 1,000-fold in pregnancy.
- Earlier studies found postpartum gray matter changes still visible 6 years after birth, and traces even decades later.
Researchers see this as a sign that pregnancy is a period of high neuroplasticity: the brain adapting and reorganizing, not breaking down. Many experts compare the gray matter changes to the pruning of adolescence, when the brain trims less-used connections to strengthen important ones, and earlier research linked them to tuning in to a baby's needs.
The hormones behind the changes
Estrogen and progesterone
Surge throughout pregnancy and drive much of the brain's remodeling, then drop sharply after birth.
Oxytocin
Often called the bonding hormone, it supports calm and connection between parent and baby.
Prolactin
Known for milk production, it also shapes caregiving behavior.
Not only pregnancy
Similar brain changes appear in fathers and non-biological caregivers, so hands-on caregiving itself reshapes the brain.
Caring for your changing brain
Stay connected
Friends, family, and support groups lower stress and build resilience.
Practice calm
Breathing exercises and mindfulness support emotional regulation.
Protect sleep
Rest matters for memory and mood; even short naps help counter fatigue.
Keep your mind engaged
Reading, puzzles, or games can support focus and memory.
Is "pregnancy brain" real?
A 2025 systematic review pulled together 31 studies comparing about 1,600 pregnant women with about 1,450 women who weren't pregnant. Here's what they found.
A little, yes
Pregnancy was linked to modest dips in verbal memory and attention. Remembering to do things later (like an appointment) was most affected, and some changes lingered for weeks or months after birth.
Not intelligence
Pregnancy had no effect on intelligence or planning. The changes are small, not a loss of who you are.
Feeling vs. testing
Poor sleep made people feel more forgetful but didn't change how they actually scored on memory tests.
A trade-off
One theory: the body shifts energy toward the baby and toward new parenting skills, like reading emotions and staying alert to possible threats.
Co-parenting from day one
Equal partners
You're not "helping" with your own baby; you're parenting. Both of you can learn to soothe, change, bathe, and feed (with bottles, burping, and settling if the baby is breastfed), and both of you share the planning and worrying that nobody sees.
It matters for children
A review of long-term studies found that children whose fathers were actively engaged had better social, emotional, and behavioral outcomes. Research on the caregiving brain shows hands-on time builds parenting skills in any parent.
It matters for the birthing parent
Feeling supported and treated as a team is one of the strongest protections against perinatal depression and anxiety.
How partners can show up, stage by stage
Whether you're a dad, a co-mom, or another partner, here are ways to share the load and care for the person carrying your baby.
What not to say, and what to say instead
Tap a card.
How couples stay connected after a baby
Research following couples into parenthood has found that relationship satisfaction often dips after a baby arrives. Couples who keep up fondness, stay curious about each other, and repair after arguments tend to weather it better.
Co-regulate
Nervous systems calm each other. A hug, a slower voice, or a hand on the back can bring both of you down a notch before you solve the problem.
Repair fast
Every couple argues. What protects the relationship is coming back: "I was harsh. Can we try again?"
Divide the invisible work
Planning, remembering, and worrying are work too. Name them and share them. The Agreements page can help.
A foundation of mutual support
Family therapists Knudson-Martin and Huenergardt describe four ingredients that let partners truly support each other. Tap each one for a question to talk through together.
Your relationship has a context
Socioculturally attuned family therapy starts from a simple idea: our relationships are shaped by the world around us, and that world isn't neutral. Gender expectations, culture, money, race, work schedules, and family traditions all influence who does what at home and whose needs get noticed.
Share the emotional load
Research shows the job of calming and managing emotions in a relationship often falls on women by default. Mutual support means each partner takes responsibility for their own feelings and how they affect the other.
Respect different styles
Love looks different across cultures. A quieter partner who keeps worries to themselves to avoid burdening others isn't necessarily less attached. Go slowly and find a way of sharing that works for both of you.
Name what's outside your control
Night shifts, money pressure, or a lack of family nearby aren't personal failings. Seeing them clearly helps you face them as a team instead of blaming each other.
Born – 21 years old
Month by month in the first two years, then year by year to adulthood. These are typical patterns, not tests. Every child moves through the same general sequence, each at their own pace.

Birth to 2: month by month

Growing
Connecting
Good to know
Ask your pediatrician if your baby isn't reaching milestones or loses skills they had. The CDC's free Milestone Tracker app can help you keep notes for visits.
Year by year: 3 to 21
Pick an age to see what's typical, what's normal even when it's hard, and when it's worth reaching out.
At any age, it's worth talking to a professional if…
- Your child's behavior or abilities seem very different from other children the same age.
- Your child goes through a big change or a frightening experience, such as a loss, family upheaval, abuse, or a medical emergency.
- Sadness or worry is severe or lasts for weeks.
- You often feel disconnected from or stressed with your child, or you'd simply like support with discipline. Asking for parenting help is a strength.
Things nobody tells you about your baby
See all tenToddler years: autonomy, comfort, and calming take time.
Seven everyday habits for happy kids
These habits, inspired by Sean Covey's book The 7 Habits of Happy Kids, line up with skills research links to children's wellbeing: self-control, planning, empathy, cooperation, and healthy routines. Children learn them best by watching the adults around them. Tap a habit.
A large review of more than 200 school programs that teach these kinds of social and emotional skills found better behavior, fewer emotional difficulties, and higher grades (Durlak et al., 2011).
Ages 3 to 12 and the first-two-years milestones are adapted and paraphrased from Ray, D. C. (Ed.). (2016). A therapist's guide to child development: The extraordinarily normal years. Routledge. See Sources.
Without shame
Mental health conditions are health conditions, not character flaws and not parenting failures. Shame keeps people quiet, and staying quiet keeps them from help that works.

Stigma delays care
A large review in Psychological Medicine found that stigma is one of the main reasons people put off seeking mental health care, and fear of being judged plays a big part.
New parents hide it
Research on postpartum depression shows many parents keep symptoms to themselves because they worry about being seen as a bad parent or about what will happen if they speak up.
Treatment helps both
When a parent gets care, the baby benefits too. Seeking help is part of caring for your family.
What weighs on new parents
Perinatal mental health conditions grow from many roots at once. None of them is a personal failure.

Body
- Hormonal shifts, sleep loss, and physical recovery
- Fertility treatment, pregnancy loss, or a difficult birth

Mind
- Guilt, fear, and shame
- Perfectionism, exhaustion, and the shock of a new identity

Culture
- Celebrity and social media images of "bouncing back"
- Stigma and the myth of the ideal parent

Family
- Bonding that takes time or feels hard
- Changing roles for partners and the whole family
Does any of this sound like you?
Parents with perinatal mood and anxiety conditions often describe thoughts like these. Tap any that feel familiar.
Guilt, not shame, with children
Psychologists draw a useful line between guilt ("I did something bad") and shame ("I am bad"). Guilt tends to motivate repair, like apologizing and making things right. Shame tends to lead to hiding, defensiveness, and anger. So when you correct a child, aim at the behavior, never at who they are.
This matters early. Between about ages 1 and 3, children are learning whether they can trust themselves to do things on their own, or whether to doubt themselves. Shaming toilet accidents, tears, or fears teaches doubt. Calm, matter-of-fact responses teach "I can handle this."
Words that help
Tap a card to see a kinder way to say it.
Talking with children about mental health
Keep it simple and true
"I have an illness called depression. It makes me very tired and sad sometimes. It's not your fault, and doctors are helping me get better."
Say "it's not your fault"
Children often believe they caused a parent's sadness or anger. Tell them directly, and more than once, that they didn't.
Name feelings without judging them
"You're really scared" works better than "Don't be a baby." All feelings are allowed; not all actions are.
Treat help as normal
Talk about counselors the way you talk about dentists: people who help keep us healthy.
When someone tells you they're struggling
Listen first
Thank them for telling you. You don't need to fix it in that moment.
Believe them
Skip "but you have a healthy baby" or "everyone feels that way." Both can make people stop talking.
Offer something concrete
"I'll take the baby Tuesday so you can see someone." Practical help says more than advice.
Point to support
Share a helpline and offer to sit with them while they call.
Your postpartum body, without shame
Your body did something enormous
It grew and birthed a baby, and it keeps changing for months: weight, belly, breasts, skin, hair, and energy. Bodies after birth look all kinds of ways, and none of them is a failure.
Healing comes first
Recovery takes many months, not weeks. Rest, nourishing food, and gentle movement when your provider says you're ready matter far more than "bouncing back."
Watch the comparisons
Filtered "snapback" photos online aren't real life. If your feed leaves you feeling worse about your body, it's okay to mute or unfollow.
When body worries grow
If thoughts about your weight or shape take over your day, or you find yourself restricting food or eating in ways that feel out of control, tell your provider. Support helps, and you deserve it.
Find your village
The weeks after birth can feel isolating, even when you're never alone. Getting out to a parent group, class, or baby playdate can feel like a big step, but it's one of the most protective things you can do. When parents talk honestly about how they feel, you quickly discover that what you're going through is shared by many others. Being heard, and hearing "me too," helps calm the nervous system, and research links social support with lower risk of postpartum depression and anxiety, for you and your baby.
New-parent groups
Small groups that meet weekly with babies in tow, often led by a trained facilitator. In Washington State, PEPS offers groups for expecting parents, newborns, older babies, second-time parents, working moms, single parents, and LGBTQIA+ parents, in person or online, with flexible pricing.
Free online support
Postpartum Support International hosts free online groups, including groups for dads, partners, and specific experiences, in several languages.
In your community
Library baby story times, breastfeeding and WIC groups, hospital classes, faith and cultural communities, parks, and stroller walks are all good places to meet other parents.
Make it easier
Go even if you feel nervous; most parents do. Bring your baby, arrive messy, and leave early if you need to. If a group doesn't feel right, try another. And if anxiety keeps you home, that's worth mentioning to your provider.
How we talk to our kids
The way we speak to children becomes the way they speak to themselves. Our words shape their brains, their sense of worth, and how they handle big feelings, for years to come.
Your voice across the journey
Before
The voice you grew up with often becomes the one that comes out under stress. Noticing your own patterns now, maybe with a therapist, helps you choose which ones to pass on.
Within
By around 24 to 26 weeks, many babies respond to sound, and imaging studies show the fetal brain responds to the mother's voice. Your baby is already learning you.
After
Every day of back-and-forth talk builds the brain's language and emotion circuits, and your tone becomes your child's inner voice.
Through the biopsychosocial lens
Biological
Conversation builds the brain. In one MIT study, the number of back-and-forth conversational turns children had at home, more than the number of words they heard, was linked to activity in a key language area of the brain.
Psychological
Words shape self-worth and emotional skills. Harsh words teach a child "I am bad"; calm correction teaches "I made a mistake and can fix it."
Social
Family culture, stress, and the way parents were raised all shape how we talk. Tired, unsupported parents yell more, so supporting parents is part of protecting kids.
What research tells us
Harsh words hurt
A two-year study of nearly 1,000 families found that shouting, cursing at, or insulting young teens was linked to more depression and behavior problems a year later, and a warm relationship didn't cancel out the effect. Harsh words also tended to make behavior worse, not better.
Emotion coaching helps
Researcher John Gottman and colleagues found that parents who treat a child's emotions as a chance to connect and teach, rather than something to dismiss or punish, have children who regulate their emotions better.
Praise the effort, not the label
Children praised for being "smart" tended to avoid challenges and fall apart after failing. Children praised for effort and strategy kept trying. Even praise heard as toddlers predicted how kids approached challenges five years later.
Secure bonds calm big feelings
In secure parent–child relationships, parents tended to defuse anger with humor, distraction, and naming feelings, and children were more open to being calmed.
Emotion coaching in five steps
- Notice the feeling, including the small ones, before they explode.
- See it as a chance to connect, not a problem to shut down.
- Listen and validate: "That really hurt your feelings."
- Help name it: mad, disappointed, jealous, scared, embarrassed.
- Set limits while solving problems together: "You can be angry. You can't hit. What could you do instead?"
Everyday skills from a parenting classic
Adele Faber and Elaine Mazlish's How to Talk So Kids Will Listen & Listen So Kids Will Talk has helped parents for decades. Its core ideas fit closely with the research on emotion coaching above. Here are a few, in our own words. The skills work for partners and adults too.
Accept feelings first
Listen fully, name the feeling ("You sound really disappointed"), and resist rushing to fix, lecture, or argue. Feelings that are heard tend to soften. It's actions, not feelings, that need limits.
Invite cooperation without nagging
Describe what you see ("The milk is out"), give information ("Milk goes sour outside the fridge"), or say it in a single word. Children are more willing to help when they aren't being blamed.
Alternatives to punishment
Say clearly how you feel and what you expect, show how to make things right, offer a choice, and solve problems together. Discipline becomes teaching, not shaming.
Support independence
Offer small choices, respect that some things are hard, and let children try before stepping in. Struggling a little, with you nearby, builds confidence.
Praise that describes
Instead of "You're so smart," describe what you notice: "You kept trying until the puzzle piece fit." Children learn to see their own effort.
Free children from labels
"The shy one" or "the messy one" can become a role a child lives up to. Show them a new picture of themselves by noticing moments when they act differently.
Want more? The book is widely available in libraries and bookstores, and many communities offer parenting groups based on it.
Guiding behavior in school-age children
Arguing, yelling, refusing, and big reactions are common in school-age children. They're still learning to manage frustration, cope with change, and see other people's points of view, while demands from school, chores, and friends keep growing. Challenging behavior often means a child is overwhelmed and needs help, not that they're "naughty" on purpose.
Tap a topic.
If behavior is intense, ongoing, or affecting daily life at home, school, or with friends, talk with your child's doctor or teacher. Sometimes it's linked to learning differences, anxiety, sensory needs, ADHD, or past hard experiences.
Words that build
Choose an age, then tap a card to see a different way to say it.
Words that wound
Labels
"You're so lazy," "bad," "stupid," or "a brat." Children believe what we call them.
Shaming and comparing
"Why can't you be like your sister?" or mocking a child's feelings or body.
Threats of leaving
"I'll leave you here" or "I'm giving you away." These strike at a child's deepest need for safety.
Dismissing feelings
"Stop crying or I'll give you something to cry about," or "Big kids don't get scared."
Parents have feelings too
Every parent feels big emotions: worry, anger, guilt, sadness, joy. How we handle our own feelings shapes how our children learn to handle theirs. You can't switch emotions off, but you can learn to work with them.
Notice your body
Emotions start in the body, like hunger or thirst. Check in "below the neck": a racing heart, tight shoulders, a heavy chest, a churning stomach.
Name it
Simply putting a feeling into words ("I'm anxious," "I'm sad") helps calm the brain's alarm system, and research shows naming feelings precisely supports well-being.
Look underneath
Guilt, anxiety, and shame can cover deeper feelings like anger or sadness. Overeating, drinking, scrolling, or trying to control everything can be ways of avoiding a feeling. Asking "What am I really feeling?" helps.
Reflect
Ask: "What's bringing this up right now? Is it connected to my own childhood?" We learn to parent from how we were raised, and awareness lets us choose what to keep and what to change.
Tap a feeling to see how it often shows up, and what it may be telling you.
When you feel your temper rising
Anger is a normal, healthy feeling, and every parent feels it. What matters is how we express it: frequent, uncontrolled anger is linked to health problems and family conflict, and harsh words can wound as deeply as actions. These steps help you respond instead of react.
Notice
Catch the early signs. In your body: a racing heart, churning stomach, clenched jaw or fists, a hot face, a louder voice. In your mind: thoughts like "No one ever helps me" or "They're doing this on purpose." Saying "I'm getting angry" to yourself helps.
Pause
Stop before you speak. Count to 10 in your head, or say "I need a minute."
Step away safely
Make sure your child is safe, then leave the room for a few minutes, or hand them to another caregiver.
Breathe slowly
Breathe in for a count of two and out for a count of four; you can do this even if you can't leave. If the noise is overwhelming, cover your ears or use headphones for a moment.
Come back and repair
Return when you're calmer. Your feelings are okay, so apologize for your reaction, not your anger: "I'm sorry I yelled. Next time I'll take a break sooner." Repair builds trust. Add: "Even when I lose my temper, I still love you."
Prevent the blowups before they start
Yelling often backfires: the emotion drowns out the message, it escalates the conflict, it loses impact when it's frequent, and it can leave children feeling unloved. Save a raised voice for real danger. These habits make calm easier.
Spot the hot spots
Notice the moments that blow up again and again, like mornings or bedtime, and plan ahead: lay out clothes the night before, start earlier, or break the routine into small steps.
Keep it simple and steady
Young children do best with predictable routines, one-step directions ("Shoes on, please"), and specific praise when they follow through.
Read the context
Hungry, tired, overstimulated, or a child with sensory or attention challenges? Knowing why behavior happens, and what your child can realistically do, makes it easier not to take it personally.
Do one thing at a time
Trying to answer emails or pay bills while kids need you raises stress for everyone. When you can, just be with them.
Ignore the small stuff
For minor attention-seeking behavior, calmly look away and praise the behavior you want instead. Never ignore aggressive or unsafe behavior.
Let it go, together
Spilled snack? "Oops, let's clean it up together" teaches more than a scolding, and keeps everyone calmer.
Words for heated moments
Tap a card.
Expect what's age-appropriate
Young children's brains are still building self-control. Meltdowns aren't manipulation; they're a skill still growing. Their feelings are always okay, even when their behavior needs a firm limit.
Model calm out loud
Children learn by watching. Try narrating: "I feel frustrated, so I'm going to take a deep breath." You're teaching the skill while you use it.
Why anger builds
Juggling too much, little sleep, money stress, illness, feeling unsupported by a partner, or feeling unappreciated all make anger more likely. Naming the real cause helps you fix it.
Reflect afterward
Once calm, maybe the next day, ask: How important was this? What upset me most? What could I control? Do I need to do something, or can I let it go? Be kind to yourself as you learn.
It can wait
If you're exhausted or stressed, take 10 to 15 minutes for yourself before dealing with a problem. For older children and non-urgent issues, it's fine to talk it through the next day, when everyone is rested.
Lighten it, kindly
Shared humor, silliness, or a playful moment can break tension, as long as it's never teasing or a joke at your child's expense.
For grandparents and every caregiver
These skills help anyone who cares for children. Regular exercise, sleep, and calming practices like meditation or yoga make it easier to stay steady over time.
Lower the pressure
Hunger, exhaustion, and doing too much alone make anyone short-tempered. Sharing the load with a partner, friends, or a parent group helps more than willpower.
When anger feels like too much
Frequent rage or irritability after a baby can be a sign of postpartum depression or anxiety, in any parent. If anger feels hard to control, talk with your provider or a counselor; therapies like CBT help.
Cultures differ in how directly parents speak, and warmth can sound different in different families. The research points to the same core: children thrive when words protect their sense of worth and safety.
Baby to adult
Mental health conditions in parents and children: what they are, what raises and lowers risk, and what can be prevented or softened.
Vulnerability is not destiny
Many mental health conditions run in families. Scientists often describe this with a vulnerability–stress model: some people carry a higher sensitivity (from genes, early experiences, or both), and a condition is more likely to appear when that vulnerability meets heavy stress without enough support. A vulnerability can stay quiet for a lifetime.
That's why prevention focuses on two things you can influence: lowering the load (toxic stress, substances, sleep loss, untreated parental illness) and building protection (warm relationships, routines, skills, early help).
Parents: the most common complication of pregnancy
1 in 5
mothers experience a mental health condition during pregnancy or in the year after birth, making these the most common complication of pregnancy and birth.
23%
of pregnancy-related deaths in the US were caused by mental health conditions, including suicide and overdose, the leading cause in CDC reviews from 36 states. More than 80% of all pregnancy-related deaths were judged preventable.
75%
of people affected never get treatment, often because of shame, cost, distrust, or fear of being judged a "bad mom" or "bad dad."
1 in 10
fathers experience depression during pregnancy or the first year after birth, and it's often missed because it can look like irritability, anger, withdrawal, overworking, or drinking.
When symptoms start
Often begins in the first months after birth
Many conditions appear well after the six-week checkup, so keep asking how you're doing all year.
In one Ontario study, suicides were most common 9 to 12 months after birth
The end of the first year is a time to check in, not to stop checking.
Untreated, it can last years
Without care, symptoms can continue for up to three years. With care, most people recover.
Parents: conditions during pregnancy and after birth
Percentages are approximate shares of pregnant or postpartum women, from the Maternal Mental Health Leadership Alliance.
Why some parents face more risk
These conditions grow from biological, psychological, and social roots together: hormone shifts, the identity changes of becoming a parent, and life stresses like money, housing, and isolation. Some experiences raise the risk further.
Life experiences
- A personal or family history of mental health conditions
- Difficult childhood experiences
- Birth trauma, pregnancy loss, or a baby in the NICU
- Intimate partner violence
- Military service, for service members and spouses
- Disability or poverty
Structural racism
American Indian and Alaska Native, Asian American and Pacific Islander, Black, Latina, and South Asian parents face higher risk, not because of who they are but because of discrimination, exclusion from research, and barriers to culturally fitting care. Black women in particular describe being dismissed or mistreated in health care.
Non-birthing parents
Fathers, partners, and adoptive parents are affected too. As many as 1 in 10 fathers have postpartum depression, and a partner's depression is the strongest predictor. Adoptive and birth parents in adoption can also feel deep grief.
Recovery is the rule
Most perinatal mental health conditions are temporary and treatable. Almost everyone recovers with some combination of these:
Looking for a specialist? See Your care team for how to find a provider trained in perinatal mental health.
Children and teens: what can be influenced
When a child's brain works differently: neurodiversity
No two brains are alike, not even in identical twins. An estimated 15 to 20% of people worldwide are neurodivergent. Neurodivergent isn't a diagnosis; it's a respectful way to describe people whose brains develop or work differently from what's typical. That brings different challenges, and often real strengths, like strong memory, visual-spatial thinking, deep focus, or creativity. Neurodivergence isn't caused by anything a parent did, and it isn't something to "fix." It's something to understand and support.
Tap a card to learn more.
Other differences sometimes included: Down syndrome and other genetic conditions, intellectual disabilities, sensory or auditory processing differences, and some mental health conditions such as OCD. People with these differences may or may not use the word neurodivergent for themselves.
Watch development, gently
Children grow at their own pace, but tracking milestones helps you notice if something needs a closer look. The CDC's free Learn the Signs. Act Early. tools and app make it easy. Pediatricians recommend developmental screening at 9, 18, and 30 months, and autism screening at 18 and 24 months; you can ask for an autism checklist (the M-CHAT) between 16 and 30 months. Some signs appear early, but many differences only become clear in preschool, school, or even middle school, as demands grow.
Trust your instincts
If you're worried, talk with your pediatrician. You don't need to wait for a diagnosis to get help, and asking early is never overreacting.
Free early support
In the US, every state offers free or low-cost early intervention for children under 3 with developmental delays, and public schools provide evaluations and services from age 3, including IEPs and 504 plans. You can request an evaluation yourself. A medical diagnosis doesn't automatically bring school support; the school usually does its own evaluation, so ask early and keep advocating.
Lead with strengths
Notice what your child loves and does well, and build on it. Accommodations, like noise-canceling headphones, visual schedules, or extra time, can unlock what a child can do.
Sensory differences
Many neurodivergent children are extra-sensitive to some sensations, like noise, light, tags, or textures, and seek more of others, like spinning, jumping, or crashing into cushions. Meltdowns are often the body saying "too much." Dimmer lights, quieter rooms, comfortable clothes, a safe space to move, fidgets, and familiar foods can help.
Therapies and treatment
Support is tailored to each child. Options may include speech or occupational therapy, tutoring, parent training, behavioral therapy, and, for ADHD, medication combined with behavioral support. Approaches differ, so ask how a therapy respects your child's comfort, feelings, and choices. Neurodivergent children also have higher rates of sleep problems, anxiety, and some medical conditions, so regular checkups matter.
Talking with your child
Many children already know they think differently. Talk about their diagnosis positively: everyone has strengths and struggles, and understanding their brain helps you get them what they need. Ask how they want to describe themselves, such as "autistic" or "a person with autism," and respect that it may change.
Words that respect
Avoid labels like "high-functioning" or "low-functioning," which judge people by how typical they seem. Every neurodivergent person is different, even with the same diagnosis. Never assume a child is incapable.
Care for yourself too
Raising a child with extra needs can bring joy, worry, and exhaustion. Parent support groups, respite care, and counseling help. Many parents also recognize their own neurodivergence when a child is diagnosed, since these traits often run in families.
Signs worth talking to your pediatrician about
Every child develops at their own pace, and one sign alone doesn't mean something is wrong. These lists can't diagnose anything, but they're good reasons to ask for a developmental check. Tap an age.
If others notice too
When teachers, caregivers, or relatives notice the same things you do in different places, that's worth investigating. And if someone dismisses a concern that keeps nagging at you, it's okay to ask again or get a second opinion.
Speech and language
Some children have trouble understanding language, expressing themselves, or saying sounds clearly. Speech-language therapy helps, and it works best when started early.
Tools that open doors
Voice-to-text, audiobooks, visual schedules, math and money apps, and communication devices can unlock learning and independence.
The whole family
Siblings need attention and their own space to share feelings. Parent training, sibling groups, and respite care help everyone thrive.
Myth check: reversing letters like b and d is common in young children and isn't by itself a sign of dyslexia; dyslexia is mainly about connecting sounds and letters. Autism diagnoses have risen in recent years, partly because of better awareness, screening, and broader criteria.
Getting an evaluation, and everyday supports
About 1 in 6 US children has a developmental disability, so you're far from alone.
Who may be on the team
A developmental pediatrician looks at overall development and medical factors; a child psychologist at thinking, feelings, and behavior; a speech-language pathologist at communication; an occupational therapist at fine motor skills, sensory needs, and daily living; and a physical therapist at movement and coordination.
Routines and visual supports
Predictable routines and picture schedules for things like brushing teeth or bedtime ease anxiety and make transitions smoother. Flexibility can grow slowly from there.
Give time to answer
Use clear, concrete words, then wait. Slowly counting to ten in your head after a question gives your child time to process and respond.
Small changes, big difference
Sometimes "behavior problems" ease when the environment changes: softer lighting, less noise, comfortable textures, or a quiet corner.
Keep a binder
Keep evaluations, reports, IEPs, and notes on progress in one place. Stay in regular contact with teachers and take an active part in school meetings.
Find your community
Parent support groups, online or in person, adapted sports and arts programs, and disability advocacy organizations offer friendship, practical tips, and a stronger voice for all children.
Can it be prevented?
Most developmental disabilities can't be prevented, and they aren't anyone's fault. Some risks can be lowered: prenatal care, folic acid, avoiding alcohol and drugs in pregnancy, vaccines that prevent harmful infections, and good nutrition. Six keys to your baby's brain health
Do children outgrow it?
Most developmental disabilities are lifelong, though some differences, like certain speech delays or attention challenges, can ease with time and support. With the right help, children build real skills and lead full lives.
Explaining to others
Lead with who your child is, their interests and strengths, then share briefly what helps them. Your child is a child first.
Behavior at school: positive support, not punishment
Special education experts often put it this way: behavior is a form of communication. When a child with a disability struggles at school, the goal is to understand why and teach new skills, not to punish or remove them from class.
It's in the law
Under IDEA, if a child's behavior gets in the way of their learning or others', the IEP team must consider positive behavioral interventions and supports (PBIS) and include them in the IEP when the team decides they are needed.
Ask "why?" with an FBA
A functional behavioral assessment looks at what happens before and after a behavior to understand what it's communicating. It leads to a behavior intervention plan (BIP) that changes triggers and teaches new skills, and should be reviewed regularly.
Suspensions and removals
Sending children out of class or school is linked to worse outcomes and is used unevenly across groups of children. Federal special education law (IDEA and Section 504) gives children with disabilities specific protections when discipline is considered, and many experts advise using removal as a last resort and restraint or seclusion only in true safety emergencies. Rules differ by state and district, so ask your school for its written policy.
Learning designed for everyone
Universal Design for Learning offers many ways to take in information, engage, and show what a child knows, a strengths-based approach that helps all children, including those with disabilities.
You're part of the team
You can ask for an IEP meeting, request an FBA, bring notes about what works at home, and ask how the school's supports respect your child's culture and language. Free language help is available from the Department of Education at 1-800-USA-LEARN.
Learning your child is developing differently: reacting with love
Finding out that your child is developing differently, through neurodivergence, a physical disability, or a delay, can turn your world upside down. Confusion, fear, and grief are all normal. Reacting with love doesn't mean having every answer. It means building a safe, accepting place for your child and for yourself.
Care for yourself first
It's okay to grieve the future you imagined; that grief doesn't mean you love your child any less. Let go of searching for blame. Find your village: a therapist, parent groups, and organizations that understand.
Understand, don't just "fix"
Your child is the same wonderful person they were before the diagnosis. Learn all you can, including from adults who share the same diagnosis. Therapies like speech, occupational, or behavioral support can build skills, but the goal is a thriving child, not a "typical" one.
Presume competence
Speak to and about your child as someone who understands, feels, and can keep learning, even if they communicate differently.
Be a safe harbor
Children read our faces. Validate struggles ("This is really hard, and I'm right here"). Celebrate your child's own milestones. Frame headphones, wheelchairs, communication devices, and therapies as tools that open up their world.
About milestones: use developmental checklists to spot when your child could use support, not to compare them with other children. Their timeline is their own.
Tap a card to reframe a stressful thought.
The joys parents describe, too
Much of what's written about raising a child with an intellectual disability focuses on stress. But when researchers reviewed 22 studies of what parents themselves say, they found consistent positives across countries and decades. Parents described:
Joy and pride in their child
A deep, unique bond, delight in time together, and pride in achievements no one expected.
Personal strength
More confidence, determination, and belief in their own ability to meet challenges.
Growing as a person
More patience, kindness, and hope, and new skills, including speaking up for their child and others.
A new outlook
Clearer priorities, gratitude for small things, and more empathy and acceptance toward others.
Closer relationships
Stronger family bonds and new friendships with people who understand.
Faith and meaning
For some, deeper spirituality or a stronger sense of purpose and meaning.
Caring for the caregiver
Grief can come back
Adjusting isn't a straight line. A new diagnosis, a missed milestone, or a hard school meeting can bring old feelings back. That's normal, not a step backward.
Self-compassion, not just self-care
A spa day is nice, but what lasts is a kind inner voice: "I'm doing a giant job, and I'm doing it with love." Research links self-compassion to lower stress and depression in parents of autistic children.
Try 10% for you
Imagine giving back just 10% of the energy you pour into your child each day: a walk, a swim, a meditation app, coffee with a friend. It isn't selfish; it's part of family care.
Calm is contagious
Young children borrow calm from the adults around them. Caring for your own stress doesn't mean you caused your child's struggles; it means you're giving them a steadier place to land.
Invite small joys
Notice and savor good moments, like gratitude, laughter, or kindness. Positive emotions help build the resilience you'll draw on during hard days.
A peaceful warrior
Advocating can feel like a constant fight, and no one can fight forever. Pace yourself, share the load with your partner and village, and refill your tank on purpose.
Protective factors that help across the board
At least one steady, caring adult
Consistently linked to resilience, even when a child faces real adversity.
Treated parental mental health
Getting help for yourself is one of the most direct ways to protect your child.
Sleep, movement, and routine
Predictable days and enough sleep support emotional regulation at every age.
Naming feelings
Children who learn words for emotions get better at managing them.
Finance
Money stress is nervous system stress. A plan you make together before the baby arrives takes a lot of pressure off the months after.
Conversations to have early
Leave
Find out what your workplace offers and what your state provides. Federal FMLA offers eligible employees unpaid, job-protected leave, and some states, including Washington, run paid family leave programs.
Insurance
Learn your deductible, out-of-pocket maximum, and how to add the baby. In the US, a birth usually opens a special enrollment window, so check your plan's deadline.
Childcare
Waitlists can be long. Look early, and talk about who will cover care if someone gets sick.
A cushion
Even a small emergency fund lowers stress. Many planners suggest aiming over time for enough to cover out-of-pocket birth costs plus a few months of living expenses. Decide together what counts as an emergency.
Costs across the journey
The first year, month by month
Costs rise and fall as your baby grows. Tap a stage to see what tends to come up.
Studies of the cost of raising a child vary widely. One 2026 LendingTree analysis put the average at about $17,000 a year, or more than $303,000 to age 18, with child care a major expense in the early years. Your costs may be far lower or higher.
What a baby can cost
Numbers can feel overwhelming. They're here to help you plan, not to scare you. Costs vary a lot by where you live, your insurance, and your choices.
The birth
Costs depend on your insurance, your state, and whether you have a vaginal or cesarean birth. With insurance, most of the bill is covered; check your deductible and out-of-pocket maximum early. Twins and complications cost more.
Medicaid
Medicaid pays for about 4 in 10 US births, and most states now cover parents for a full year after birth. Income limits are higher during pregnancy than for other adults, so check even if you didn't qualify before.
Gear
Hand-me-downs and used items save a lot. Two exceptions: buy car seats new or from someone you trust (they expire and may be damaged in crashes), and make sure cribs meet current safety standards.
A typical year in the first two years
About $12,680 a year for a middle-income two-parent family, based on the USDA's last report (2015 dollars). Costs are higher today with inflation. Child care is often the biggest expense after housing, so sibling discounts, family help, and flexible work can make a real difference.
Benefits, insurance, and savings for a new baby
After-birth money checklist
Tax credits
Child Tax Credit
Up to $2,200 per child under 17, with up to $1,700 refundable even if you owe little or no tax. The full credit is available up to $200,000 in income ($400,000 for married couples filing jointly). To get the refundable part, you need at least $2,500 in earned income. You (or your spouse, if filing jointly) and your child each need a Social Security number valid for work, issued by your tax return's due date, so apply for your baby's number soon after birth. Claimed on Schedule 8812 with Form 1040; you may be able to claim it even if you don't usually file. IRS details
Pre-tax and penalty-free options
A Dependent Care FSA through your employer lets you pay for child care with pre-tax dollars, and a Healthcare FSA covers copays and prescriptions. Within a year of a birth or adoption, each parent can take up to $5,000 from a retirement account without the 10% early-withdrawal penalty, though income tax still applies, so weigh it carefully.
Other credits to know
The Credit for Other Dependents (up to $500), which can be claimed for dependents with an ITIN when the Child Tax Credit doesn't apply, the Child and Dependent Care Credit for daycare costs, the Earned Income Tax Credit for lower and moderate incomes, and the Adoption Tax Credit for adoptive families. Free tax help is available for qualifying families.
Health insurance for your baby
Coverage isn't automatic
Many plans cover a newborn only for the first 30 days. A birth is a qualifying life event, so you can add your baby outside open enrollment, but deadlines are short: usually 30 days for employer plans and 60 days for Marketplace plans. Don't wait for your baby's Social Security card; the clock starts at birth, and you can usually add the number later. It's also a chance to rethink your whole plan, since babies have many checkups in the first year.
Medicaid and CHIP
Babies born to parents covered by Medicaid are generally covered for their first year. The Children's Health Insurance Program (CHIP) offers low-cost coverage, including checkups and vaccines, with year-round sign-up.
Savings accounts for a child
| Account | Key features | Things to know |
|---|---|---|
| Trump Account | A federal $1,000 starter deposit for eligible US-citizen children born 2025 through 2028. Family and others can add up to $5,000 a year, invested in US stock index funds. | Opened by filing IRS Form 4547 (with your tax return or online). Follows retirement-account rules once the child turns 18. |
| 529 education plan | Earnings grow tax-free when used for qualified education, including college, trade school, and some K–12 tuition. Many states offer a state tax deduction. | Plans are run by states; compare fees and your own state's benefits. Unused money can usually go to another family member, and some can later roll into the child's Roth IRA within limits. Some states also offer prepaid tuition plans. |
| Coverdell education savings account | Tax-free growth for education from kindergarten through college, including tuition, books, and tutoring. | Contributions are capped at $2,000 a year per child, and income limits apply. |
| Custodial account (UGMA/UTMA) | No contribution limits and can be used for any purpose that benefits the child. | Fewer tax advantages, the money legally belongs to the child, and the child gains full control at 18 to 21, depending on the state. It can also count more heavily against college financial aid. |
| Children's savings account | A simple bank account managed by a parent or guardian. | Look for no minimum balance, no fees, and a good interest rate. |
Many families combine accounts. A financial or tax professional can help you decide what fits your goals.
Protecting your family
It's not easy to think about, but a few documents give real peace of mind.
A will and a guardian
A will is where you name who would raise your child if something happened to you. For many parents, this is the single most important step after a birth.
Beneficiaries and powers of attorney
Update beneficiaries on life insurance and retirement accounts, and name who can make financial and medical decisions if you can't. A trust can add control, especially for larger estates.
Insurance that protects income
Check whether your life insurance would replace lost income, child care, and debts, and consider disability insurance, since your ability to earn is often your biggest asset.
Your rights at work (US)
Protection from discrimination
You can't be fired, passed over, given lesser assignments, or forced onto leave because of pregnancy, childbirth, or a related medical condition.
Reasonable accommodations
Under the Pregnant Workers Fairness Act, if your employer has 15 or more employees, you can ask for changes like extra breaks, a water bottle or snacks, a stool, schedule changes or telework, help with lifting, or time off for appointments and recovery. Learn more
The right to pump
Under the PUMP Act, most employees have the right to reasonable break time and a private place, other than a bathroom, to pump milk at work for up to a year after birth. Learn more
More help for families
Housing and energy
HUD housing counseling and LIHEAP for help with energy bills.
Child care
Help paying for child care, plus tips for visiting and choosing a program.
Children's coverage
InsureKidsNow.gov or 1-877-KIDS-NOW for Medicaid and CHIP. If you're enrolled, keep your contact information current and watch for renewal letters.
Cash assistance
Temporary Assistance for Needy Families (TANF) offers time-limited cash help for eligible low-income families through your state. Some states have their own programs too. Some cities and tribal communities also run guaranteed-income pilots for new parents; ask locally.
Example: Washington State
The Pregnant Women Assistance program offers up to $450 a month in cash to eligible low-income pregnant people who don't qualify for TANF. Apply through DSHS online, by phone at 877-501-2233, or at a local office. Applications come in many languages.
Where to start
Most programs run through your state's health and human services department. In the US, dialing 211 connects you with local help for food, housing, utilities, and more.
Outside the US
Every country has its own supports. Your local health ministry, midwife, community health center, or social services office can tell you what's available where you live.
Source: US Department of Health and Human Services and Washington State DSHS. Programs, amounts, and eligibility vary by state and country, and change over time, so check current details.
Essentials, not extras
Babies need less than stores suggest. Check off what you have; your list stays in this browser. Borrowed and secondhand items are great, except car seats and sleep spaces, which should meet current safety standards.
Safe sleep basics
Every sleep: alone, on the back, on a firm flat mattress with only a fitted sheet. No pillows, blankets, bumpers, or weighted sleep sacks. Room-sharing without bed-sharing is recommended for at least the first 6 months.
Bouncers and swings
Handy for awake, supervised time while you're nearby. If your baby falls asleep in one, move them to their flat sleep space.
Fever in a newborn is urgent
For a baby under 3 months, a temperature of 100.4°F (38°C) or higher is a reason to call your pediatrician right away, day or night. A rectal thermometer gives the most accurate reading.
Shop smart
Research big items like the car seat and stroller for your needs and budget. Keep clothes simple. Buy one or two bottles and pacifiers to test before buying a set. Toys and gadgets can wait; every baby is different.
Clean bottles
Wash bottles after every use with hot soapy water and a bottle brush. The CDC also recommends sanitizing at least once a day for babies under 3 months, born early, or with weaker immune systems, for example by boiling for 5 minutes.
Changing and bath safety
Keep one hand on your baby when they're on any raised surface, or change them on a mat on the floor. Test bath water with your wrist or elbow, and never leave a baby alone in water, even for a moment.
Umbilical cord care
Today's advice is simple: keep the stump clean and dry, fold the diaper below it, and let it fall off on its own, usually in 1 to 3 weeks. Rubbing alcohol is no longer recommended. Call your pediatrician if you see redness spreading, pus, or a bad smell.
You can probably skip
Changing tables, wipe warmers, bottle warmers, baby shoes, diaper pails, and too many outfits. A regular sink or tub works for baths, and any backpack can be a diaper bag. Ask what your hospital sends home, and pass things along when your baby outgrows them.
Car seat check
Rear-facing, installed correctly, and never secondhand from a stranger. Many fire stations and hospitals offer free installation checks by certified technicians.
Monthly baby budget sketch
Enter your own estimates. Nothing is sent anywhere; numbers stay in this browser.
Estimated monthly total
$0
About $0 a year
This is a planning aid, not financial advice. A financial professional can help with your specific situation.
Agreements
Most conflict after a baby isn't about big values. It's about the 3 a.m. feeding nobody discussed. Talk through these now, while you're both rested.
How to start the conversation
Pick the moment
Choose a calm, private time, not during an argument, a stressful day, or when one of you is exhausted. A walk or a quiet evening works well.
Open gently
Share your own feelings first, then ask open questions and listen. You're exploring together, not winning a debate.
Take it in pieces
No one settles everything in one talk. Pick a few topics at a time, write down what you agree on and any deal-breakers, and come back to the rest.
Tap a card for a way to open the topic.
100 questions to explore together
Your agreements
Your notes stay only in this browser on this device.
Your care team
You deserve to be listened to, spoken to with respect, and included in every decision about your body and your baby. Good communication isn't a bonus. Research links it with better experiences, less stress, and better follow-through on care.

What respectful care looks like
A review of research on communication in maternity care points to a few things that make the biggest difference.
Active listening
Your provider gives you full attention, acknowledges your feelings, and asks what matters to you.
Clear, honest information
Options, risks, and benefits are explained in plain words, and you get time to ask questions.
Respect for your culture
Your beliefs, traditions, language, and privacy preferences are taken seriously, not stereotyped.
Shared decisions
Your provider brings medical knowledge, you bring your values, and you decide together.
When communication breaks down
A study in which women in Malawi described their experiences during childbirth found that when providers were warm and respectful, women wanted to come back. When they were shouted at, mocked, ignored when they asked questions, couldn't understand their provider's language, or were treated worse for being poor or unable to read, some said they would rather give birth outside the health system next time. Research from many countries, including the US, describes similar barriers.
Language
You have the right to understand your care. In the US, health care providers that receive federal funding must offer language help, such as a qualified interpreter, usually at no cost. Ask for one, including for sign language.
Questions
If you're rushed, it's okay to say "I have two more questions before we finish." Writing them down beforehand helps.
Disrespect
If you're treated rudely or unfairly, you can ask for a different provider, bring a support person, or contact the facility's patient advocate.
Urgent maternal warning signs
If something just doesn't feel right, trust that and talk to a provider. Partners, family, and friends: if she says something is wrong, listen and help her get care. List from the CDC's Hear Her campaign, developed by the Alliance for Innovation on Maternal Health.
Free and low-cost help
Money and access shape every pregnancy. These federal programs can help.
Community health centers
Nearly 1,400 federally funded health centers offer prenatal, primary, and mental health care regardless of your ability to pay. Find a health center
WIC
Free healthy foods, nutrition counseling, and breastfeeding support for eligible pregnant and postpartum people and children under 5. Learn about WIC
Early Head Start
Free programs for eligible pregnant people, babies, and toddlers that support early learning, health, and family well-being. Learn more
Safe sleep
Babies sleep safest alone, on their backs, on a firm flat surface with no soft bedding. CDC safe sleep tips
If you feel you can't keep your baby safe
Every US state has Safe Haven laws that let a parent leave a newborn safely and confidentially at designated places like hospitals and fire stations. Reaching out for help is an act of care.
More federal resources
Moms.gov gathers federal information on pregnancy, breastfeeding, nutrition, mental health, and family support in one place.
OB-GYN, midwife, doula: who does what?
You don't have to choose between them. A doctor or midwife provides your medical care and delivers your baby; a doula can add non-medical support alongside either one. In the US, most births are attended by a physician and about 1 in 10 by a midwife, while in many countries and cultures midwives are the main caregivers through pregnancy and birth.
| Role | What they do | Often a good fit if |
|---|---|---|
| OB-GYN | A medical doctor with four years of medical school and a four-year residency, often board-certified, specializing in pregnancy and reproductive health. Manages complications, performs procedures, and does cesarean births. Maternal-fetal medicine specialists handle the highest-risk pregnancies. Some family physicians also provide pregnancy care and deliver babies, though not all do, and not all perform cesareans. | You have a health condition or higher-risk pregnancy, or you want a doctor-led hospital birth. |
| Midwife | A trained health professional who cares for healthy pregnancies, monitors labor, and delivers babies, and consults or transfers care to a doctor if complications arise. In the US there are three main credentials: certified nurse-midwives (registered nurses with a graduate degree), certified midwives (non-nurses with a graduate degree in midwifery), and certified professional midwives (certified by the North American Registry of Midwives, who mostly attend home and birth center births). Nurse-midwives usually work in hospitals, provide routine gynecological care, and can prescribe. Training and licensing vary by state and country. | Your pregnancy is low-risk and you'd like a lower-intervention approach, in a hospital, birth center, or at home. |
| Doula | A trained, non-medical support person who stays with you through labor: comfort measures, breathing, massage, information, and help speaking up for your wishes. Doulas don't deliver babies or give medical advice. Many offer mental health check-ins, and postpartum doulas help at home after birth. | You'd like continuous, one-on-one emotional and physical support, whatever kind of birth you have, including with an epidural or cesarean. |
| Your hospital team | Nurses, plus your doctor or midwife, care for you safely through labor, though nurses often care for more than one patient at a time. | You plan to rely on your partner, family, and care team for support. |
Questions to help you choose
Finding and hiring a doula
Birth or postpartum doula?
A birth doula supports you continuously through labor and delivery. A postpartum doula helps in the weeks and months after, with newborn care, feeding, rest, and adjusting to your new roles. Some families choose one, some both.
Where to look
DONA International's directory lists certified doulas worldwide. Your provider, hospital, local parent groups, and community doula programs can also recommend people, including free or sliding-scale options.
A good doula supports your choices
DONA's code of ethics says doulas support each family's decisions without judgment and don't make choices for you or push their own preferences, whether you want an epidural, an unmedicated birth, or a cesarean.
Questions to ask in an interview
- What training or certification do you have, and how many births have you supported?
- How many visits are included before and after the birth, and what does it cost? Do you offer sliding-scale fees, or take insurance or Medicaid?
- When do you join me in labor, and who is your backup if you can't come?
- How do you support my partner and work with my medical team?
- How would you support me if my plans change, like needing an induction or a cesarean?
- Have you supported families from my culture, faith, or language, or with my family's needs?
- Can I talk with families you've worked with?
Trust how you feel with them. Feeling safe and understood matters as much as experience.
Why doulas matter for mental health
Continuous labor support is linked to less use of pain medication, fewer interventions, shorter labors, and more positive birth experiences, and feeling supported and heard during birth matters for how parents feel afterward.
Paying for a doula
Some state Medicaid programs and insurers now cover doula care, and many communities have sliding-scale, volunteer, or nonprofit doulas, including programs for Black, Hispanic, and Indigenous families, who face higher risks in pregnancy. Ask your provider, hospital, or local doula organization.
Who may benefit most from a doula
Doulas can be especially helpful for first-time parents, people who had a hard or traumatic birth before, and people hoping for an unmedicated birth. In a national survey of births in 2011-12, only about 6% included a doula, often because families don't know about them or can't afford one.
Finding your team
Start with your insurance plan's list and ask people you trust. Directories can help: the American College of Nurse-Midwives and the North American Registry of Midwives for midwives, and DONA International for doulas. Midwives often care for your whole self, physical, emotional, and social, which fits a biopsychosocial approach.
Check credentials
Look for a certified nurse-midwife or licensed midwife and a trained or certified doula. Many hospitals and birth centers don't allow uncredentialed providers in the birth room.
Take a childbirth class
Whoever is on your team, a childbirth education class helps you and your support people know what to expect. Many hospitals offer them free or at low cost, online or in person.
Every choice is valid
A hospital or home birth, a midwife or a doctor, medication or none, a planned or unplanned cesarean: there's no "better" way to give birth. What matters is that you're safe, respected, and supported.
Finding a perinatal mental health specialist
Postpartum Support International (PSI), the largest nonprofit focused on perinatal mental health, created the first certification in this specialty in 2018. Providers who hold it use the letters PMH-C after their name.
What PMH-C means
The provider has at least two years of experience working with pregnant and postpartum families, completed specialized perinatal mental health training plus advanced training, and passed a certification exam.
Who can hold it
Therapists and counselors, prescribers such as psychiatrists and nurse practitioners, and allied professionals like nurses, doulas, lactation consultants, and peer supporters.
Where to look
PSI's online provider directory and free HelpLine (1-800-944-4773) can connect you with trained providers and free online support groups.
What perinatal mental health care can include
Before pregnancy
Preconception counseling to plan for your mental health, including medicines, before you conceive.
Medication guidance
Specialists who understand medicines during pregnancy, breastfeeding, and postpartum, and who weigh the risks of treatment against the risks of untreated illness with you.
Therapy
Evidence-based talk therapy before, during, and after pregnancy, including support after loss and bereavement.
Groups and partners
Support groups for parents adjusting to life with a baby, and care for partners whose mood is affected too.
This kind of care may be for you if…
If any of these fit, that's reason enough to reach out. You don't need to be in crisis to deserve support. This is a reflection tool, not a diagnosis, and your answers aren't saved.
Example: Washington State
Perinatal Support Washington runs a free Warm Line (1-888-404-7763): leave a message and a trained volunteer calls back within a day. They also offer support groups, therapy, and referrals. Many local hospitals, such as EvergreenHealth, have perinatal behavioral health programs too.
Wherever you live
Ask your obstetric provider, midwife, or pediatrician for a referral, or contact PSI, which has volunteer coordinators in many countries. Outpatient programs aren't for emergencies; in a crisis in the US, call or text 988.
A simple way to make decisions: BRAIN
Many childbirth educators teach these five questions. Tap each one.
Plan your next visit
Jot down what you want to ask. Your notes stay only in this browser.
If you're asked to join a research study
Research during pregnancy is how we learn what's safe and what helps, and taking part is always your choice. In the US, federal rules add extra protections for studies involving pregnant people. Here's how consent works under those rules:
Your consent alone
When a study might benefit you, or you and the baby, or when it carries no more than minimal risk to the fetus and seeks important knowledge that can't be gained another way.
Both parents' consent
When the possible benefit is to the fetus alone, the other biological parent (the regulation says "father") must usually consent too. That isn't required if they can't reasonably be found or reached, can't consent, or if the pregnancy resulted from rape or incest.
Your rights
You can ask questions, take time to decide, say no, or leave a study at any time without it affecting your regular care.
About us
Within Your Pregnancy is an educational project of WITHIN Learning Group, LLC. We look at pregnancy before, within, and after through a biopsychosocial lens, as a mental health journey for parents and the developing child. We translate research on brain development and perinatal mental health into plain language for the people living it.

Within Learning Group

WithinYourPregnancy.com is part of Within Learning Group, an educational initiative dedicated to making science-informed, compassionate knowledge accessible to individuals, couples, and families seeking growth, healing, and deeper connection.
Illuminating Minds and Hearts Through Learning From Within
Evidence-based biopsychosocial education for emotional wellness, families, and creative growth.
Copyright © 2026 Within Learning Group LLC.
What we believe
A baby's mental health starts with the mental health of the people caring for them. Supporting parents is supporting babies.
For every family
This site is for everyone: every culture, religion, tradition, language, family shape, and financial situation. We care about all the babies in the world, and we believe a healthy, well-informed pregnancy is the first way to care for a baby.
Gentle by design
We share peer-reviewed research with care. Our goal is to educate, never to frighten or shame. Every fact comes with what you can do, and with compassion for real life.
Evidence first, human always
Our foundation is the biopsychosocial lens, and our content draws on peer-reviewed research and trusted health organizations (see our sources). Where philosophy, culture, spirituality, or personal reflection can enrich a topic, we say so clearly and keep it separate from the research. How we label what we share.
Guided by professional ethics
As a mental health education project, we are guided by the ACA, AMHCA, and APA codes of ethics. No ads, no sponsors, no analytics or tracking cookies. Our ethics
Our sister sites
Contact us
Questions, ideas for topics, or partnership requests are welcome. We can't give individual medical or mental health advice.
Bienvenida en español
Within Your Pregnancy ofrece educación sobre la salud mental antes, durante y después del embarazo: el cuerpo, la mente y el mundo que te rodea. Esta página reúne en español la información más importante para tu seguridad.
Apoyo ahora
Estas líneas gratuitas en EE. UU. son para madres, padres, parejas y cualquier persona que los apoye, durante el embarazo y después.
Señales de alerta urgentes
Dolor de cabeza que no se quita o empeora
El peor dolor de cabeza de tu vida, que no mejora con medicina ni líquidos, que empieza de repente, o que viene con visión borrosa o mareo.
Mareos o desmayos
Te desmayas, te sientes mareada por días o tienes un momento que no puedes recordar.
Cambios en la vista
Destellos de luz, puntos brillantes, puntos ciegos, visión borrosa o doble.
Fiebre de 100.4 °F (38 °C) o más
Tómate la temperatura si te sientes mal.
Hinchazón extrema de las manos o la cara
Te cuesta doblar los dedos o usar anillos, los ojos están tan hinchados que no abren bien, o los labios están hinchados o adormecidos.
Pensamientos de hacerte daño o de hacerle daño a tu bebé
Sentirte muy triste, sin esperanza, fuera de control o extremadamente preocupada, o tener pensamientos no deseados de lastimar a tu bebé.
Dificultad para respirar
Falta de aire repentina o que aumenta, garganta o pecho apretados, o necesitar almohadas para respirar acostada.
Dolor en el pecho o corazón acelerado
Presión en el pecho, dolor que se extiende a la espalda, el cuello o el brazo, o latidos rápidos o irregulares.
Náuseas y vómitos fuertes
Mucho más que las náuseas normales: no puedes beber por 8 horas, comer por 24 horas, o mantener líquidos.
Dolor fuerte de vientre que no se quita
Dolor agudo, punzante o de cólico que empieza de repente o sigue empeorando.
El bebé se mueve menos o deja de moverse durante el embarazo
No hay un número "normal" de patadas. Lo importante es un cambio en lo que es usual para tu bebé.
Sangrado o salida de líquido vaginal durante el embarazo
Sangrado más fuerte que unas gotas, cualquier salida de líquido o flujo con mal olor.
Sangrado fuerte o flujo después del parto
Empapar una o más toallas sanitarias en una hora, coágulos más grandes que un huevo o flujo con mal olor.
Hinchazón, enrojecimiento o dolor en una pierna o un brazo
Por lo general en una pantorrilla o un brazo, a veces caliente o rojo. Vigila esto durante el embarazo y hasta 6 semanas después del parto.
Cansancio abrumador
Debilidad repentina, ningún descanso te recupera, estás demasiado cansada para cuidar a tu bebé, o te sientes triste después del parto.
Si algo no se siente bien, confía en ti y habla con un proveedor. Parejas y familiares: si ella dice que algo está mal, escúchenla y ayúdenla a recibir atención. Lista basada en la campaña Hear Her (Escúchala) de los CDC.
Sobre este sitio
Este sitio es solo educativo. Usarlo no crea una relación de consejería, terapia ni atención médica, y no reemplaza la atención de un profesional calificado.
Seguimos los códigos de ética de la ACA, la AMHCA y la APA. No mostramos anuncios, no tenemos patrocinadores y no rastreamos a nadie. Lo que guardas en este sitio se queda en tu propio dispositivo.
Escribimos para todas las familias: toda cultura, fe, idioma, forma de familia y situación económica.
Explora el resto del sitio
Todo el sitio ya está disponible en español. Usa el menú de idioma que aparece en la parte de arriba de cualquier página para cambiar entre inglés y español. Las traducciones todavía no las ha revisado un traductor médico certificado, así que confirma la información de salud importante con tu proveedor. En EE. UU., la mayoría de los hospitales y clínicas que reciben fondos federales (por ejemplo, Medicare o Medicaid) deben ofrecerte un intérprete calificado sin costo en tus citas médicas. Pídelo.
Bienvenue en français
Within Your Pregnancy propose une information éducative sur la santé mentale avant, pendant et après la grossesse : le corps, l'esprit et le monde qui vous entoure. Cette page réunit en français les informations les plus importantes pour votre sécurité.
Obtenir du soutien maintenant
Ces lignes gratuites aux États-Unis s'adressent aux mères, aux pères, aux partenaires et à toute personne qui les soutient, pendant la grossesse et après.
Signes d'alerte urgents
Mal de tête qui ne passe pas ou s'aggrave
Le pire mal de tête de votre vie, qui persiste malgré les médicaments et les boissons, qui commence brutalement, ou qui s'accompagne d'une vision floue ou de vertiges.
Vertiges ou évanouissement
Vous perdez connaissance, vous avez des vertiges pendant plusieurs jours, ou vous ne vous souvenez pas d'un moment.
Troubles de la vue
Éclairs lumineux, taches brillantes, zones aveugles, vision floue ou double.
Fièvre de 38 °C (100,4 °F) ou plus
Prenez votre température si vous ne vous sentez pas bien.
Gonflement important des mains ou du visage
Difficulté à plier les doigts ou à porter des bagues, yeux si gonflés qu'ils s'ouvrent mal, lèvres gonflées ou engourdies.
Pensées de vous faire du mal ou de faire du mal à votre bébé
Vous sentir très triste, sans espoir, hors de contrôle ou extrêmement inquiète, ou avoir des pensées non désirées de blesser votre bébé.
Difficulté à respirer
Essoufflement soudain ou qui s'aggrave, gorge ou poitrine serrée, ou besoin d'être surélevée pour respirer en position allongée.
Douleur à la poitrine ou cœur qui bat vite
Pression dans la poitrine, douleur qui s'étend au dos, au cou ou au bras, ou battements rapides ou irréguliers.
Nausées et vomissements sévères
Bien plus que les nausées habituelles : impossible de boire pendant 8 heures, de manger pendant 24 heures, ou de garder les liquides.
Douleur au ventre intense qui ne passe pas
Douleur aiguë, lancinante ou en crampes, qui commence brutalement ou s'aggrave.
Le bébé bouge moins ou ne bouge plus pendant la grossesse
Il n'y a pas de nombre « normal » de mouvements. Ce qui compte, c'est un changement par rapport à l'habitude de votre bébé.
Saignement ou perte de liquide vaginal pendant la grossesse
Saignement plus abondant que quelques gouttes, toute perte de liquide, ou pertes à mauvaise odeur.
Saignement abondant ou pertes après l'accouchement
Une serviette hygiénique ou plus trempée en une heure, caillots plus gros qu'un œuf ou expulsion de tissus, ou pertes à mauvaise odeur.
Gonflement, rougeur ou douleur dans une jambe ou un bras
Généralement dans un mollet ou un bras, parfois chaud ou rouge. À surveiller pendant la grossesse et jusqu'à 6 semaines après l'accouchement.
Fatigue écrasante
Faiblesse soudaine, aucun repos ne suffit, trop fatiguée pour vous occuper de votre bébé, ou tristesse après l'accouchement.
Si quelque chose ne vous semble pas normal, faites-vous confiance et parlez-en à un professionnel. Partenaires et proches : si elle dit que quelque chose ne va pas, écoutez-la et aidez-la à obtenir des soins. Liste basée sur la campagne Hear Her des CDC.
À propos de ce site
Ce site est uniquement éducatif. Son utilisation ne crée pas de relation d'accompagnement psychologique, de thérapie ou de soins médicaux, et ne remplace pas les soins d'un professionnel qualifié.
Nous suivons les codes de déontologie de l'ACA, de l'AMHCA et de l'APA. Pas de publicité, pas de sponsors, aucun traçage de votre navigation. Ce que vous enregistrez sur ce site reste sur votre propre appareil.
Nous écrivons pour toutes les familles : toutes les cultures, croyances, langues, formes de famille et situations financières.
Explorer le reste du site
Tout le site est maintenant disponible en français. Utilisez le menu des langues en haut de chaque page pour passer de l'anglais au français. Les traductions n'ont pas encore été révisées par un traducteur médical certifié : vérifiez donc les informations de santé importantes auprès de votre professionnel de santé. Dans la plupart des hôpitaux et cliniques des États-Unis qui reçoivent des fonds fédéraux (comme Medicare ou Medicaid), vous pouvez obtenir gratuitement un interprète qualifié pour vos rendez-vous médicaux : n'hésitez pas à le demander.
欢迎(简体中文)
Within Your Pregnancy 提供关于怀孕前、怀孕期间和产后心理健康的教育信息,关注身体、心理以及您周围的世界。本页用中文汇集了与您的安全最相关的重要信息。
立即获得支持
以下是美国的免费热线,适用于怀孕期间及产后的母亲、父亲、伴侣以及任何支持他们的人。
紧急警示症状
头痛不消退或越来越严重
一生中最严重的头痛,服药和喝水后仍不缓解,突然开始,或伴有视力模糊或头晕。
头晕或昏倒
您昏倒过、连续几天时常头晕,或有一段时间想不起来发生了什么。
视力变化
看到闪光、亮点、盲点,短时间内完全看不见,或视力模糊、无法对焦、重影。
发烧 38°C(100.4°F)或以上
如果感觉不舒服,请测量体温。
手部或面部严重肿胀
手指难以弯曲或戴不上戒指,眼睛肿得睁不开,或嘴唇肿胀、麻木。
有伤害自己或婴儿的想法
感到非常悲伤、绝望、失控或极度担忧,或出现不想要的、伤害婴儿的念头。
呼吸困难
突然或逐渐感到气短,喉咙或胸口发紧,或躺下时需要垫高才能呼吸。
胸痛或心跳很快
胸口有压迫感,疼痛蔓延到背部、颈部或手臂,或心跳过快、怦怦直跳或不规律。
严重恶心和呕吐
远比一般孕吐严重:超过8小时无法喝水、超过24小时无法进食,或喝下的液体都吐出来。
严重腹痛且不消退
突然开始或持续加重的剧痛、刺痛或绞痛;或严重的胸部、肩部或背部疼痛。
怀孕期间胎动减少或停止
胎动没有一个“正常”的固定次数。重要的是与您宝宝平常的情况相比是否有变化。
怀孕期间阴道出血或流液
出血量多于少量点滴,任何液体流出,或分泌物有异味。
产后大量出血或分泌物
一小时内浸透一片或更多卫生巾,排出比鸡蛋大的血块或组织,或分泌物有异味。
腿部或手臂肿胀、发红或疼痛
通常出现在一侧小腿或一只手臂,可能发热或发红。怀孕期间及产后6周内都要留意。
极度疲惫
突然非常虚弱,怎么休息都恢复不了,累得无法照顾宝宝,或产后感到悲伤。
如果感觉有什么不对劲,请相信自己并告诉医护人员。伴侣和家人:如果她说有什么不对,请认真倾听并帮助她就医。此列表依据美国疾病控制与预防中心(CDC)的 Hear Her 宣传活动。
关于本网站
本网站仅供教育用途。使用本网站不会建立咨询、治疗或医疗关系,也不能取代合格专业人员的照护。
我们遵循美国心理咨询协会(ACA)、美国心理健康咨询师协会(AMHCA)和美国心理学会(APA)的伦理守则。没有广告、没有赞助商、不做追踪。您在本网站保存的内容只会留在您自己的设备上。
我们为所有家庭撰写内容:不论文化、信仰、语言、家庭形式或经济状况。
探索网站的其他内容
整个网站现在已提供简体中文版本。您可以使用任何页面顶部的语言菜单,在英文和中文之间切换。这些翻译尚未经过认证的医学翻译人员审核,所以重要的健康信息请向您的医疗服务提供者确认。在美国,大多数医院和诊所(凡接受联邦资金者,例如 Medicare 或 Medicaid)必须在您就医时免费提供合格的口译员:请主动提出要求。
Chào mừng bằng tiếng Việt
Within Your Pregnancy cung cấp thông tin giáo dục về sức khỏe tâm thần trước, trong và sau khi mang thai: cơ thể, tâm trí và thế giới xung quanh bạn. Trang này tập hợp bằng tiếng Việt những thông tin quan trọng nhất cho sự an toàn của bạn.
Nhận hỗ trợ ngay
Các đường dây miễn phí tại Hoa Kỳ này dành cho mẹ, cha, người bạn đời và bất kỳ ai hỗ trợ họ, trong thai kỳ và sau sinh.
Dấu hiệu cảnh báo khẩn cấp
Đau đầu không hết hoặc nặng hơn
Cơn đau đầu tệ nhất trong đời, không đỡ dù đã uống thuốc và nước, bắt đầu đột ngột, hoặc kèm theo nhìn mờ hay chóng mặt.
Chóng mặt hoặc ngất xỉu
Bạn bị ngất, thường xuyên chóng mặt trong nhiều ngày, hoặc có khoảng thời gian không nhớ được.
Thay đổi thị lực
Thấy chớp sáng, đốm sáng, điểm mù, nhìn mờ hoặc nhìn đôi.
Sốt 38°C (100,4°F) trở lên
Hãy đo nhiệt độ nếu bạn cảm thấy không khỏe.
Sưng nhiều ở tay hoặc mặt
Khó gập ngón tay hoặc đeo nhẫn, mắt sưng đến mức khó mở, hoặc môi sưng hay tê.
Có ý nghĩ làm hại bản thân hoặc em bé
Cảm thấy rất buồn, tuyệt vọng, mất kiểm soát hoặc vô cùng lo lắng, hoặc có những ý nghĩ không mong muốn về việc làm đau em bé.
Khó thở
Hụt hơi đột ngột hoặc ngày càng nặng, cổ họng hay ngực bị thắt lại, hoặc phải kê cao người mới thở được khi nằm.
Đau ngực hoặc tim đập nhanh
Cảm giác đè nặng ở ngực, cơn đau lan ra lưng, cổ hoặc tay, hoặc tim đập nhanh, mạnh hay không đều.
Buồn nôn và nôn nhiều
Nặng hơn nhiều so với ốm nghén thông thường: không uống được trong hơn 8 giờ, không ăn được trong hơn 24 giờ, hoặc không giữ được nước uống.
Đau bụng dữ dội không hết
Cơn đau nhói, đau như dao đâm hoặc quặn thắt, bắt đầu đột ngột hoặc ngày càng tệ hơn.
Em bé cử động ít đi hoặc ngừng cử động trong thai kỳ
Không có số lần đạp nào là "bình thường" cố định. Điều quan trọng là sự thay đổi so với thói quen thường ngày của em bé.
Chảy máu hoặc rỉ nước âm đạo trong thai kỳ
Chảy máu nhiều hơn vài giọt, bất kỳ dịch nào rỉ ra, hoặc khí hư có mùi hôi.
Chảy máu nhiều hoặc sản dịch bất thường sau sinh
Thấm ướt một hoặc nhiều băng vệ sinh trong một giờ, cục máu đông lớn hơn quả trứng, hoặc sản dịch có mùi hôi.
Sưng, đỏ hoặc đau ở chân hoặc tay
Thường ở một bên bắp chân hoặc một cánh tay, có thể ấm hoặc đỏ. Hãy để ý trong thai kỳ và đến 6 tuần sau sinh.
Mệt mỏi quá mức
Đột nhiên rất yếu, nghỉ ngơi bao nhiêu cũng không lại sức, quá mệt để chăm sóc em bé, hoặc cảm thấy buồn sau sinh.
Nếu bạn cảm thấy có điều gì không ổn, hãy tin vào bản thân và nói với nhân viên y tế. Người bạn đời và gia đình: nếu cô ấy nói có điều gì không ổn, hãy lắng nghe và giúp cô ấy đi khám. Danh sách dựa trên chiến dịch Hear Her của CDC.
Về trang web này
Trang web này chỉ nhằm mục đích giáo dục. Việc sử dụng trang web không tạo ra mối quan hệ tư vấn, trị liệu hay chăm sóc y tế, và không thay thế sự chăm sóc của chuyên gia có trình độ.
Chúng tôi tuân theo các bộ quy tắc đạo đức của ACA, AMHCA và APA. Không quảng cáo, không nhà tài trợ, không theo dõi người dùng. Những gì bạn lưu trên trang web này chỉ ở trên thiết bị của chính bạn.
Chúng tôi viết cho mọi gia đình: mọi nền văn hóa, tín ngưỡng, ngôn ngữ, hình thức gia đình và hoàn cảnh tài chính.
Khám phá phần còn lại của trang web
Toàn bộ trang web hiện đã có bằng tiếng Việt. Hãy dùng menu ngôn ngữ ở đầu mỗi trang để chuyển giữa tiếng Anh và tiếng Việt. Các bản dịch chưa được biên dịch viên y khoa có chứng chỉ kiểm tra, vì vậy hãy xác nhận các thông tin sức khỏe quan trọng với nhân viên y tế của bạn. Tại Hoa Kỳ, hầu hết cơ sở y tế nhận tiền liên bang (như Medicaid, Medicare) phải cung cấp thông dịch viên miễn phí khi bạn yêu cầu. Hãy yêu cầu thông dịch viên khi đặt lịch hẹn.
Ti diamo il benvenuto in italiano
Within Your Pregnancy offre educazione alla salute mentale prima, durante e dopo la gravidanza: il corpo, la mente e il mondo che ti circonda. Questa pagina riunisce in italiano le informazioni più importanti per la tua sicurezza.
Supporto adesso
Queste linee gratuite degli Stati Uniti sono per genitori, partner e chiunque li sostenga, durante la gravidanza e dopo.
Segnali di allarme urgenti
Mal di testa che non passa o peggiora
Il peggior mal di testa della tua vita, che non migliora con i farmaci o i liquidi, che inizia all'improvviso o che arriva con vista offuscata o capogiro.
Capogiri o svenimenti
Svieni, ti senti stordita per giorni o hai un momento che non riesci a ricordare.
Cambiamenti della vista
Lampi di luce, puntini luminosi, punti ciechi, vista offuscata o doppia.
Febbre di 100,4 °F (38 °C) o più
Misurati la temperatura se non ti senti bene.
Gonfiore estremo di mani o viso
Fai fatica a piegare le dita o a portare gli anelli, gli occhi sono così gonfi che non si aprono bene, oppure le labbra sono gonfie o intorpidite.
Pensieri di farti del male o di fare del male al tuo bebè
Sentirti molto triste, senza speranza, fuori controllo o estremamente in ansia, oppure avere pensieri indesiderati di far male al tuo bebè.
Difficoltà a respirare
Mancanza di fiato improvvisa o che aumenta, gola o petto stretti, oppure aver bisogno di cuscini per respirare da sdraiata.
Dolore al petto o cuore che batte forte
Pressione al petto, dolore che si estende alla schiena, al collo o al braccio, oppure battito rapido o irregolare.
Nausea e vomito forti
Molto più della normale nausea: non riesci a bere per 8 ore, a mangiare per 24 ore o a trattenere i liquidi.
Forte dolore alla pancia che non passa
Dolore acuto, trafittivo o a crampi che inizia all'improvviso o continua a peggiorare.
Il bebè si muove meno o smette di muoversi durante la gravidanza
Non esiste un numero "normale" di calci. Ciò che conta è un cambiamento rispetto a quello che è abituale per il tuo bebè.
Sanguinamento o perdita di liquido dalla vagina durante la gravidanza
Sanguinamento più abbondante di qualche goccia, qualsiasi perdita di liquido o perdite con cattivo odore.
Sanguinamento abbondante o perdite dopo il parto
Inzuppare uno o più assorbenti in un'ora, coaguli più grandi di un uovo o perdite con cattivo odore.
Gonfiore, arrossamento o dolore a una gamba o a un braccio
In genere a un polpaccio o a un braccio, a volte caldo o rosso. Tieni d'occhio questo segnale durante la gravidanza e fino a 6 settimane dopo il parto.
Stanchezza travolgente
Debolezza improvvisa, nessun riposo ti ristora, sei troppo stanca per occuparti del tuo bebè, oppure ti senti triste dopo il parto.
Se qualcosa non ti sembra a posto, fidati di te e parlane con il tuo medico o la tua ostetrica. Partner e familiari: se la persona dice che qualcosa non va, ascoltatela e aiutatela a ricevere assistenza. Elenco basato sulla campagna Hear Her dei CDC.
Su questo sito
Questo sito ha solo scopo educativo. Usarlo non crea un rapporto di consulenza, terapia o assistenza medica e non sostituisce le cure di un professionista qualificato.
Seguiamo i codici etici di ACA, AMHCA e APA. Non mostriamo pubblicità, non abbiamo sponsor e non tracciamo nessuno. Ciò che salvi su questo sito resta sul tuo dispositivo.
Scriviamo per tutte le famiglie: ogni cultura, fede, lingua, forma di famiglia e situazione economica.
Esplora il resto del sito
Tutto il sito è ora disponibile in italiano. Usa il menu della lingua in alto in qualsiasi pagina per passare dall'inglese all'italiano. Le traduzioni non sono ancora state riviste da un traduttore medico certificato, quindi conferma le informazioni importanti sulla salute con il tuo medico o la tua ostetrica. Negli Stati Uniti, la maggior parte degli ospedali e delle cliniche che ricevono finanziamenti federali (come Medicare o Medicaid) è tenuta a offrirti gratuitamente un interprete qualificato durante le visite mediche. Chiedilo.
Your mental health
Caring for yourself is part of caring for your child. Here are calming tools you can use today, ways to break hard family patterns, and where to find real support.
Why your wellbeing matters
Calm is shared
Babies and young children borrow calm from the adults around them. When you have ways to settle your own body, you give your child a steadier place to land.
Treatment helps children too
In a large study, when mothers' depression improved with treatment, their children's symptoms improved too. A father's mental health matters for his child too. Getting help is one of the most loving things any parent can do.
Fathers too
About 1 in 10 fathers experience depression in pregnancy or the first year, and fathers' anxiety and stress are common too. In men it often shows up as irritability, anger, withdrawal, working longer hours, or drinking more, so it's easy to miss. Fathers deserve screening and care just as much.
Every parent struggles
Exhaustion, worry, irritability, and feeling overwhelmed are common for mothers, fathers, and partners. Struggling doesn't mean you're failing; it means you're human and need support.
How a parent's mental health shapes a baby's brain
This is hard to read, and important to know. It applies to both parents, and to any partner who cares for the baby. When a mother's or a father's depression, anxiety, anger, or unresolved childhood trauma is serious, lasts a long time, and goes untreated, research shows it can affect how a baby's brain develops, especially the systems for stress, emotions, attention, and relationships. It happens in two main ways:
During pregnancy
Long-lasting, intense distress changes stress hormones and inflammation. Much of this is filtered by the placenta, but chronic stress can weaken that protection, and it's been linked with differences in the baby's developing emotion and stress circuits.
After birth
Babies' brains grow through back-and-forth with caregivers: a smile answered, a cry soothed. Depression can make a parent flat or withdrawn, anxiety can make them tense, and anger or trauma can make them frightening or unpredictable. A baby's stress system then stays on alert, and over time this "toxic stress" can disrupt developing brain architecture.
The good news
The brain is most changeable early on, so these effects are not fixed. When parents get treatment and support, and when babies have at least one warm, steady caregiver, children's development improves.
Tap a topic to see what research shows, and what helps.
Breathing you can do anywhere
Slow breathing, especially with a longer breath out, helps calm your heart rate and nervous system. Choose a pattern and follow the circle for one to five minutes.
If you feel lightheaded, return to normal breathing. These tools ease stress; they don't replace treatment.
Your calming toolbox
5-4-3-2-1 grounding
When worry spins, notice 5 things you see, 4 you can touch, 3 you hear, 2 you smell, and 1 you taste. It brings your attention back to the present.
Name it to tame it
Say the feeling to yourself: "I'm anxious," "I'm overwhelmed." Putting feelings into words helps calm the brain's alarm system.
Relax your muscles
Tense one muscle group for 5 seconds, like your shoulders or fists, then let go for 10 seconds. Work from your feet to your face.
A self-compassion break
Put a hand on your heart and say: "This is hard. Many parents feel this. May I be kind to myself right now." Self-compassion is linked to lower stress in parents.
Check the basics
Hungry, angry, lonely, or tired? Any of these makes everything feel harder. Sometimes a snack, a nap, or a text to a friend is the first step.
Move and get outside
A short walk, stretching, or fresh air with the stroller can lift mood and ease tension, even for ten minutes.
More tools for hard moments: When you feel your temper rising · Without shame
Understanding your nervous system

Your body reacts before you think
Your nervous system is always scanning for safety or danger, mostly below awareness. Many therapists call this neuroception, a term from psychiatrist Stephen Porges. It's why a crying baby, a partner's sigh, or a slammed door can set your heart racing before you've had a single thought. Tap each step.
Three states we move between
A helpful map many therapists use describes three states, like rungs on a ladder. We all move up and down every day; the goal is not to stay calm forever, but to find our way back. Tap a state.
When a trigger makes the past feel present
What happens
A sound, smell, tone of voice, or even a baby's cry can bring back an old memory and the body's survival state at the same time. The room is safe, but the body reacts as if the old danger has returned: racing heart, panic, numbness, or an urge to escape.
Why it matters for parents
Parenting can stir up our own childhood. A child's tantrum or tears may land on an old hurt, which is why reactions can feel bigger than the moment. Noticing "this feels like then, but it's now" is a powerful first step.
How therapy helps
Trauma therapists first help you feel safe and steady in your body, then help you hold a memory while staying connected to the present ("dual awareness"). Therapies such as EMDR, cognitive processing therapy, and prolonged exposure help the brain file memories as past, not present.
Stress hormones, simply explained
This "HPA axis" is helpful in short bursts. When stress never lets up, the system stays switched on, which can affect sleep, mood, blood sugar, and inflammation. What helps it reset is ordinary and powerful: regular sleep and wake times, regular meals, daily movement, slow breathing, daylight, and time with people who feel safe.
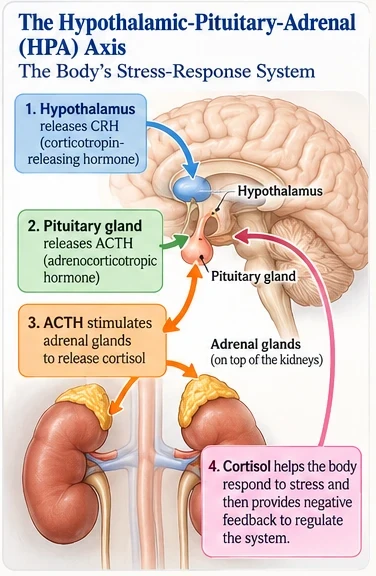
A 4-minute reset
A guided practice to shift toward calm. Follow along; each step lasts about half a minute.
Kind words to start the day
Self-talk works best when it feels believable and kind, not forced. Research suggests that overly positive statements can backfire when we don't believe them, so pick the phrases that ring true for you. Tap a card to see why it helps.
A note on the science: the three-state map comes from polyvagal theory, which is widely used in therapy. Scientists debate parts of its biology, especially claims about specific nerve pathways. The practical lessons, that stress responses are automatic, that they aren't character flaws, and that safety, connection, and calming skills help, are well supported by broader stress research.
Small changes that ripple outward
Big change often starts small. These everyday practices have research behind them, and when parents feel better, the whole family feels it.
Three good things
Each evening, write down three things that went well and why. In a well-known study, this simple habit raised happiness and eased depressive symptoms for months. Counting blessings also improved wellbeing in earlier research.
Journaling
Writing about your deepest thoughts and feelings for 15 to 20 minutes, a few days in a row, has been linked with better mood and health. Writing about your relationship may even strengthen it.
Exercise
In a clinical trial with adults who had depression, regular exercise worked as well as medication, and people who kept exercising were less likely to have depression return. Even a daily stroller walk counts.
Meditation
A large review of clinical trials found mindfulness meditation programs modestly reduce anxiety and depression. A few minutes of focused breathing a day is a good start.
Acts of kindness
Doing a few kind acts in one day each week, like a note to a friend or helping a neighbor, boosted happiness in research on lasting wellbeing.
Your three good things
Try it tonight. Your entries stay private on this device.
When your own past shows up
Many parents carry hard experiences from their own childhood. About 2 in 3 US adults report at least one adverse childhood experience, such as abuse, neglect, or growing up with violence or a parent's untreated mental illness. Unhealed trauma can make stress harder to manage and relationships harder to repair, and parenting can bring old feelings to the surface. Research suggests stress can pass between generations, mostly through parenting and relationships; studies of biological pathways in humans are still early.
It's not your fault
What happened to you as a child wasn't your choice. Noticing patterns isn't blaming yourself or your parents; it's the first step toward choosing something different.
The cycle can break
Healing your own trauma is one of the strongest ways to protect your child. Many parents who had painful childhoods raise children who feel safe and loved, especially with support.
Repair matters most
No parent is perfect. Coming back after a hard moment, apologizing, and reconnecting teaches your child that relationships can mend, something many of us never learned.
Therapies that help
Trauma-focused therapies such as cognitive processing therapy, prolonged exposure, and EMDR have strong research support for adults. Approaches like Internal Family Systems, which works with the protective "parts" we develop, are growing, with early research. It's never too late to heal.
Programs for anger and parenting stress
These programs have research behind them and are offered in many communities, often free or low cost through health departments, schools, and family centers.
ACT Raising Safe Kids
An American Psychological Association program that teaches parents anger management, positive discipline, and how to understand child development. Learn more
Triple P (Positive Parenting Program)
Offered in many countries, from short seminars to individual support, to reduce stress and build confidence. Learn more
Parent-Child Interaction Therapy (PCIT)
A therapist coaches you live, through an earpiece, as you play with your child (usually ages 2 to 7), building warmth and calm limits. Learn more
The Incredible Years
Group programs for parents of babies through school-age children, focused on positive relationships and handling behavior. Learn more
Circle of Security
Helps parents understand their child's emotional needs and strengthen attachment, often in small groups. Learn more
Individual therapy for anger
Cognitive behavioral therapy helps you spot triggers, change angry thought patterns, and practice calmer responses. Ask your provider for a referral.
Kinds of professional help
Talk therapy
Cognitive behavioral therapy (CBT) and interpersonal therapy (IPT) both have strong evidence for depression and anxiety in pregnancy and after birth. Online and phone therapy can work well for busy parents.
Medication
Some medicines are options during pregnancy and breastfeeding. Decide together with a prescriber who knows perinatal care, weighing the risks of treatment and of untreated illness. Don't stop a medicine suddenly on your own.
Couples and family support
Couples counseling can help partners share the load and reconnect. Support groups remind you that you're not alone.
Things nobody tells you about your baby
See all tenFor you: permission to need a break, and to be a good-enough parent.
Where to find support
You're not the only one
Shame keeps parents quiet, and silence makes every struggle feel like yours alone. These are things most families go through but rarely say out loud, from trying to conceive to the teen years and beyond.
Breaking the silence
Research on stigma finds that fear of being judged is one of the main reasons people put off getting help. Every time one parent says "me too," it gets easier for the next. You don't have to tell everyone. Start with one person.
Ways to start
- "Can I tell you something I've been hiding?"
- "This has been harder than I expected, and I haven't said it out loud."
- "Has anything like this happened to you?"
- "I'm not sure it's normal, and I'd like to ask someone."
When someone shares with you
Say "thank you for telling me." Listen before you advise. Skip "at least…" and "everyone feels that way." Offer something concrete, like a meal or an hour of babysitting, and share a helpline if they're struggling.
Where to find your people
Parent groups, your provider's office, library story times, faith and cultural communities, and free online groups from Postpartum Support International all help. Finding your village
Our ethics
Because this is mental health education, WITHIN Learning Group is guided by the standards of the American Counseling Association (ACA) Code of Ethics, the American Mental Health Counselors Association (AMHCA) Code of Ethics, and the American Psychological Association (APA) Ethical Principles and Code of Conduct.
Our commitments
Education, not a counseling relationship
Reading this site, using its tools, or contacting us does not create a counseling, therapy, or medical relationship. We don't diagnose or give individual advice, and nothing here replaces care from a qualified professional. (ACA C.6.c; APA 5.04)
Evidence first, human always
The biopsychosocial lens is our foundation. When we include philosophy, culture, spirituality, or personal reflection, we label it clearly, never present it as research, and never rank one tradition above another. (ACA A.4.b; AMHCA I; APA Principle E)
Grounded in science
What we share is based on peer-reviewed research and established professional guidance. When evidence is early, small, or only shows links, we say so, and we update content when the science changes. (ACA C.6.c, C.7; APA 2.04)
Honest and accurate
We avoid false, misleading, or exaggerated claims. We don't use testimonials, and we accurately represent who we are and our qualifications. (ACA C.3, C.4; AMHCA V; APA 5.01, 5.05)
Do no harm
We write to inform, never to frighten or shame. Hard topics come with what you can do and where to find help, and sensitive topics like eating, self-harm, and loss are handled with care. (ACA A.1; APA Principle A)
Respect for every person
We serve every culture, faith, language, family shape, ability, gender, sexual orientation, and income, and we don't discriminate. We present choices about birth, feeding, faith, and parenting without judgment. (ACA C.5; AMHCA I; APA Principles D and E)
Your privacy
We don't sell your information or track you for ads. Notes, checklists, and saved pages stay in your own browser. If you choose to join our newsletter, we store your email address and any optional details you give, as explained in our privacy policy. (ACA B, H.5; APA 4.01)
No conflicts of interest
We don't run ads, accept sponsorships, or use affiliate links. When we mention a program or organization, it's an example, not an endorsement.
Safety first
Crisis lines are one tap away on every page. If you might be in danger, please call or text 988 in the US, or your local emergency number.
Accessibility and language
Built for everyone
We design for screen readers, keyboard use, readable contrast, reduced motion, and phones. If something doesn't work for you, please tell us. (ACA H.5.d)
Other languages
Key safety information is available in Spanish, French, Mandarin Chinese, Vietnamese, and Italian; these translations are being reviewed by qualified medical translators. For other pages, you can use your browser's translate feature to read this site in your language. Automatic translations are imperfect, so please confirm important health information with your provider, ideally with a qualified interpreter. Many US health care providers must offer one free of charge, so ask.
Check a professional's credentials
Before choosing a counselor or therapist, you can confirm their license with your state's licensing board, for example the Washington State provider credential search, and national certification through the National Board for Certified Counselors. (ACA H.5.b)
American Counseling Association. (2014). ACA code of ethics. · American Mental Health Counselors Association. (2020). AMHCA code of ethics. · American Psychological Association. (2017). Ethical principles of psychologists and code of conduct (2002, amended effective June 1, 2010, and January 1, 2017).
Sources
The research and organizations behind our content.
How we choose sources
We rely first on peer-reviewed research and on government agencies and professional bodies such as the CDC, NIH, HHS, ACOG, and the American Academy of Pediatrics. Hospital and university health libraries add practical, clinician-reviewed detail. We never use Wikipedia.
How we write
We describe what research shows, and what it doesn't yet. When studies are small or only show links rather than causes, we say so. Anything from philosophy, culture, spirituality, or reflection carries a label and is never presented as research. Costs and programs change, so we date them and ask you to check current details.
Help us stay accurate
Spot something outdated or unclear? Let us know. Information here is for education, not a substitute for care from a qualified professional.
- Abraham, E., Hendler, T., Shapira-Lichter, I., Kanat-Maymon, Y., Zagoory-Sharon, O., & Feldman, R. (2014). Father's brain is sensitive to childcare experiences. Proceedings of the National Academy of Sciences, 111(27), 9792–9797.
- Academy of Breastfeeding Medicine. (2014). ABM clinical protocol #4: Mastitis, revised March 2014. Breastfeeding Medicine, 9(5), 239–243. https://doi.org/10.1089/bfm.2014.9984
- Aftab, N. (2025). Social media use during pregnancy: Risks and benefits for women's health. Cureus, 17(8), e90410. https://doi.org/10.7759/cureus.90410
- Agbi, F. A., Zhou, L., & Asamoah, E. O. (2023). Quality of communication between healthcare providers and pregnant women: Impact on maternal satisfaction, health outcomes, and shared decision-making. Universal Journal of Obstetrics and Gynecology, 2(1), 3–10. https://doi.org/10.31586/ujog.2023.784
- Al-Asmakh, M., Anuar, F., Zadjali, F., Rafter, J., & Pettersson, S. (2012). Gut microbial communities modulating brain development and function. Gut Microbes, 3(4), 366–373. https://doi.org/10.4161/gmic.21287
- American College of Obstetricians and Gynecologists Committee on Obstetric Practice & Society for Maternal-Fetal Medicine. (2013). Definition of term pregnancy (Committee Opinion No. 579). Obstetrics & Gynecology, 122(5), 1139–1140.
- American College of Obstetricians and Gynecologists. (2018). Early pregnancy loss (Practice Bulletin No. 200). Obstetrics & Gynecology, 132(5), e197–e207.
- American College of Obstetricians and Gynecologists. (2018). Nausea and vomiting of pregnancy (Practice Bulletin No. 189). Obstetrics & Gynecology, 131(1), e15–e30.
- American College of Obstetricians and Gynecologists. (2020). External cephalic version (Practice Bulletin No. 221). Obstetrics & Gynecology, 135(5), e203–e212.
- American College of Obstetricians and Gynecologists. (2020). Physical activity and exercise during pregnancy and the postpartum period (Committee Opinion No. 804). Obstetrics & Gynecology, 135(4), e178–e188.
- American College of Obstetricians and Gynecologists. (2021). Reducing prenatal exposure to toxic environmental agents (Committee Opinion No. 832). Obstetrics & Gynecology, 138(1), e40–e54.
- American College of Obstetricians and Gynecologists. (2023). Screening and diagnosis of mental health conditions during pregnancy and postpartum (Clinical Practice Guideline No. 4). Obstetrics & Gynecology, 141(6), 1232–1261.
- American Counseling Association. (2014). ACA code of ethics. https://www.counseling.org/docs/default-source/defaultdocument-library/ethics/2014-aca-code-of-ethics.pdf
- American Mental Health Counselors Association. (2020). AMHCA code of ethics. https://www.amhca.org
- American Psychological Association. (2017). Ethical principles of psychologists and code of conduct (2002, amended effective June 1, 2010, and January 1, 2017). https://www.apa.org/ethics/code
- American Psychological Association. (n.d.). ACT Raising Safe Kids Program. https://www.apa.org/act
- Arky, B. (2025, February 5). Calm voices, calmer kids. Child Mind Institute. https://childmind.org/article/calm-voices-calmer-kids/
- Arnett, J. J. (2000). Emerging adulthood: A theory of development from the late teens through the twenties. American Psychologist, 55(5), 469–480. https://doi.org/10.1037/0003-066X.55.5.469
- Babyak, M., Blumenthal, J. A., Herman, S., Khatri, P., Doraiswamy, M., Moore, K., Craighead, W. E., Baldewicz, T. T., & Krishnan, K. R. (2000). Exercise treatment for major depression: Maintenance of therapeutic benefit at 10 months. Psychosomatic Medicine, 62(5), 633–638. https://doi.org/10.1097/00006842-200009000-00006
- Balban, M. Y., Neri, E., Kogon, M. M., Weed, L., Nouriani, B., Jo, B., Holl, G., Zeitzer, J. M., Spiegel, D., & Huberman, A. D. (2023). Brief structured respiration practices enhance mood and reduce physiological arousal. Cell Reports Medicine, 4(1), 100895. https://doi.org/10.1016/j.xcrm.2022.100895
- Barr, R. G., Rivara, F. P., Barr, M., Cummings, P., Taylor, J., Lengua, L. J., & Meredith-Benitz, E. (2009). Effectiveness of educational materials designed to change knowledge and behaviors regarding crying and shaken-baby syndrome in mothers of newborns: A randomized, controlled trial. Pediatrics, 123(3), 972–980. https://doi.org/10.1542/peds.2008-0908
- Bastow, B., & Lakshmin, P. (2021). Gynecological conditions and mental health. In L. A. Hutner, L. A. Catapano, S. M. Nagle-Yang, K. E. Williams, & L. M. Osborne (Eds.), Textbook of women's reproductive mental health (pp. 31–59). American Psychiatric Association Publishing.
- Bath, S. C., Steer, C. D., Golding, J., Emmett, P., & Rayman, M. P. (2013). Effect of inadequate iodine status in UK pregnant women on cognitive outcomes in their children: Results from the Avon Longitudinal Study of Parents and Children (ALSPAC). The Lancet, 382(9889), 331–337. https://doi.org/10.1016/S0140-6736(13)60436-5
- Beighton, C., & Wills, J. (2019). How parents describe the positive aspects of parenting their child who has intellectual disabilities: A systematic review and narrative synthesis. Journal of Applied Research in Intellectual Disabilities, 32(5), 1255–1279. https://doi.org/10.1111/jar.12617
- Belden, A. C., Thomson, N. R., & Luby, J. L. (2008). Temper tantrums in healthy versus depressed and disruptive preschoolers: Defining tantrum behavior associated with clinical problems. The Journal of Pediatrics, 152(1), 117–122. https://doi.org/10.1016/j.jpeds.2007.06.030
- Bendel-Stenzel, L. C., An, D., & Kochanska, G. (2022). Infants' attachment security and children's self-regulation within and outside the parent–child relationship at kindergarten age: Distinct paths for children varying in anger proneness. Journal of Experimental Child Psychology, 221, 105433. https://doi.org/10.1016/j.jecp.2022.105433
- Benderev, M. D. (2025, April 29). What are the most important influences on brain development before birth? ZERO TO THREE. https://www.zerotothree.org/resource/what-are-the-most-important-influences-on-brain-development-before-birth/
- Berge, J. M., MacLehose, R., Loth, K. A., Eisenberg, M., Bucchianeri, M. M., & Neumark-Sztainer, D. (2013). Parent conversations about healthful eating and weight: Associations with adolescent disordered eating behaviors. JAMA Pediatrics, 167(8), 746–753. https://doi.org/10.1001/jamapediatrics.2013.78
- Bitsko, R. H., Claussen, A. H., Lichstein, J., Black, L. I., Jones, S. E., Danielson, M. L., Hoenig, J. M., Davis Jack, S. P., Brody, D. J., Gyawali, S., Maenner, M. J., Warner, M., Holland, K. M., Perou, R., Crosby, A. E., Blumberg, S. J., Avenevoli, S., Kaminski, J. W., & Ghandour, R. M. (2022). Mental health surveillance among children: United States, 2013–2019. MMWR Supplements, 71(2), 1–42. https://doi.org/10.15585/mmwr.su7102a1
- Bohren, M. A., Hofmeyr, G. J., Sakala, C., Fukuzawa, R. K., & Cuthbert, A. (2017). Continuous support for women during childbirth. Cochrane Database of Systematic Reviews, 7, CD003766. https://doi.org/10.1002/14651858.CD003766.pub6
- Borra, C., Iacovou, M., & Sevilla, A. (2015). New evidence on breastfeeding and postpartum depression: The importance of understanding women's intentions. Maternal and Child Health Journal, 19(4), 897–907. https://doi.org/10.1007/s10995-014-1591-z
- Bowers, M. E., & Yehuda, R. (2016). Intergenerational transmission of stress in humans. Neuropsychopharmacology, 41(1), 232–244. https://doi.org/10.1038/npp.2015.247
- Casey, B. J., Jones, R. M., & Hare, T. A. (2008). The adolescent brain. Annals of the New York Academy of Sciences, 1124, 111–126. https://doi.org/10.1196/annals.1440.010
- Center on the Developing Child at Harvard University. (n.d.). Brain architecture; Serve and return; Toxic stress. https://developingchild.harvard.edu
- Centers for Disease Control and Prevention. (2024). About adverse childhood experiences. https://www.cdc.gov/aces/about/index.html
- Centers for Disease Control and Prevention. (2024). Youth Risk Behavior Survey data summary & trends report: 2013–2023. https://www.cdc.gov/yrbs/dstr/index.html
- Centers for Disease Control and Prevention. (2024, May 15). Urgent maternal warning signs and symptoms. Hear Her campaign. https://www.cdc.gov/hearher/maternal-warning-signs/index.html
- Centers for Disease Control and Prevention. (2026, July 14). Planning for pregnancy. https://www.cdc.gov/pregnancy/about/index.html
- Centers for Disease Control and Prevention. (n.d.). About alcohol use during pregnancy. https://www.cdc.gov/alcohol-pregnancy/about/index.html
- Centers for Disease Control and Prevention. (n.d.). Assisted reproductive technology (ART). https://www.cdc.gov/art/
- Centers for Disease Control and Prevention. (n.d.). Births: Method of delivery. https://www.cdc.gov/nchs/fastats/delivery.htm
- Centers for Disease Control and Prevention. (n.d.). Folic acid: Facts for clinicians; About alcohol use during pregnancy; Learn the signs. Act early: Milestone Tracker. https://www.cdc.gov
- Centers for Disease Control and Prevention. (n.d.). Gestational diabetes. https://www.cdc.gov/diabetes/about/gestational-diabetes.html
- Centers for Disease Control and Prevention. (n.d.). Learn the signs. Act early. https://www.cdc.gov/act-early/
- Centers for Disease Control and Prevention. (n.d.). Preterm birth. https://www.cdc.gov/maternal-infant-health/preterm-birth/index.html
- Centers for Disease Control and Prevention. (n.d.). What is stillbirth? https://www.cdc.gov/stillbirth/about/index.html
- Children's Hospital Colorado. (2023, March 15). A parent's guide to neurodiversity. https://www.childrenscolorado.org/just-ask-childrens/articles/neurodiversity/
- Children's National Hospital. (2016, October 28). Every day that fetuses remain in utero critical to preserving normal brain development [Press release]. https://www.childrensnational.org/about-us/newsroom/2016/every-day-that-fetuses-remain-in-utero-critical-to-preserving-normal-brain-development
- Clement, S., Schauman, O., Graham, T., et al. (2015). What is the impact of mental health-related stigma on help-seeking? A systematic review of quantitative and qualitative studies. Psychological Medicine, 45(1), 11–27.
- Cleveland Clinic. (2022, June 2). Neurodivergent. https://my.clevelandclinic.org/health/symptoms/23154-neurodivergent
- Cleveland Clinic. (2024, February 12). Nurse midwife vs. doula: Who does what? Health Essentials. https://health.clevelandclinic.org/doula-vs-midwife
- Cleveland Clinic. (2026, May 26). Conception. https://my.clevelandclinic.org/health/articles/11585-conception
- Cleveland Clinic. (n.d.). Am I pregnant? https://my.clevelandclinic.org/health/articles/9709-pregnancy-am-i-pregnant
- Cohen, G. L., & Sherman, D. K. (2014). The psychology of change: Self-affirmation and social psychological intervention. Annual Review of Psychology, 65, 333–371. https://doi.org/10.1146/annurev-psych-010213-115137
- Corrigan, P. W., & Watson, A. C. (2002). Understanding the impact of stigma on people with mental illness. World Psychiatry, 1(1), 16–20.
- Council on Communications and Media. (2016). Media and young minds. Pediatrics, 138(5), e20162591. https://doi.org/10.1542/peds.2016-2591
- Covey, S. (2008). The 7 habits of happy kids. Simon & Schuster Books for Young Readers.
- Cryan, J. F., O'Riordan, K. J., Cowan, C. S. M., et al. (2019). The microbiota-gut-brain axis. Physiological Reviews, 99(4), 1877–2013.
- Dana, D. (2018). The polyvagal theory in therapy: Engaging the rhythm of regulation. W. W. Norton.
- Dazzi, T., Gribble, R., Wessely, S., & Fear, N. T. (2014). Does asking about suicide and related behaviours induce suicidal ideation? What is the evidence? Psychological Medicine, 44(16), 3361–3363. https://doi.org/10.1017/S0033291714001299
- Dennis, C.-L., & Chung-Lee, L. (2006). Postpartum depression help-seeking barriers and maternal treatment preferences: A qualitative systematic review. Birth, 33(4), 323–331.
- Doctrow, B. (2024). Brain changes observed during pregnancy. NIH Research Matters. National Institutes of Health. https://www.nih.gov/news-events/nih-research-matters/brain-changes-observed-during-pregnancy
- DONA International. (n.d.). Find a DONA certified doula. https://dona.org/find-a-dona-certified-doula/
- Durlak, J. A., Weissberg, R. P., Dymnicki, A. B., Taylor, R. D., & Schellinger, K. B. (2011). The impact of enhancing students' social and emotional learning: A meta-analysis of school-based universal interventions. Child Development, 82(1), 405–432. https://doi.org/10.1111/j.1467-8624.2010.01564.x
- Emmons, R. A., & McCullough, M. E. (2003). Counting blessings versus burdens: An experimental investigation of gratitude and subjective well-being in daily life. Journal of Personality and Social Psychology, 84(2), 377–389. https://doi.org/10.1037/0022-3514.84.2.377
- Eunice Kennedy Shriver National Institute of Child Health and Human Development. (2024). About pregnancy. National Institutes of Health. https://www.nichd.nih.gov/health/topics/pregnancy/conditioninfo
- Faber, A., & Mazlish, E. (2012). How to talk so kids will listen & listen so kids will talk (30th anniversary ed.). Scribner.
- Fairbrother, N., & Woody, S. R. (2008). New mothers' thoughts of harm related to the newborn. Archives of Women's Mental Health, 11(3), 221–229. https://doi.org/10.1007/s00737-008-0016-7
- Felitti, V. J., Anda, R. F., Nordenberg, D., et al. (1998). Relationship of childhood abuse and household dysfunction to many of the leading causes of death in adults. American Journal of Preventive Medicine, 14(4), 245–258.
- Fitzgerald, E., Hor, K., & Drake, A. J. (2020). Maternal influences on fetal brain development: The role of nutrition, infection and stress, and the potential for intergenerational consequences. Early Human Development, 150, 105190. https://doi.org/10.1016/j.earlhumdev.2020.105190
- Fraga, J., & Hendel, H. J. (2025, December 16). Four ways for parents to manage their emotions. Greater Good Magazine. https://greatergood.berkeley.edu/article/item/four_ways_for_parents_to_manage_their_emotions
- Gottman, J. M., Katz, L. F., & Hooven, C. (1996). Parental meta-emotion philosophy and the emotional life of families: Theoretical models and preliminary data. Journal of Family Psychology, 10(3), 243–268. https://doi.org/10.1037/0893-3200.10.3.243
- Goyal, M., Singh, S., Sibinga, E. M. S., Gould, N. F., Rowland-Seymour, A., Sharma, R., Berger, Z., Sleicher, D., Maron, D. D., Shihab, H. M., Ranasinghe, P. D., Linn, S., Saha, S., Bass, E. B., & Haythornthwaite, J. A. (2014). Meditation programs for psychological stress and well-being: A systematic review and meta-analysis. JAMA Internal Medicine, 174(3), 357–368. https://doi.org/10.1001/jamainternmed.2013.13018
- Grossman, P. (2023). Fundamental challenges and likely refutations of the five basic premises of the polyvagal theory. Biological Psychology, 180, 108589. https://doi.org/10.1016/j.biopsycho.2023.108589
- Guinhouya, B. C., Duclos, M., Enea, C., & Storme, L. (2022). Beneficial effects of maternal physical activity during pregnancy on fetal, newborn, and child health: Guidelines for interventions during the perinatal period from the French National College of Midwives. Journal of Midwifery & Women's Health, 67(Suppl. 1), S149–S157.
- Gunderson, E. A., Gripshover, S. J., Romero, C., Dweck, C. S., Goldin-Meadow, S., & Levine, S. C. (2013). Parent praise to 1- to 3-year-olds predicts children's motivational frameworks 5 years later. Child Development, 84(5), 1526–1541. https://doi.org/10.1111/cdev.12064
- Harrison, M. E., Norris, M. L., Obeid, N., Fu, M., Weinstangel, H., & Sampson, M. (2015). Systematic review of the effects of family meal frequency on psychosocial outcomes in youth. Canadian Family Physician, 61(2), e96–e106.
- HealthPartners. (2026, February 5). Midwife vs. OB-GYN: How to choose an expert for pregnancy care. https://www.healthpartners.com/blog/midwife-vs-obgyn-whats-the-difference/
- Hoekzema, E., Barba-Müller, E., Pozzobon, C., et al. (2017). Pregnancy leads to long-lasting changes in human brain structure. Nature Neuroscience, 20(2), 287–296.
- Hopkins, E., & Luecking, C. (2024). Brain food: Essential nutrients to support baby's brain development in pregnancy. University of Kentucky Cooperative Extension.
- Hudepohl, N. S., Coker, J. L., Shivanekar, S. P., Nagalla, M.-L., Givrad, S., Standeven, L. R., & Erdly, C. (2021). Infertility and perinatal loss. In L. A. Hutner, L. A. Catapano, S. M. Nagle-Yang, K. E. Williams, & L. M. Osborne (Eds.), Textbook of women's reproductive mental health (pp. 113–151). American Psychiatric Association Publishing.
- Hunziker, U. A., & Barr, R. G. (1986). Increased carrying reduces infant crying: A randomized controlled trial. Pediatrics, 77(5), 641–648.
- Internal Revenue Service. (2026, March 3). Tax benefits for parents and families (Tax Tip 2026-17). https://www.irs.gov/newsroom/tax-benefits-for-parents-and-families
- Internal Revenue Service. (2026, March 31). 4 million children have been signed up for Trump Accounts with 1 million claiming the $1,000 pilot program contribution (IR-2026-42). https://www.irs.gov/newsroom/4-million-children-have-been-signed-up-for-trump-accounts-with-1-million-claiming-the-1000-pilot-program-contribution
- Internal Revenue Service. (2026, September 21). Child Tax Credit. https://www.irs.gov/credits-deductions/individuals/child-tax-credit
- Irvine, N., England-Mason, G., Field, C. J., Dewey, D., & Aghajafari, F. (2022). Prenatal folate and choline levels and brain and cognitive development in children: A critical narrative review. Nutrients, 14(2), 364. https://doi.org/10.3390/nu14020364
- Irwin, V., Wang, K., Cui, J., & Thompson, A. (2022). Report on indicators of school crime and safety: 2021 (NCES 2022-092). National Center for Education Statistics.
- Jacka, F. N., Ystrom, E., Brantsaeter, A. L., Karevold, E., Roth, C., Haugen, M., Meltzer, H. M., Schjolberg, S., & Berk, M. (2013). Maternal and early postnatal nutrition and mental health of offspring by age 5: A prospective cohort study. Journal of the American Academy of Child & Adolescent Psychiatry, 52(10), 1038–1047. https://doi.org/10.1016/j.jaac.2013.07.002
- Kessler, R. C., Berglund, P., Demler, O., Jin, R., Merikangas, K. R., & Walters, E. E. (2005). Lifetime prevalence and age-of-onset distributions of DSM-IV disorders. Archives of General Psychiatry, 62(6), 593–602.
- KFF. (2026, July 15). Medicaid postpartum coverage extension tracker. https://www.kff.org/medicaid/medicaid-postpartum-coverage-extension-tracker/
- Kim, G.-H., & Shim, J.-O. (2022). Gut microbiota affects brain development and behavior. Clinical and Experimental Pediatrics, 66(7), 274–280. https://doi.org/10.3345/cep.2021.01550
- Knickmeyer, R. C., Gouttard, S., Kang, C., et al. (2008). A structural MRI study of human brain development from birth to 2 years. Journal of Neuroscience, 28(47), 12176–12182.
- Knudson-Martin, C., & Huenergardt, D. (2015). Bridging emotion, societal discourse, and couple interaction in clinical practice. In C. Knudson-Martin, S. K. Samman, & M. A. Wells (Eds.), Socio-emotional relationship therapy: Bridging emotion, societal context, and couple interaction. Springer.
- Labonté-LeMoyne, É., Curnier, D., & Ellemberg, D. (2017). Exercise during pregnancy enhances cerebral maturation in the newborn: A randomized controlled trial. Journal of Clinical and Experimental Neuropsychology, 39(4), 347–354.
- Lino, M., Kuczynski, K., Rodriguez, N., & Schap, T. (2017). Expenditures on children by families, 2015 (Miscellaneous Publication No. 1528-2015). US Department of Agriculture, Center for Nutrition Policy and Promotion.
- Lyubomirsky, S., Sheldon, K. M., & Schkade, D. (2005). Pursuing happiness: The architecture of sustainable change. Review of General Psychology, 9(2), 111–131. https://doi.org/10.1037/1089-2680.9.2.111
- Madula, P., Kalembo, F. W., Yu, H., & Kaminga, A. C. (2018). Healthcare provider-patient communication: A qualitative study of women's perceptions during childbirth. Reproductive Health, 15, 135. https://doi.org/10.1186/s12978-018-0580-x
- Makrides, M., Gibson, R. A., McPhee, A. J., Yelland, L., Quinlivan, J., Ryan, P., & DOMInO Investigative Team. (2010). Effect of DHA supplementation during pregnancy on maternal depression and neurodevelopment of young children: A randomized controlled trial. JAMA, 304(15), 1675–1683. https://doi.org/10.1001/jama.2010.1507
- Marconi, A., Di Forti, M., Lewis, C. M., Murray, R. M., & Vassos, E. (2016). Meta-analysis of the association between the level of cannabis use and risk of psychosis. Schizophrenia Bulletin, 42(5), 1262–1269.
- Maternal Mental Health Leadership Alliance. (2025, August). Maternal mental health overview [Fact sheet]. https://www.mmhla.org
- Mayo Clinic Staff. (2025, January 31). Pregnancy diet: Focus on these essential nutrients. Mayo Clinic. https://www.mayoclinic.org/healthy-lifestyle/pregnancy-week-by-week/in-depth/pregnancy-nutrition/art-20045082
- McDowell, T., Knudson-Martin, C., & Bermudez, J. M. (2017). Socioculturally attuned family therapy: Guidelines for equitable theory and practice. Routledge.
- McEwen, B. S. (1998). Protective and damaging effects of stress mediators. New England Journal of Medicine, 338(3), 171–179. https://doi.org/10.1056/NEJM199801153380307
- McQueen, J. (2025, February 4). Doctor, doula, midwife: Which is right for you? WebMD. https://www.webmd.com/baby/doctor-doula-midwife
- MedlinePlus. (n.d.). Pregnancy. National Library of Medicine. https://medlineplus.gov/pregnancy.html
- Moffitt, T. E., Arseneault, L., Belsky, D., Dickson, N., Hancox, R. J., Harrington, H., Houts, R., Poulton, R., Roberts, B. W., Ross, S., Sears, M. R., Thomson, W. M., & Caspi, A. (2011). A gradient of childhood self-control predicts health, wealth, and public safety. Proceedings of the National Academy of Sciences, 108(7), 2693–2698. https://doi.org/10.1073/pnas.1010076108
- Monroe, S. M., & Simons, A. D. (1991). Diathesis-stress theories in the context of life stress research. Psychological Bulletin, 110(3), 406–425.
- Mueller, C. M., & Dweck, C. S. (1998). Praise for intelligence can undermine children's motivation and performance. Journal of Personality and Social Psychology, 75(1), 33–52. https://doi.org/10.1037/0022-3514.75.1.33
- Muskens, L., Boekhorst, M. G. B. M., Pop, V. J. M., & van den Heuvel, M. I. (2024). Browsing throughout pregnancy: The longitudinal course of social media use during pregnancy. Midwifery, 129, 103905. https://doi.org/10.1016/j.midw.2023.103905
- Na, X., Mackean, P. P., Cape, G. A., Johnson, J. W., & Ou, X. (2024). Maternal nutrition during pregnancy and offspring brain development: Insights from neuroimaging. Nutrients, 16(19), 3337. https://doi.org/10.3390/nu16193337
- Na, X., Raja, R., Phelan, N. E., Tadros, M. R., Moore, A., Wu, Z., Wang, L., Li, G., Glasier, C. M., Ramakrishnaiah, R. R., Andres, A., & Ou, X. (2022). Mother's physical activity during pregnancy and newborn's brain cortical development. Frontiers in Human Neuroscience, 16, 943341. https://doi.org/10.3389/fnhum.2022.943341
- National Health Service. (n.d.). Trying to get pregnant. https://www.nhs.uk/pregnancy/trying-for-a-baby/trying-to-get-pregnant/
- National Institutes of Health, Office of Dietary Supplements. (n.d.). Dietary supplement fact sheets: Folate; Choline; Iodine; Iron. https://ods.od.nih.gov/factsheets/list-all/
- National Scientific Council on the Developing Child. (2014). Excessive stress disrupts the architecture of the developing brain (Working Paper 3, updated ed.). Center on the Developing Child at Harvard University. https://developingchild.harvard.edu/resources/wp3/
- Neff, K. D., & Faso, D. J. (2015). Self-compassion and well-being in parents of children with autism. Mindfulness, 6(4), 938–947. https://doi.org/10.1007/s12671-014-0359-2
- New York Life. (2026). How much does a baby cost per month in the first year? https://www.newyorklife.com/articles/breakdown-of-biggest-expenses-for-your-child
- Niño Cruz, G. I., Ramirez Varela, A., da Silva, I. C. M., Hallal, P. C., & Santos, I. S. (2018). Physical activity during pregnancy and offspring neurodevelopment: A systematic review. Paediatric and Perinatal Epidemiology, 32, 369–379. https://doi.org/10.1111/ppe.12472
- Nolvi, S., Merz, E. C., Kataja, E.-L., & Parsons, C. E. (2023). Prenatal stress and the developing brain: Postnatal environments promoting resilience. Biological Psychiatry, 93(10), 942–952. https://doi.org/10.1016/j.biopsych.2022.11.023
- Northwell Health. (n.d.). What the science reveals about brain remodeling during pregnancy [Interview with D. Zilberman]. https://www.northwell.edu
- O'Neil, A., Quirk, S. E., Housden, S., Brennan, S. L., Williams, L. J., Pasco, J. A., Berk, M., & Jacka, F. N. (2014). Relationship between diet and mental health in children and adolescents: A systematic review. American Journal of Public Health, 104(10), e31–e42. https://doi.org/10.2105/AJPH.2014.302110
- Office on Women's Health. (2025, September 26). Stages of pregnancy. US Department of Health and Human Services. https://www.womenshealth.gov/pregnancy/youre-pregnant-now-what/stages-pregnancy
- Paruthi, S., Brooks, L. J., D'Ambrosio, C., Hall, W. A., Kotagal, S., Lloyd, R. M., Malow, B. A., Maski, K., Nichols, C., Quan, S. F., Rosen, C. L., Troester, M. M., & Wise, M. S. (2016). Recommended amount of sleep for pediatric populations: A consensus statement of the American Academy of Sleep Medicine. Journal of Clinical Sleep Medicine, 12(6), 785–786. https://doi.org/10.5664/jcsm.5866
- Paulson, J. F., & Bazemore, S. D. (2010). Prenatal and postpartum depression in fathers and its association with maternal depression: A meta-analysis. JAMA, 303(19), 1961–1969.
- Pennebaker, J. W. (1997). Writing about emotional experiences as a therapeutic process. Psychological Science, 8(3), 162–166. https://doi.org/10.1111/j.1467-9280.1997.tb00403.x
- PEPS. (n.d.). Real support for parents. https://peps.org/
- Pinhorn, L. (2018, September 19). Raising exceptional families with special needs children. The Gottman Institute. https://www.gottman.com/blog/raising-exceptional-families-with-special-needs-children/
- Planned Parenthood. (n.d.). How pregnancy happens. https://www.plannedparenthood.org/learn/pregnancy/how-pregnancy-happens
- Porges, S. W. (2022). Polyvagal theory: A science of safety. Frontiers in Integrative Neuroscience, 16, 871227. https://doi.org/10.3389/fnint.2022.871227
- Postpartum Support International. (2024). Perinatal Mental Health Certification program candidate handbook. https://www.postpartum.net/professionals/certification/
- Pritschet, L., Taylor, C. M., Cossio, D., Faskowitz, J., Santander, T., Handwerker, D. A., Grotzinger, H., Layher, E., Chrastil, E. R., & Jacobs, E. G. (2024). Neuroanatomical changes observed over the course of a human pregnancy. Nature Neuroscience, 27(11), 2253–2260. https://doi.org/10.1038/s41593-024-01741-0
- Rae, M., Cox, C., & Dingel, H. (2022, July 13). Health costs associated with pregnancy, childbirth, and postpartum care. Peterson-KFF Health System Tracker. https://www.healthsystemtracker.org/brief/health-costs-associated-with-pregnancy-childbirth-and-postpartum-care/
- Raising Children Network. (2026, July 17). Anger management guide for parents. https://raisingchildren.net.au/guides/first-1000-days/looking-after-yourself/anger-management-for-parents
- Ramchandani, P., Stein, A., Evans, J., O'Connor, T. G., & ALSPAC Study Team. (2005). Paternal depression in the postnatal period and child development: A prospective population study. The Lancet, 365(9478), 2201–2205. https://doi.org/10.1016/S0140-6736(05)66778-5
- Ray, D. C. (Ed.). (2016). A therapist's guide to child development: The extraordinarily normal years. Routledge.
- Resnick, M. D., Bearman, P. S., Blum, R. W., Bauman, K. E., Harris, K. M., Jones, J., Tabor, J., Beuhring, T., Sieving, R. E., Shew, M., Ireland, M., Bearinger, L. H., & Udry, J. R. (1997). Protecting adolescents from harm: Findings from the National Longitudinal Study on Adolescent Health. JAMA, 278(10), 823–832. https://doi.org/10.1001/jama.1997.03550100049038
- Romeo, R. R., Leonard, J. A., Robinson, S. T., West, M. R., Mackey, A. P., Rowe, M. L., & Gabrieli, J. D. E. (2018). Beyond the 30-million-word gap: Children's conversational exposure is associated with language-related brain function. Psychological Science, 29(5), 700–710. https://doi.org/10.1177/0956797617742725
- Ryan, C., Huebner, D., Diaz, R. M., & Sanchez, J. (2009). Family rejection as a predictor of negative health outcomes in white and Latino lesbian, gay, and bisexual young adults. Pediatrics, 123(1), 346–352. https://doi.org/10.1542/peds.2007-3524
- Sanders, M. R., Kirby, J. N., Tellegen, C. L., & Day, J. J. (2014). The Triple P–Positive Parenting Program: A systematic review and meta-analysis of a multi-level system of parenting support. Clinical Psychology Review, 34(4), 337–357. https://doi.org/10.1016/j.cpr.2014.04.003
- Sarkadi, A., Kristiansson, R., Oberklaid, F., & Bremberg, S. (2008). Fathers' involvement and children's developmental outcomes: A systematic review of longitudinal studies. Acta Paediatrica, 97(2), 153–158. https://doi.org/10.1111/j.1651-2227.2007.00572.x
- Schwarzenberg, S. J., Georgieff, M. K., & Committee on Nutrition. (2018). Advocacy for improving nutrition in the first 1000 days to support childhood development and adult health. Pediatrics, 141(2), e20173716. https://doi.org/10.1542/peds.2017-3716
- Seligman, M. E. P., Steen, T. A., Park, N., & Peterson, C. (2005). Positive psychology progress: Empirical validation of interventions. American Psychologist, 60(5), 410–421. https://doi.org/10.1037/0003-066X.60.5.410
- Shapiro, A. F., Gottman, J. M., & Carrère, S. (2000). The baby and the marriage. Journal of Family Psychology, 14(1), 59–70.
- Shapiro, F. (2018). Eye movement desensitization and reprocessing (EMDR) therapy: Basic principles, protocols, and procedures (3rd ed.). Guilford Press.
- Shonkoff, J. P., Garner, A. S., Committee on Psychosocial Aspects of Child and Family Health, Committee on Early Childhood, Adoption, and Dependent Care, & Section on Developmental and Behavioral Pediatrics. (2012). The lifelong effects of early childhood adversity and toxic stress. Pediatrics, 129(1), e232–e246. https://doi.org/10.1542/peds.2011-2663
- Shonkoff, J. P., Garner, A. S., et al. (2012). The lifelong effects of early childhood adversity and toxic stress. Pediatrics, 129(1), e232–e246.
- Simkin, P. (n.d.). How the doula helps during a breech version [Handout]. DONA International.
- Slatcher, R. B., & Pennebaker, J. W. (2006). How do I love thee? Let me count the words: The social effects of expressive writing. Psychological Science, 17(8), 660–664. https://doi.org/10.1111/j.1467-9280.2006.01762.x
- Soet, J. E., Brack, G. A., & DiIorio, C. (2003). Prevalence and predictors of women's experience of psychological trauma during childbirth. Birth, 30(1), 36–46. https://doi.org/10.1046/j.1523-536X.2003.00215.x
- Spong, C. Y. (2013). Defining "term" pregnancy: Recommendations from the Defining "Term" Pregnancy Workgroup. JAMA, 309(23), 2445–2446. https://doi.org/10.1001/jama.2013.6235
- Stanford Medicine Children's Health. (n.d.). Anger management: Strategies for parents and grandparents. https://www.stanfordchildrens.org/en/topic/default?id=anger-management-strategies-for-parents-and-grandparents-160-45
- Stein, A., Pearson, R. M., Goodman, S. H., Rapa, E., Rahman, A., McCallum, M., Howard, L. M., & Pariante, C. M. (2014). Effects of perinatal mental disorders on the fetus and child. The Lancet, 384(9956), 1800–1819. https://doi.org/10.1016/S0140-6736(14)61277-0
- Steinberg, L. (2001). We know some things: Parent-adolescent relationships in retrospect and prospect. Journal of Research on Adolescence, 11(1), 1–19. https://doi.org/10.1111/1532-7795.00001
- Stewart, R. (2016, June 14). Soon-to-be dads: How to help – and what not to say – during pregnancy. UT Southwestern Medical Center MedBlog. https://utswmed.org/medblog/fathers-guide-to-pregnancy/
- Stoll, B. J., Hansen, N. I., Bell, E. F., Shankaran, S., Laptook, A. R., Walsh, M. C., et al. (2010). Neonatal outcomes of extremely preterm infants from the NICHD Neonatal Research Network. Pediatrics, 126(3), 443–456. https://doi.org/10.1542/peds.2009-2959
- Susser, E., Neugebauer, R., Hoek, H. W., Brown, A. S., Lin, S., Labovitz, D., & Gorman, J. M. (1996). Schizophrenia after prenatal famine: Further evidence. Archives of General Psychiatry, 53(1), 25–31. https://doi.org/10.1001/archpsyc.1996.01830010027005
- Tangney, J. P., Stuewig, J., & Mashek, D. J. (2007). Moral emotions and moral behavior. Annual Review of Psychology, 58, 345–372.
- The Royal Children's Hospital Melbourne. (2026, May). Understanding behaviour – school-age children [Fact sheet]. https://www.rch.org.au/kidsinfo/fact_sheets/Challenging_behaviour_school_aged_children/
- Tronick, E., Als, H., Adamson, L., Wise, S., & Brazelton, T. B. (1978). The infant's response to entrapment between contradictory messages in face-to-face interaction. Journal of the American Academy of Child Psychiatry, 17(1), 1–13. https://doi.org/10.1016/S0002-7138(09)62273-1
- Trost, S. L., Beauregard, J., Njie, F., Harvey, E. M., Chandra, G., Zhang, Y., Byrd, J., Petersen, E. E., & Goodman, D. A. (2022). Pregnancy-related deaths: Data from maternal mortality review committees in 36 US states, 2017–2019. Centers for Disease Control and Prevention.
- UC Berkeley School of Public Health. (2021, May 20). New research shows that early fetal brain development is key to neurodevelopment. https://publichealth.berkeley.edu/articles/spotlight/research/early-fetal-brain-development-is-key-to-neurodevelopment
- US Department of Education, Office of Special Education and Rehabilitative Services. (2022, July 19). Positive, proactive approaches to supporting children with disabilities: A guide for stakeholders (OSEP Policy Support 22-01). https://sites.ed.gov/idea/idea-files/guide-positive-proactive-approaches-to-supporting-children-with-disabilities/
- US Department of Health and Human Services. (2025, December 22). Government programs and benefits for your family. https://www.hhs.gov/healthcare/maternal-health/newborn-supply-kit/support-for-family/index.html
- US Department of Health and Human Services. (n.d.). Moms.gov: Resources for pregnancy, maternal health, newborn care, and family support. https://www.moms.gov/
- US Department of Health and Human Services. (n.d.). Research involving pregnant women or fetuses, 45 C.F.R. § 46.204. https://www.ecfr.gov
- US Food and Drug Administration. (n.d.). Advice about eating fish. https://www.fda.gov/food/consumers/advice-about-eating-fish
- US Preventive Services Task Force. (2019). Interventions to prevent perinatal depression: Recommendation statement. JAMA, 321(6), 580–587.
- Valpey, R., Sachdeva, J., & Moel, J. E. (2021). Eating disorders. In L. A. Hutner, L. A. Catapano, S. M. Nagle-Yang, K. E. Williams, & L. M. Osborne (Eds.), Textbook of women's reproductive mental health (pp. 619–645). American Psychiatric Association Publishing.
- Van den Bergh, B. R. H., van den Heuvel, M. I., Lahti, M., et al. (2020). Prenatal developmental origins of behavior and mental health: The influence of maternal stress in pregnancy. Neuroscience & Biobehavioral Reviews, 117, 26–64.
- van IJzendoorn, M. H. (1995). Adult attachment representations, parental responsiveness, and infant attachment: A meta-analysis on the predictive validity of the Adult Attachment Interview. Psychological Bulletin, 117(3), 387–403. https://doi.org/10.1037/0033-2909.117.3.387
- Vedam, S., Stoll, K., Taiwo, T. K., Rubashkin, N., Cheyney, M., Strauss, N., McLemore, M., Cadena, M., Nethery, E., Rushton, E., Schummers, L., Declercq, E., & GVtM-US Steering Council. (2019). The Giving Voice to Mothers study: Inequity and mistreatment during pregnancy and childbirth in the United States. Reproductive Health, 16, 77. https://doi.org/10.1186/s12978-019-0729-2
- Verny, T. R., & Kelly, J. (1981). The Secret Life of the Unborn Child. Cited as a historical perspective, not as scientific evidence.
- Wang, M.-T., & Kenny, S. (2014). Longitudinal links between fathers' and mothers' harsh verbal discipline and adolescents' conduct problems and depressive symptoms. Child Development, 85(3), 908–923. https://doi.org/10.1111/cdev.12143
- Washington State Department of Social and Health Services. (n.d.). Pregnant Women Assistance program. https://www.dshs.wa.gov/family-food-and-housing-services/cash-assistance/pregnant-women-assistance-program
- Wassef, A., Nguyen, Q. D., & St-André, M. (2019). Anaemia and depletion of iron stores as risk factors for postpartum depression: A literature review. Journal of Psychosomatic Obstetrics & Gynecology, 40(1), 19–28. https://doi.org/10.1080/0167482X.2018.1427725
- Weissman, M. M., Pilowsky, D. J., Wickramaratne, P. J., Talati, A., Wisniewski, S. R., Fava, M., Hughes, C. W., Garber, J., Malloy, E., King, C. A., Cerda, G., Sood, A. B., Alpert, J. E., Trivedi, M. H., & Rush, A. J. (2006). Remissions in maternal depression and child psychopathology: A STAR*D-Child report. JAMA, 295(12), 1389–1398. https://doi.org/10.1001/jama.295.12.1389
- Wenze, S. J., Battle, C. L., & Tezanos, K. M. (2015). Raising multiples: Mental health of mothers and fathers in early parenthood. Archives of Women's Mental Health, 18, 163–176. https://doi.org/10.1007/s00737-014-0484-x
- Wesley, A. L., Zein, M., Olgun, M., & Catapano, L. A. (2021). The reproductive life cycle. In L. A. Hutner, L. A. Catapano, S. M. Nagle-Yang, K. E. Williams, & L. M. Osborne (Eds.), Textbook of women's reproductive mental health (pp. 3–29). American Psychiatric Association Publishing.
- Widman, L., Choukas-Bradley, S., Noar, S. M., Nesi, J., & Garrett, K. (2016). Parent-adolescent sexual communication and adolescent safer sex behavior: A meta-analysis. JAMA Pediatrics, 170(1), 52–61. https://doi.org/10.1001/jamapediatrics.2015.2731
- Wood, J. V., Perunovic, W. Q. E., & Lee, J. W. (2009). Positive self-statements: Power for some, peril for others. Psychological Science, 20(7), 860–866. https://doi.org/10.1111/j.1467-9280.2009.02370.x
- World Health Organization. (2023). Infertility prevalence estimates, 1990–2021. https://www.who.int/publications/i/item/978920068315
- Wu, Y., De Asis-Cruz, J., & Limperopoulos, C. (2024). Brain structural and functional outcomes in the offspring of women experiencing psychological distress during pregnancy. Molecular Psychiatry, 29, 2223–2240. https://doi.org/10.1038/s41380-024-02449-0
- Yildiz, P. D., Ayers, S., & Phillips, L. (2017). The prevalence of posttraumatic stress disorder in pregnancy and after birth: A systematic review and meta-analysis. Journal of Affective Disorders, 208, 634–645. https://doi.org/10.1016/j.jad.2016.10.009
- Younis, J., Bleibel, M., El Masri, J., Ismail, A., & AbouAbbas, L. (2025). Exploring the influence of pregnancy on cognitive function in women: A systematic review. BMC Pregnancy and Childbirth, 25, 88. https://doi.org/10.1186/s12884-025-07181-3
- Zablotsky, B., Black, L. I., Maenner, M. J., Schieve, L. A., Danielson, M. L., Bitsko, R. H., Blumberg, S. J., Kogan, M. D., & Boyle, C. A. (2019). Prevalence and trends of developmental disabilities among children in the United States: 2009–2017. Pediatrics, 144(4), e20190811. https://doi.org/10.1542/peds.2019-0811
- Zubrick, S. R., Taylor, C. L., Rice, M. L., & Slegers, D. W. (2007). Late language emergence at 24 months: An epidemiological study of prevalence, predictors, and covariates. Journal of Speech, Language, and Hearing Research, 50(6), 1562–1592. https://doi.org/10.1044/1092-4388(2007/106)
The weekly newsletter
One short, kind, research-based email a week, matched to where you are in your journey. Free, and by email only.
Our newsletter isn't open yet
We're still building it. When it opens, we'll announce it here. Until then, nothing is collected and nothing is sent. You can read everything on this site. Have an idea or a question? Contact us
Welcome!
Our promises
- Free. One email a week, by email only. No postal mail.
- Private. We never sell your details, we share them only with the services that host and send your email, and there are no ads.
- Your choice. Your stage only decides which email you get. We ask for nothing else.
- Easy to leave. One-click unsubscribe in every email.
- Honest. We say what research shows and what it doesn't yet. Every email is a conversation starter to bring to your own professionals.
Read how we handle your information in our privacy policy and consumer health data privacy policy.
Consumer health data privacy policy
Some information you choose to give us can reveal something about your health or pregnancy. This page explains exactly what that is, why we ask, who sees it, and how you stay in control. It goes with our privacy policy.
WITHIN LEARNING GROUP LLC · Effective October 12, 2026 · Last updated October 12, 2026
1. What health-related information we collect
Only one thing: the stage you may choose when you join our newsletter or change your preferences (for example "pregnant" or "thinking about a baby"). It is linked to your email address, and we record the agreement you gave. Choosing a stage is always optional, and "Prefer not to say" stores nothing about your health. We do not collect any other health information on our servers. What you type into the tools on this site (notes, checklists, and so on) stays on your own device and is not sent to us.
2. Why we collect it
- To choose which weekly email to send you.
- To keep a record of your agreement.
- To honor your requests to change or delete it.
We do not use it for advertising or to build a profile of you.
3. Where it comes from
Only from you, through the newsletter form or the preferences link in your emails.
4. Who we share it with
When we send the newsletter, the email-sending tool we use will receive your email address and, so the right email reaches you, your stage. It may use them only to send our emails. We will name that tool on this page before the first newsletter is sent.
5. Your agreement
We collect your stage only after you tick a separate box that says: "I agree that WITHIN Learning Group may store the stage I chose, which may reveal that I am pregnant or planning to be, only to choose which weekly email to send me. I can change it or ask to delete it at any time." You can withdraw that agreement at any time by changing your preferences or unsubscribing. When you unsubscribe we erase your name and stage and keep only your email address and a note that you left, so we do not add you again.
6. Your rights and how to use them
- Know and access: ask us to confirm whether we hold your information, to give you a copy, and to list the third parties and affiliates it has been shared with or sold to (none, other than the service providers described above).
- Withdraw your agreement: use "Update your preferences" or "Unsubscribe" at the bottom of any email.
- Delete: email us and we will delete your information.
Write to info@withinlearninggroup.com. We will respond within 45 days. If we decline a request, you may appeal by replying with the word "Appeal" in the subject line. We will answer your appeal within 45 days and explain our decision. If you are still not satisfied, you may contact the Washington State Attorney General's office.
7. Changes
If we ever collect more health information, we will update this page first, change its date, and ask for your agreement before collecting it.
8. Contact
WITHIN LEARNING GROUP LLC
info@withinlearninggroup.com
This policy describes our practices and is not legal advice. See also our privacy policy.
© 2026 WITHIN LEARNING GROUP LLC. All rights reserved.
Privacy policy
You should be able to read, learn, and use our tools about deeply personal subjects without handing us your information. This page explains, in plain words, what we collect, what we don't, and what may change.
WITHIN LEARNING GROUP LLC · Effective October 12, 2026 · Last updated October 28, 2026
- When you first visit, we ask you to accept this policy and the way the site stores things on your device. You can read the policy first, from the link on that screen.
- No accounts, no ads, and no analytics or tracking cookies on this site today.
- What you save or type in our tools (saved pages, notes, checklists, budget, and similar) stays in your own browser on your device. We don't receive it.
- If you email us, we receive what you send.
- Our free weekly newsletter is optional. If you join, we collect your email, an optional first name, and an optional stage you choose. We keep the list on our own server, never sell it, and every email has a one-click unsubscribe.
- Coming later: an optional login so the site can remember your activity on any device. We will update this policy and ask for your choice before collecting anything.
Words we use in this policy
Service
This website, WithinYourPregnancy.com.
Personal information
Information that identifies you or could reasonably be linked to you, such as an email address or a name.
Technical information
Details your browser sends automatically when it asks for a page, such as its IP address, browser type, and the time of the request.
Cookies
Small files that a website stores in your browser. This site sets none of its own today.
Local storage
A small area in your browser where this site keeps what you choose to save, on your device only.
Service providers
Companies that help us run the site, such as web hosting and security. They may use your information only to do that work for us.
1. Who we are
WITHIN LEARNING GROUP LLC ("we," "our," "us") owns and operates WithinYourPregnancy.com, an educational website. "You" means anyone who visits it. This policy applies to WithinYourPregnancy.com. Our other sites, such as WithinYourMarriage.com and WithinYourLight.com, publish their own privacy notices, which may differ because their features differ.
2. What we collect today
Weekly newsletter (optional, not open yet)
If you join, we store your email address, a first name if you give one, and a stage if you choose one (for example "pregnant"). A stage can reveal pregnancy or health-related information, so it is always optional and needs a separate tick-box agreement (see our consumer health data privacy policy). We also store the agreement text you saw, its version, the time you agreed, and a private code that powers your unsubscribe and preferences links. The list sits in the database of our own web hosting account. We do not save your IP address with it. To block spam, we briefly keep a one-way scrambled code from your connection (never the address itself) for up to an hour.
What you send us
The Contact page and email links open your own email app. If you send a message, we receive your email address, your name if you include it, and what you write. We use it to reply. Please don't send highly sensitive medical, mental health, financial, or personal details by ordinary email.
What stays on your device
To remember your place, this site uses your browser's local storage. Depending on what you use, it may hold: your language, the last page you read, pages you saved, topics you visited, the week of pregnancy you entered, readiness, budget, and agreement notes, checklists, gratitude entries, and notes you write for a provider visit. This information is not sent to us. Clearing your browser data deletes it, or you can clear it yourself:
Technical information
Like any website, our hosting provider's servers record standard technical details when a page is requested, such as your IP address, browser type, the page requested, and the date and time. Our site is also delivered through Cloudflare, a security and content-delivery service that handles each request so the site loads quickly and stays protected, so it also sees your IP address. We use this to run, secure, and fix the site, and we keep it only for a limited period.
Fonts
The site's fonts are stored on our own server, so your browser does not contact Google or any other font service when a page opens.
3. Sensitive subjects
You may come here for pregnancy, reproductive health, mental health, family, or relationship topics. We don't assume that reading about a topic means it applies to you, and we don't track your interests. Apart from the optional newsletter stage described in section 2, we don't collect health information. A stage can reveal pregnancy or health-related information, so we ask for your separate agreement before storing it, use it only to choose what to send you, never sell or share it for advertising, and delete it if you ask. If we ever collect more, we will tell you first, collect only what is needed, and get any consent the law requires (see section 14).
4. Optional accounts (planned)
We plan to offer an optional account, so that if you want the site to remember your activity across devices, you can log in and have it saved. None of this is happening yet. When we launch it:
- It will be optional. You can keep using the whole site without an account.
- We may collect your email address, an optional name, your password (stored securely and never in plain text), and what you choose to save: saved pages, progress, preferences, and entries in our tools.
- We will explain it at sign-up and ask for your agreement before collecting, with extra consent for any health-related information.
- We will use a sign-in cookie only to keep you logged in.
- You will be able to see, correct, export, and delete what we hold, including deleting your whole account.
- Before launch, we will update this policy and change the date at the top.
5. How we use information
- To reply to your messages.
- To run, secure, and fix the site, and to improve its accessibility.
- When accounts exist: to create and protect your account and remember your activity.
- To send the weekly newsletter, only if you join, and to choose which email fits the stage you picked. Every email includes a one-click unsubscribe link.
- To keep records and follow the law.
We do not sell your information, and we do not use it for advertising or to build profiles about you.
6. Cookies, analytics, and advertising
This site sets no cookies of its own today and runs no analytics or advertising tools. The newsletter signup sets no cookies. Newsletter emails are sent with an email tool. If that tool measures opens or clicks, we will say so here. If we later add a privacy-respecting analytics tool, an account cookie, or anything else that tracks use, we will say so here first and give you a choice where the law requires. We will not share identifiable health-related information with advertising platforms.
Do Not Track and Global Privacy Control. We do not track you across websites, we do not sell or share your information for advertising, and we collect no tracking data on this site. For that reason, a Do Not Track or Global Privacy Control signal from your browser does not change anything today, because there is nothing to switch off. If that changes, we will honor those signals as the law requires.
7. AI-powered tools
We don't offer any today. If we add one, we will tell you what you enter, which provider processes it, whether it is kept, and ask for consent before processing sensitive information. Please don't enter identifying details unless needed. AI-generated information is educational and is not professional medical, psychological, or legal advice.
8. Who we share information with
We don't sell personal information. We may share it with service providers that help us run the site, such as web hosting (which stores the newsletter list for us), security, the tool we use to send emails, and, in the future, account services. They may use it only to do that work for us. We may also share information when the law requires it, to protect someone's safety, or if our business changes hands, with the same protections.
9. Email and messages
Ordinary email is not fully secure or confidential. Our inbox is not monitored for emergencies. If you or someone else is in danger, call 911. If you are in emotional crisis, call or text 988.
10. Security
We use reasonable safeguards for the information we hold, including secure hosting and limited access. No website or transmission is completely secure, so we can't guarantee absolute security. Choosing a private window, logging out on shared devices, and keeping your devices updated all help.
11. How long we keep information
We keep emails only as long as needed to reply and keep reasonable records. When you unsubscribe, we erase your name and stage and keep only your email address and a note that you left, so we don't add you again. Ask us if you'd like that deleted too. Server logs are kept for a limited period. Once accounts exist, we will keep account data until you delete it or close your account, unless the law requires us to keep it longer. Then we delete or de-identify it.
12. Children and teens
This site is written for adults, parents, and caregivers. It is not directed to children under 13, and we don't knowingly collect personal information from them. If you believe a child has sent us personal information, contact us and we will delete it. Teens are welcome to read, and we encourage them to talk with a parent or trusted adult about anything they read here.
13. Your choices and rights
Depending on where you live and the law, you may have the right to ask what personal information we hold about you, to see it, correct it, delete it, withdraw consent, limit certain uses, opt out of optional emails, or file a complaint. Email us at the address below and we will respond as the law requires. We won't treat you unfairly for using these rights. You can also remove anything stored on your device at any time by clearing your browser data.
California residents. You may ask us to tell you what personal information we hold about you, to delete or correct it, and to limit how we use it. We do not sell personal information or share it for cross-context behavioral advertising, and we will not treat you differently for using your rights. Email us at the address in section 18.
14. Washington consumer health data
Information about physical or mental health, reproductive health, or pregnancy can count as "consumer health data" under Washington's My Health My Data Act and similar laws. The only health-related information we may hold is the optional newsletter stage, which we collect only after a separate agreement. We explain it in our separate Consumer Health Data Privacy Policy. If we collect more, for example through optional accounts that save health-related entries, we will update both policies first and ask for your agreement. We will not sell consumer health data without the authorization the law requires.
15. Links to other websites
Our pages link to outside resources, such as health agencies and organizations. Those sites have their own privacy practices, and we aren't responsible for them. Please read their policies.
16. Visitors outside the United States
This site is written for U.S. residents. If you visit from elsewhere, your information may be processed in the United States, where privacy laws may differ from your own.
If you are in the European Economic Area or the United Kingdom, you may ask us to give you access to your personal information, correct it, erase it, restrict or object to how we use it, give you a copy in a common format, or withdraw your consent at any time, and you may complain to your local data protection authority. We use personal information because you agreed (for example, when you join the newsletter), because we have a legitimate interest in running and protecting the site, and to follow the law. We may ask you to confirm your identity before we act on a request.
17. Changes to this policy
We will update this page when our practices change, and we will change the "last updated" date. If a change affects how we treat your information, we will give clear notice and ask for your consent where the law requires.
18. Contact us
WITHIN LEARNING GROUP LLC
Privacy contact: info@withinlearninggroup.com
Questions, privacy requests, or concerns about how your information is handled. We will review and respond as applicable law requires.
This policy describes our practices and is not legal advice. See also our ethics commitments and the disclosure in the page footer.
© 2026 WITHIN LEARNING GROUP LLC. All rights reserved.